Related Experiment Video
Updated: May 5, 2026
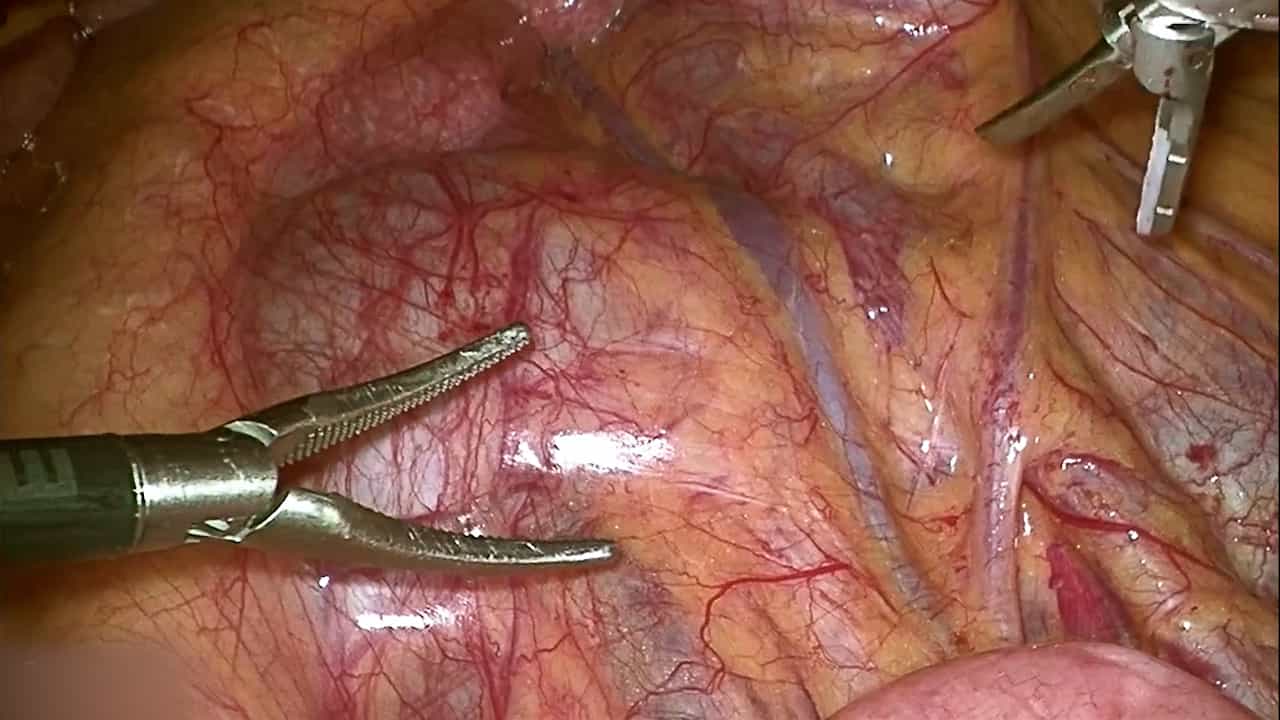

Transmesenteric Laparoscopic Pyeloplasty in Trendelenburg Position for Horseshoe Kidney with Hydronephrosis
Published on: July 8, 2025
Coexisting ureteropelvic junction obstruction and ureterovesical junction obstruction: is pyeloplasty always the
Yong Seung Lee1, Young Jae Im1, Hyeyoung Lee1
1Department of Urology and Urological Science Institute, Yonsei University College of Medicine, Seoul, Korea.

Insights
Diagnosing simultaneous ureteropelvic junction obstruction (UPJO) and ureterovesical junction obstruction (UVJO) in children is challenging. Preoperative evaluation, including retrograde ureteropyelography, is crucial for accurate diagnosis and appropriate surgical planning.
Area of Science:
- Pediatric Urology
- Surgical Management
- Diagnostic Imaging
Background:
- Coexisting ureteropelvic junction obstruction (UPJO) and ureterovesical junction obstruction (UVJO) present diagnostic and therapeutic challenges in pediatric patients.
- Accurate preoperative diagnosis is critical for effective management of these complex urinary tract conditions.
Purpose of the Study:
- To review the diagnostic accuracy and surgical outcomes for pediatric patients with concurrent UPJO and UVJO.
- To evaluate the effectiveness of different surgical approaches in managing these combined obstructions.
Main Methods:
- Retrospective analysis of 15 pediatric patients diagnosed with coexisting UPJO and UVJO between 2003 and 2012.
- Review of medical records, including preoperative evaluations (antegrade and retrograde studies) and surgical interventions (pyeloplasty, ureteroneocystostomy).
Main Results:
- Preoperative diagnosis was achieved in 66.7% of cases; 33.3% had only one obstruction diagnosed.
- Initial surgical management varied, with pyeloplasty in 9 patients and ureteroneocystostomy in 5.
- Secondary procedures were required in 4 patients (2 after pyeloplasty, 2 after ureteroneocystostomy).
Conclusions:
- Accurate diagnosis of combined UPJO and UVJO is often difficult.
- Retrograde ureteropyelography is recommended before pyeloplasty to assess the distal ureter and UVJ.
- Initial pyeloplasty may not always be the optimal first-line treatment for coexisting UPJO and UVJO.
Objective:
To report our experience with the diagnosis and management of coexisting ureteropelvic junction obstruction (UPJO) and ureterovesical junction obstruction (UVJO).
Materials And Methods:
Among the pediatric patients who underwent pyeloplasty or ureteroneocystostomy from 2003-2012, 15 patients were diagnosed with coexisting UPJO and UVJO. We retrospectively analyzed their medical records.
Results:
Of the 15 patients with coexisting UPJO and UVJO, the correct diagnosis was made preoperatively in 10 patients (66.7%). In 4 other patients, only UPJO was diagnosed, and in 1 patient, only UVJO was diagnosed. The decision of where to initially operate was determined from the combined results of the preoperative antegrade evaluation and retrograde ureteropyelography. Pyeloplasty was the initial surgical management choice for 9 patients, and ureteroneocystostomy was the initial surgical approach in 5 patients. In 1 patient, both pyeloplasty and ureteroneocystostomy were performed simultaneously. Of the 9 patients who underwent initial pyeloplasty, additional ureteroneocystostomy was required in 2. Additional pyeloplasty was required in 2 of the 5 patients who initially underwent ureteroneocystostomy.
Conclusion:
It is often difficult to correctly diagnose coexisting UPJO and UVJO. In patients with UPJO, it is highly recommended that retrograde ureteropyelography be performed before pyeloplasty to evaluate the distal ureter-ureterovesical junction. Initial pyeloplasty is not always recommended as a first-line therapy.

Related Concept Videos
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:27
Acute Pyelonephritis I: Introduction
 01:30
Urinary Tract Calculi III: Medical Management