Related Experiment Video
Updated: May 5, 2026


Author Spotlight: Advancing Early Detection and Treatment of Gastrointestinal Tumors
Published on: February 16, 2024
Esophageal intraepithelial invasion of Helicobacter pylori correlates with atypical hyperplasia
Wen-sheng Li1, Dong-ping Tian, Xiao-ying Guan
1Key Immunopathology Laboratory of Guangdong Province, Institute of Clinical Pathology & Department of Pathology, Shantou University Medical College, Shantou, Guangdong, China; Shaanxi Provincial People's Hospital, The Third Affiliated Hospital, Medical College of Xi'an Jiaotong University, Xi'an, China.

Abstract:
Helicobacter pylori (H. pylori), a common pathogen residing in the gastrointestinal tract, has been well characterized in stomach cancer,while its correlation with esophageal cancer remains poorly understood. In this study, we aim to assess the relationship between esophageal intraepithelial H. pylori invasion and inflammation as well as atypical hyperplasia in esophageal squamous epithelial tissues. Esophageal squamous cell carcinoma (ESCC) tissue samples from 196 individuals from both southern and northern esophageal carcinoma high-risk areas in China were examined (125 from northern high-risk areas, 71 from southern high-risk area), while additional 30 samples were collected adjacent to the esophageal squamous cell carcinoma (A-ESCC). H. pylori infection was identified by Giemsa staining, immuno-histochemical staining, and H. pylori 16S rRNA-based PCR. A significant increase of H. pylori infection was found in tumor tissues (including ESCC and A-ESCC samples) compared to that of non-tumor tissues (p < 0.05). The positive rate of H. pylori 16S rRNA in ESCC, A-ESCC, and normal groups were 62.5, 74.1, and 26.7%, respectively. The PCR results showed that the positive incidence of the H. pylori virulence factor CagA gene in tumor (ESCC and A-ESCC) and normal groups was 54.9 and 20%, respectively (p < 0.05). To explore the possible causes of CagA+ H. pylori infection leading to carcinogenesis, we found that CagA+ H. pylori filtrate induced DNA strand breaks in esophageal epithelial NE3 cells, suggesting that H. pylori infection may be an original cause leading to atypical hyperplasia of esophageal squamous epithelial tissues and contributed to pathological carcinogenesis of ESCC.
More Related Videos


Related Concept Videos
 01:26
Gastritis II: Pathophysiology
 01:27
Peptic Ulcer
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:25
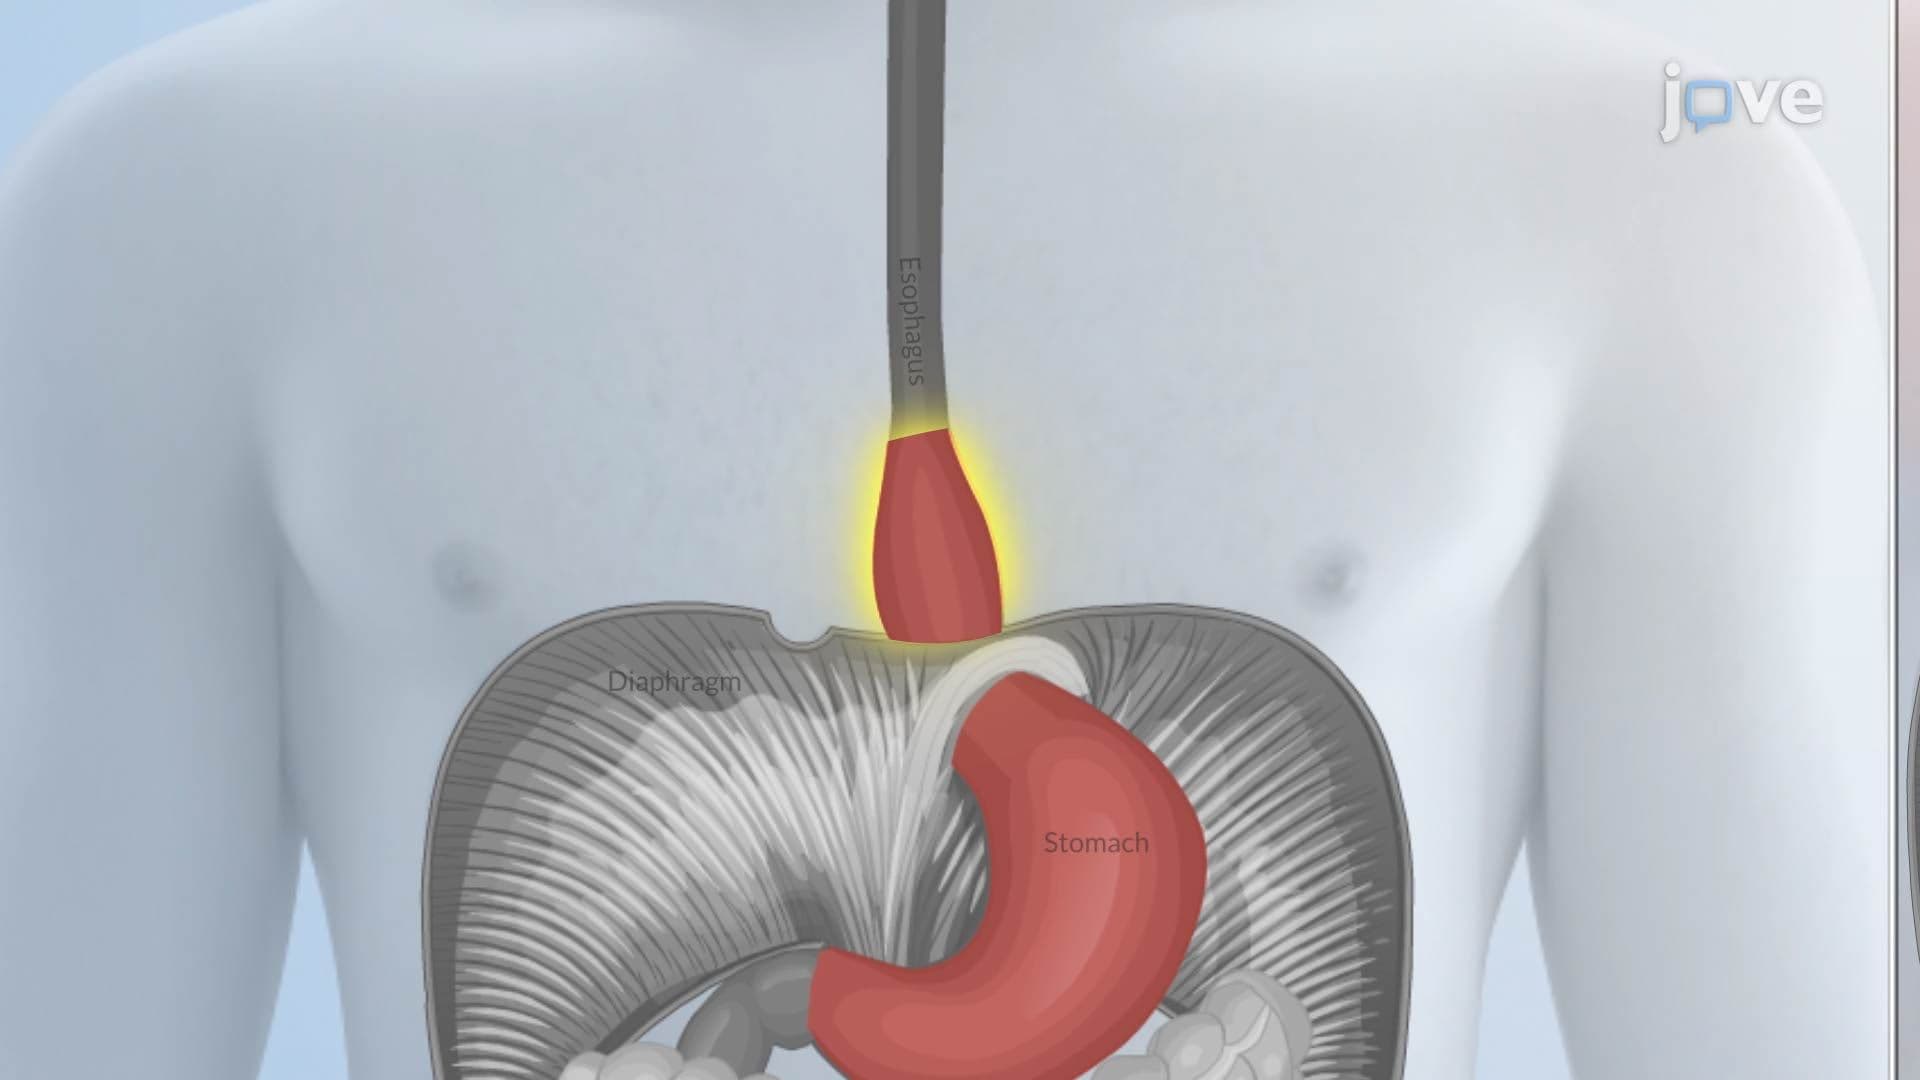
Hiatal Hernia
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more...
 01:24
Peptic Ulcer Disease II: Pathophysiology