Related Experiment Video
Updated: May 5, 2026
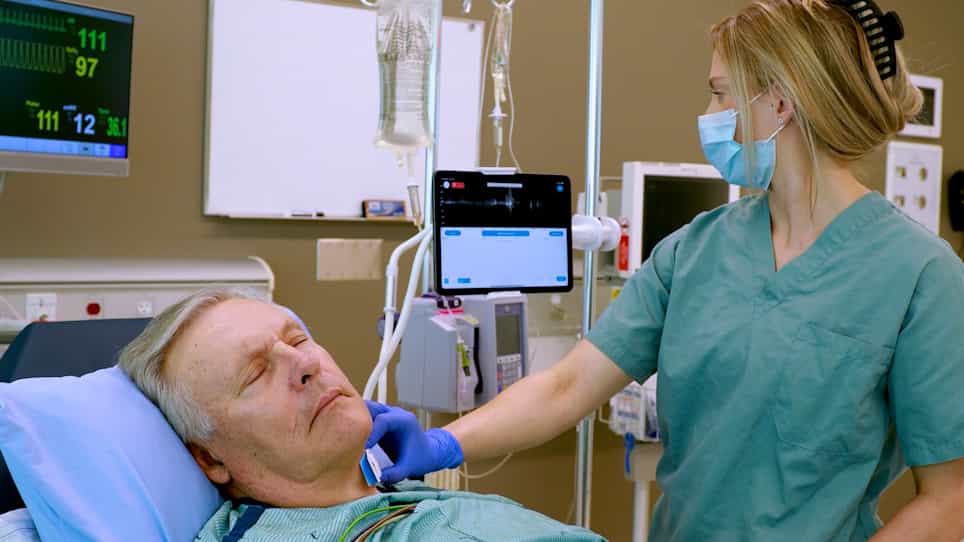

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Predicting fluid responsiveness in children: a systematic review
Heng Gan1, Maxime Cannesson, John R Chandler
1From the *Department of Anesthesiology, Pharmacology, and Therapeutics, University of British Columbia; †Department of Anesthesia, BC Children's Hospital, Vancouver, Canada; ‡Department of Anesthesiology and Perioperative Care, University of California, Irvine, School of Medicine, Irvine, California; and §Department of Anaesthesia, University College London Trust, London, United Kingdom.

Insights
Predicting fluid responsiveness in children is challenging. Respiratory variation in aortic blood flow peak velocity is the only reliable predictor, while static and arterial blood pressure-based dynamic variables are not effective.
Area of Science:
- Pediatric critical care medicine
- Hemodynamics
- Fluid resuscitation
Background:
- Fluid administration is key for hemodynamic resuscitation, but not all children respond.
- Excessive fluid can be harmful, making accurate prediction of fluid responsiveness crucial.
- Existing dynamic variables, effective in adults, lack consensus for pediatric use.
Purpose of the Study:
- To systematically review evidence on predictors of fluid responsiveness in pediatric patients.
- To identify reliable hemodynamic variables for guiding fluid therapy in children.
Main Methods:
- Systematic literature search of PubMed and EMBASE (1947-2013).
- Inclusion of studies on pediatric subjects (infants, children, adolescents).
- Data extraction focused on variables with receiver operating characteristic curve area significantly above 0.5.
Main Results:
- Twelve studies analyzed 501 fluid boluses in 438 pediatric patients.
- Respiratory variation in aortic blood flow peak velocity was the only variable consistently predictive across multiple studies.
- Static variables and dynamic variables based on arterial blood pressure or plethysmography were generally not predictive.
Conclusions:
- Respiratory variation in aortic blood flow peak velocity is the sole validated predictor of fluid responsiveness in children.
- Static variables are unreliable in children, mirroring adult evidence.
- Dynamic arterial blood pressure-based variables are not predictive in children; plethysmography data is inconclusive.
Background:
Administration of fluid to improve cardiac output is the mainstay of hemodynamic resuscitation. Not all patients respond to fluid therapy, and excessive fluid administration is harmful. Predicting fluid responsiveness can be challenging, particularly in children. Numerous hemodynamic variables have been proposed as predictors of fluid responsiveness. Dynamic variables based on the heart-lung interaction appear to be excellent predictors of fluid responsiveness in adults, but there is no consensus on their usefulness in children.
Methods:
We systematically reviewed the current evidence for predictors of fluid responsiveness in children. A systematic search was performed using PubMed (1947-2013) and EMBASE (1974-2013). Search terms included fluid, volume, response, respond, challenge, bolus, load, predict, and guide. Results were limited to studies involving pediatric subjects (infant, child, and adolescent). Extraction of data was performed independently by 2 authors using predefined data fields, including study quality indicators. Any variable with an area under the receiver operating characteristic curve that was significantly above 0.5 was considered predictive.
Results:
Twelve studies involving 501 fluid boluses in 438 pediatric patients (age range 1 day to 17.8 years) were included. Twenty-four variables were investigated. The only variable shown in multiple studies to be predictive was respiratory variation in aortic blood flow peak velocity (5 studies). Stroke volume index, stroke distance variation, and change in cardiac index (and stroke volume) induced by passive leg raising were found to be predictive in single studies only. Static variables based on heart rate, systolic arterial blood pressure, preload (central venous pressure, pulmonary artery occlusion pressure), thermodilution (global end diastolic volume index), ultrasound dilution (active circulation volume, central blood volume, total end diastolic volume, total ejection fraction), echocardiography (left ventricular end diastolic area), and Doppler (stroke volume index, corrected flow time) did not predict fluid responsiveness in children. Dynamic variables based on arterial blood pressure (systolic pressure variation, pulse pressure variation and stroke volume variation, difference between maximal or minimal systolic arterial blood pressure and systolic pressure at end-expiratory pause) and plethysmography (pulse oximeter plethysmograph amplitude variation) were also not predictive. There were contradicting results for plethymograph variation index and inferior vena cava diameter variation.
Conclusions:
Respiratory variation in aortic blood flow peak velocity was the only variable shown to predict fluid responsiveness in children. Static variables did not predict fluid responsiveness in children, which was consistent with evidence in adults. Dynamic variables based on arterial blood pressure did not predict fluid responsiveness in children, but the evidence for dynamic variables based on plethysmography was inconclusive.

Related Concept Videos
 01:29
Drug Dosing: Infants and Children
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:21
Factors Affecting Drug Response: Overview
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure