
A case of difficult management of fluid-electrolyte imbalance in choroid plexus papilloma
Atsushi Saito1, Shinjitsu Nishimura, Tomoaki Fujita
1Department of Neurosurgery, Aomori Prefectural Central Hospital.

Insights
A choroid plexus papilloma caused cerebrospinal fluid overproduction and severe dehydration in a child. Prompt surgical removal resolved these critical issues, highlighting the need for careful management.
Area of Science:
- Pediatric Neurology
- Neurosurgery
- Pediatric Oncology
Background:
- Choroid plexus papillomas are rare intraventricular tumors, often presenting with hydrocephalus.
- Fluid and electrolyte imbalances can complicate management, particularly with cerebrospinal fluid overproduction.
Observation:
- A 22-month-old boy presented with gait disturbance and nausea, later developing acute hydrocephalus.
- External ventricular drainage revealed significant cerebrospinal fluid overproduction (800-1500 mL/day) and marked dehydration with electrolyte abnormalities.
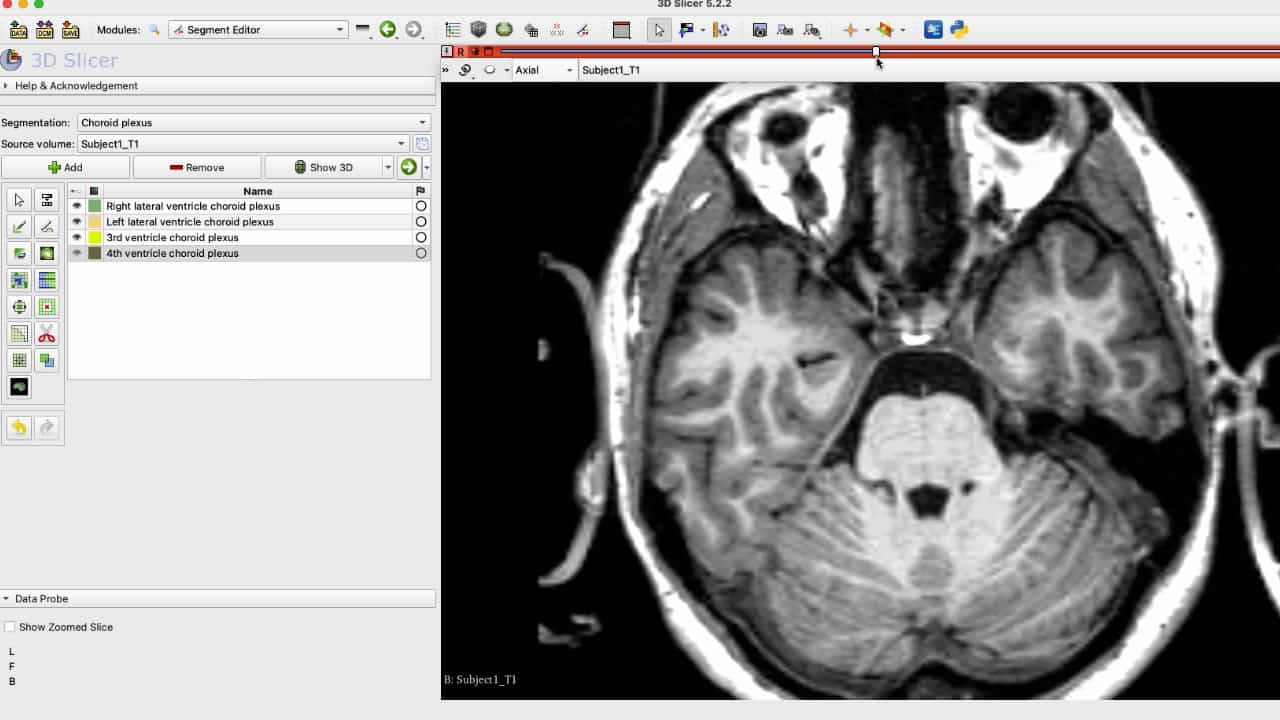
- Magnetic resonance imaging identified a multi-lobular mass in the right lateral ventricle, suspected to be a choroid plexus tumor.
Findings:
- Surgical removal of the choroid plexus papilloma led to normalization of blood urea nitrogen:creatinine ratio, hemoglobin levels, and electrolytes.
- Cerebrospinal fluid overproduction significantly decreased post-operatively (<300 mL/day).
- Histopathological examination confirmed the diagnosis of choroid plexus papilloma.
Implications:
- This case underscores the potential for severe fluid-electrolyte imbalance due to over-drainage in pediatric hydrocephalus secondary to choroid plexus papilloma.
- Cautious fluid management and timely surgical intervention are crucial for managing cerebrospinal fluid overproduction and associated complications.
- Early diagnosis and surgical resection are vital for favorable outcomes in pediatric choroid plexus papilloma.
Abstract:
A 22-month-old boy presented with nausea and gradual deterioration of gait disturbance. Computed tomography (CT) demonstrated an intraventricular mass lesion in the right lateral ventricle. He was referred to our department 3 weeks after onset. Acute hydrocephalus gradually proceeded 4 days after admission, and external ventricular drainage (EVD) was performed. EVD revealed cerebrospinal fluid (CSF) overproduction (800-1,500 mL/day) under constant pressure of 10 cm H2O above external auditory meatus. Magnetic resonance imaging showed a multi-lobular mass in the inferior horn of the right lateral ventricle. A choroid plexus tumor was suspected. The ratio of blood urea nitrogen:creatinine (BUN:Cre) remained between 30 and 40, and hemoglobin was between 14.0-17.0 mg/dL, suggesting marked dehydration. Serum sodium varied between 117 and 140 mmol/L, and serum potassium between 2.2 mmol/L and 6.9 mmol/L. The amount of EVD was unstable and fluid balance management was difficult. Hypotonic fluid with sodium chloride supplement was used to adjust the fluid and electrolyte imbalance. Surgical removal of the tumor was performed 6 days after EVD and tumor was grossly and totally removed. The high BUN:Cre ratio decreased to about 15 and hemoglobin recovered to 7.5-9.0 mg/dL after removal. Electrolytes returned to the normal range. Overproduction of CSF also markedly improved to < 300 mL/day. Histopathological examination diagnosed choroid plexus papilloma.We experienced a case of choroid plexus papilloma associated with fluid-electrolyte imbalance due to over-drainage after EVD, which could not be effectively controlled before tumor removal. Cautious fluid management and emergent surgical resection might be required to manage the overproduction of CSF and fluid-electrolyte imbalance.
Related Concept Videos
 01:22
Cerebral Edema ll: Pathophysiology
 01:19
Cerebral Edema l: Introduction
 01:25
Glaucoma: Overview
 01:21
Cytotoxic Edema: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:28
Angle Closure Glaucoma: Treatment