Related Experiment Video
Updated: May 5, 2026


Electrochemiluminescence Assays for Human Islet Autoantibodies
Published on: March 23, 2018
DWI findings of autoimmune pancreatitis: comparison between symptomatic and asymptomatic patients
Hodaka Oki1, Yoshiko Hayashida, Haruka Oki
1Department of Radiology, University of Occupational and Environmental Health, Yahatanishi-ku, Kitakyushu, Fukuoka, Japan.

Purpose:
To compare the MR findings including diffusion-weighted imaging (DWI) between symptomatic and asymptomatic patients with autoimmune pancreatitis (AIP) and to determine whether DWI can be used as an objective biomarker for symptomatic AIP, which is considered an indication for steroid therapy.
Materials And Methods:
This retrospective study was approved by our institutional review board. MRI scans from 37 patients with AIP (symptomatic, n = 19; asymptomatic, n = 18) were retrospectively evaluated. The imaging studies were performed on a 1.5 Tesla scanner and assessed for parenchymal enlargement, narrowing of the main pancreatic duct, hypointensity on fat-suppressed T1-weighted images (FS-T1WI), a capsule-like rim, extrapancreatic lesions, and hyperintensity on DWI. The findings were compared by univariate and multivariate logistic regression analysis. Apparent diffusion coefficient (ADC) values were also calculated.
Results:
Multivariate analysis showed that hyperintensity on DWI were most significantly associated with the symptoms of AIP (odds ratio = 28.2; P = 0.003). Interobserver agreement for DWI was also high. The ADC values were significantly lower in symptomatic than in asymptomatic patients (0.94 ± 0.17 versus 1.16 ± 0.16 × 10(-3) mm(2)/s, P < 0.001). Receiver operating characteristic curve analysis of the ADC values to differentiate between symptomatic and asymptomatic patients showed that sensitivity was 68.4%, specificity 83.3%, and AUC 0.74.
Conclusion:
Signal intensity on DWI and ADC value were well correlated with the active symptoms of AIP patients. DWI may be useful as an objective biomarker for determining the indication for steroid therapy.
Insights
Diffusion-weighted imaging (DWI) and apparent diffusion coefficient (ADC) values can differentiate symptomatic from asymptomatic autoimmune pancreatitis (AIP). DWI may serve as an objective biomarker for guiding steroid therapy in AIP patients.
Area of Science:
- Radiology
- Gastroenterology
- Medical Imaging
Background:
- Autoimmune pancreatitis (AIP) is a chronic inflammatory condition requiring timely diagnosis and treatment.
- Differentiating symptomatic from asymptomatic AIP is crucial for initiating steroid therapy.
- Current diagnostic methods may not always provide objective markers for symptom severity.
Purpose of the Study:
- To compare magnetic resonance imaging (MRI) findings, including diffusion-weighted imaging (DWI), between symptomatic and asymptomatic AIP patients.
- To evaluate the potential of DWI as an objective biomarker for identifying symptomatic AIP, indicating the need for steroid therapy.
Main Methods:
- Retrospective analysis of MRI scans from 37 AIP patients (19 symptomatic, 18 asymptomatic).
- Assessment of specific MRI features including parenchymal enlargement, main pancreatic duct narrowing, T1WI hypointensity, capsule-like rim, extrapancreatic lesions, and DWI hyperintensity.
- Comparison of findings using logistic regression and calculation of apparent diffusion coefficient (ADC) values.
Main Results:
- Hyperintensity on DWI was significantly associated with AIP symptoms (odds ratio = 28.2, P = 0.003).
- ADC values were significantly lower in symptomatic AIP patients compared to asymptomatic ones (0.94 ± 0.17 vs. 1.16 ± 0.16 × 10⁻³ mm²/s, P < 0.001).
- Receiver operating characteristic analysis for ADC values showed 68.4% sensitivity, 83.3% specificity, and an AUC of 0.74 for differentiating symptomatic from asymptomatic AIP.
Conclusions:
- Diffusion-weighted imaging (DWI) signal intensity and ADC values correlate well with active AIP symptoms.
- DWI shows promise as an objective biomarker for determining the indication for steroid therapy in AIP patients.
Related Concept Videos
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
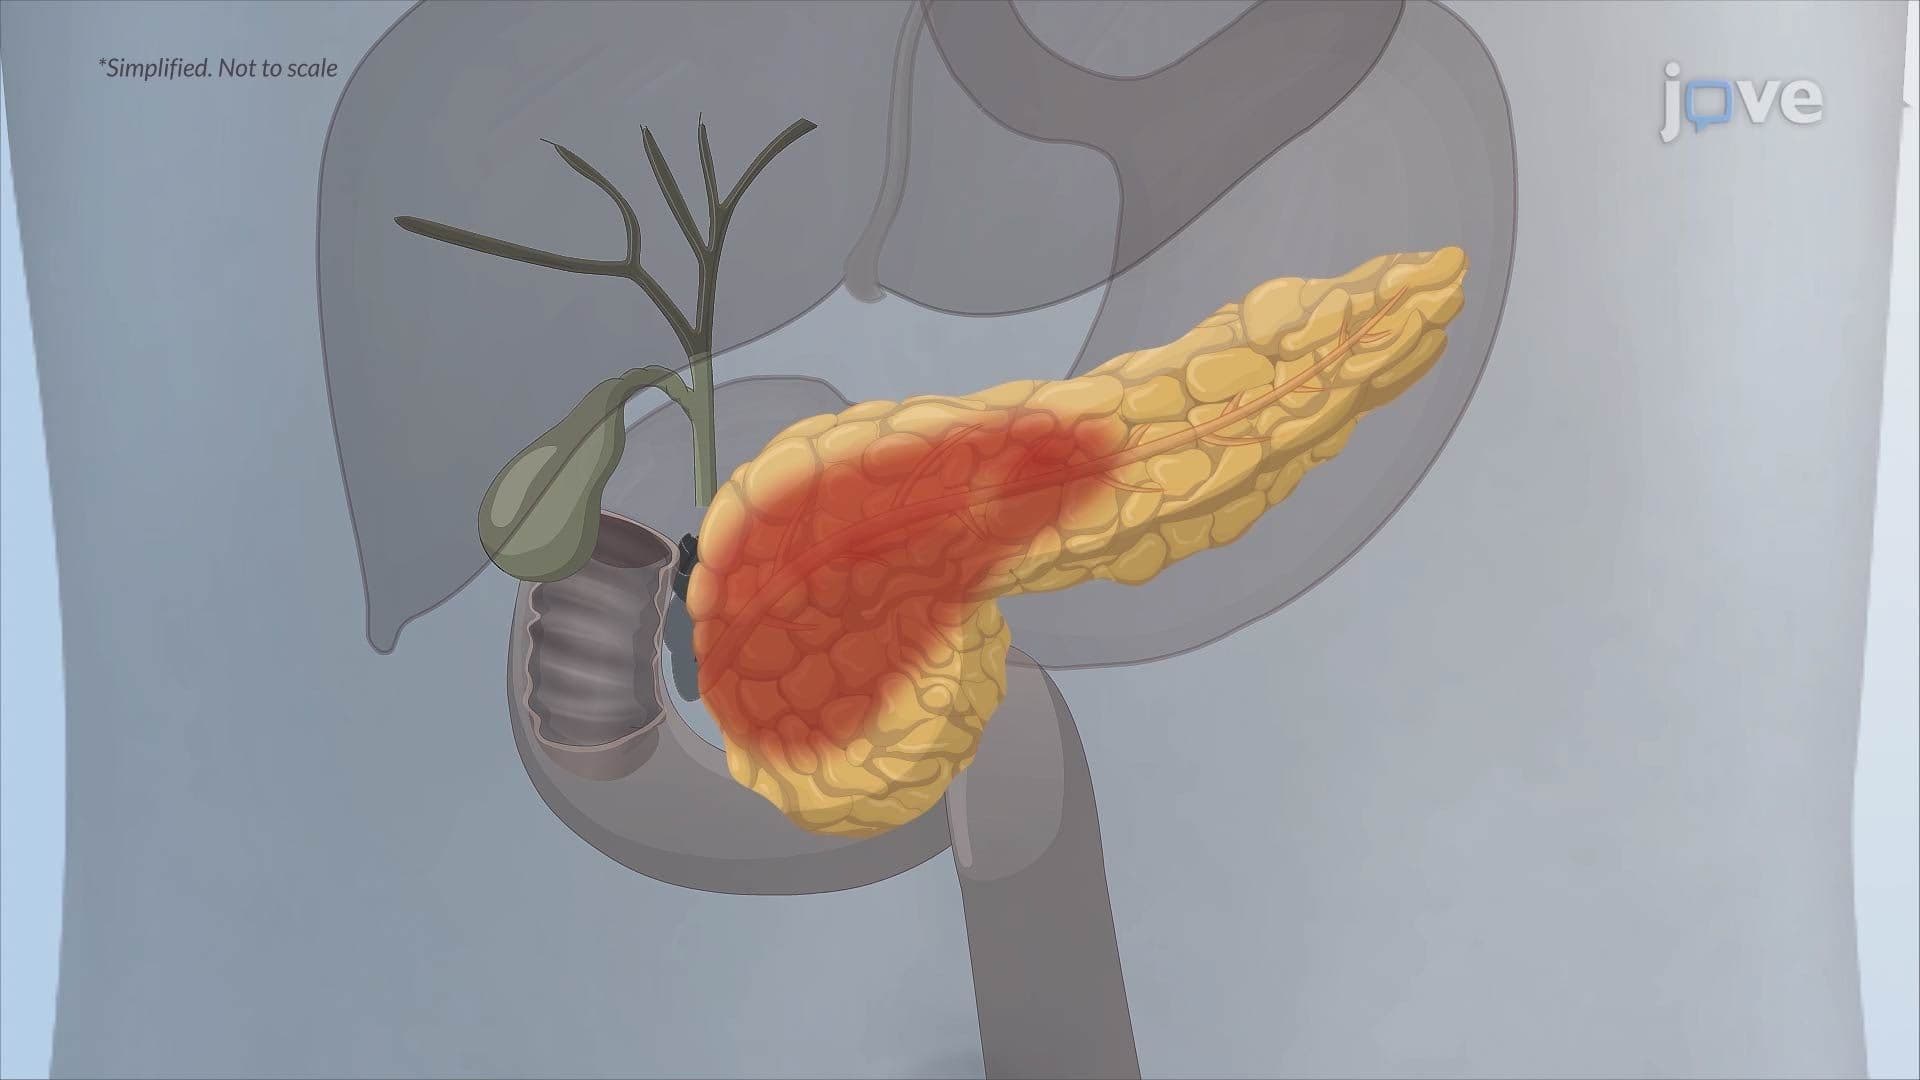
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:26
Type I Diabetes II: Pathophysiology
 01:12
Type I Diabetes I: Introduction
 01:21
Acute Pancreatitis II: Pathophysiology