Related Experiment Video
Updated: May 5, 2026
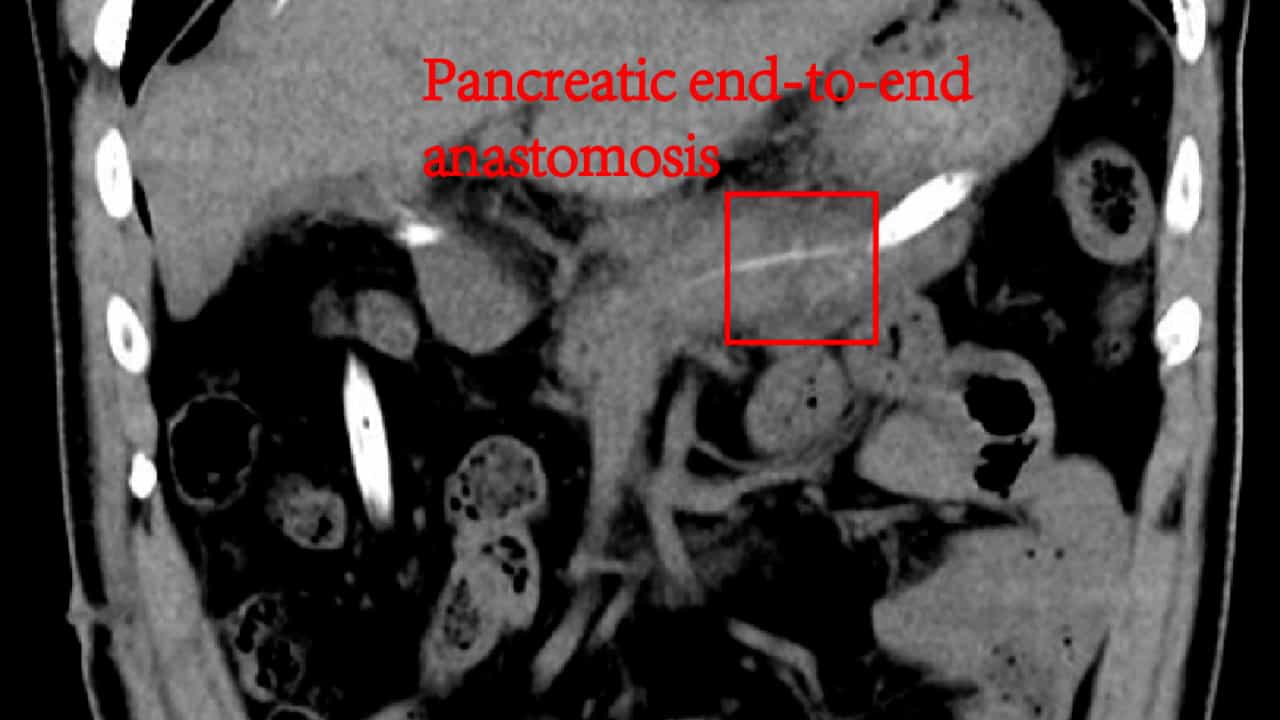
Application of Mid-Pancreatectomy with End-to-End Anastomosis in Pancreatic Benign Tumors
Published on: February 9, 2024
Impact of cardiac comorbidity on early outcomes after pancreatic resection
Sean M Ronnekleiv-Kelly1, David Y Greenblatt, Chee Paul Lin
1Department of Surgery, University of Wisconsin, 600 Highland Avenue, G4/700 CSC, Madison, WI, 53792, USA.

Insights
Cardiac disease significantly increases risks for serious complications and mortality following pancreatic resection (PR). Identifying these patients allows for targeted interventions to improve outcomes after PR.
Area of Science:
- Surgical outcomes research
- Cardiovascular disease epidemiology
- Gastrointestinal surgery
Background:
- Pancreatic resection (PR) carries risks of postoperative complications.
- Identifying high-risk patient subgroups can guide interventions.
- Cardiac disease is a common comorbidity in surgical patients.
Purpose of the Study:
- To examine the association between cardiac disease history and outcomes after pancreatic resection.
- To determine if acute cardiac events impact postoperative complications and mortality.
- To inform risk stratification and patient counseling for PR.
Main Methods:
- Retrospective analysis of patients undergoing PR (2005-2010) from the ACS NSQIP database.
- Categorization of patients based on any history of cardiac disease or acute cardiac disease.
- Multivariate analysis to assess the relationship between cardiac disease and outcomes.
Main Results:
- Patients with any cardiac disease history had higher rates of serious complications (34% vs. 24%) and mortality (4.5% vs. 2.0%) compared to those without.
- Patients with acute cardiac disease showed increased serious complications (37% vs. 25%) and mortality (8.6% vs. 2.2%).
- Cardiac disease remained a significant independent predictor of mortality in multivariate analysis.
Conclusions:
- Cardiac disease is a significant risk factor for adverse outcomes, including mortality, after pancreatic resection.
- These findings are crucial for improving informed consent processes for patients considering pancreatectomy.
- Risk stratification based on cardiac history can optimize perioperative care.
Background:
In patients undergoing pancreatic resection (PR), identification of subgroups at increased risk for postoperative complications can allow focused interventions that may improve outcomes.
Study Design:
Patients undergoing PR from 2005-2010 were selected from the American College of Surgeons National Surgical Quality Improvement Program database and categorized as having any history of cardiac disease (angina, congestive heart failure (CHF), myocardial infarction (MI), cardiac stent, or bypass) or as having acute cardiac disease (symptoms of CHF or angina within 30 days or MI within 6 months). These variables were utilized to examine the relationship between cardiac disease and outcomes after PR.
Results:
The rate of serious complications and perioperative mortality in patients with any history of cardiac disease vs. those without was 34 vs. 24 % (p < 0.001) and 4.5 vs. 2.0 % (p < 0.001), respectively, and in patients with acute cardiac disease compared to patients without was 37 vs. 25 % (p < 0.001) and 8.6 vs. 2.2 % (p < 0.001), respectively. In multivariate analysis, the two cardiac disease variables remained associated with mortality.
Conclusions:
In patients undergoing PR, cardiac disease is a significant risk factor for adverse outcomes. These observations are critical for meaningful informed consent in patients considering pancreatectomy.
More Related Videos
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management