Related Experiment Video
Updated: May 5, 2026


In Vitro Modeling of Down Syndrome Neurogenesis Using Human-Induced Pluripotent Stem Cells
Published on: March 7, 2025
Thyroid dysfunction in a cohort of South African children with Down syndrome
Shahida Moosa1, David G Segal, Arnold L Christianson
1Division of Human Genetics, National Health Laboratory Service and School of Pathology, Faculty of Health Sciences, University of the Witwatersrand, Johannesburg, South Africa. shahidamoosa@gmail.com.

Insights
Thyroid dysfunction is common in South African children with Down syndrome (DS). Many children with abnormal thyroid function tests (TFTs) were not referred for treatment, highlighting a need for improved surveillance and management guidelines.
Area of Science:
- Pediatric Endocrinology
- Genetics
- Public Health
Background:
- Thyroid dysfunction is more prevalent in individuals with Down syndrome (DS) globally.
- Data on thyroid function in sub-Saharan African children with DS is limited.
Purpose of the Study:
- To determine the spectrum of thyroid function in South African children with DS.
- To evaluate current referral and treatment practices for thyroid dysfunction in this population.
Main Methods:
- Retrospective study of 391 children with DS (2003-2008) at Johannesburg hospitals.
- Collected thyroid function test (TFT) results (TSH, free thyroxine) and demographic data.
- Reviewed endocrine clinic files for referral and treatment information.
Main Results:
- 83.6% of children had at least one TFT, primarily between 2-12 months.
- Subclinical hypothyroidism (SCH) was the most common dysfunction (28.7%).
- One-third of patients, including neonates, were not referred for evaluation or treatment.
- Inter-laboratory discrepancies and lack of reference ranges complicated results interpretation.
- Treatment practices for SCH were influenced by ongoing controversy.
Conclusions:
- Thyroid dysfunction is prevalent in South African children with DS.
- Urgent need to address laboratory discrepancies and establish clear guidelines for surveillance and treatment.
- Improved management is crucial to prevent irreversible neurological and physical impairments.
Background:
While international studies show thyroid dysfunction occurs more commonly in individuals with Down syndrome (DS) than in the general population, there is a paucity of available data from sub-Saharan Africa.
Objectives:
To document the range of thyroid function in a cohort of South African children with DS, and to assess referral and treatment practices when thyroid dysfunction was present.
Methods:
A retrospective file-based study of 391 children with DS seen at the genetic clinics at three Johannesburg hospitals from 2003 to 2008. Thyroid function test (TFT) results (thyroid-stimulating hormone and free thyroxine) and demographic details were collected for each child. Endocrine clinic files from two of the hospitals were reviewed for additional referral and treatment information.
Results:
The majority (83.6%) of children had at least one TFT, in most cases performed between the ages of 2 and 12 months. The most common form of thyroid dysfunction was subclinical hypothyroidism (SCH) (28.7%). Up to one-third of the patients, including several neonates with abnormal results, were not referred for further evaluation and were therefore not receiving the necessary treatment. Inter- laboratory biochemical discrepancies and lack of population-specific reference ranges complicated the interpretation of results. The controversy surrounding whether, and how, to treat SCH influenced treatment practices.
Conclusions:
Thyroid dysfunction is prevalent in South African children with DS. There is an urgent need to address the laboratory biochemical discrepancies, and to establish guidelines for surveillance and treatment to prevent further irreversible neurological and physical impairment.


Related Concept Videos
 01:23
Hypothyroidism II: Pathophysiology
 01:27
Hyperthyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:28
Graves' Disease I: Introduction
 01:20
Synthesis and Regulation of Thyroid Hormones
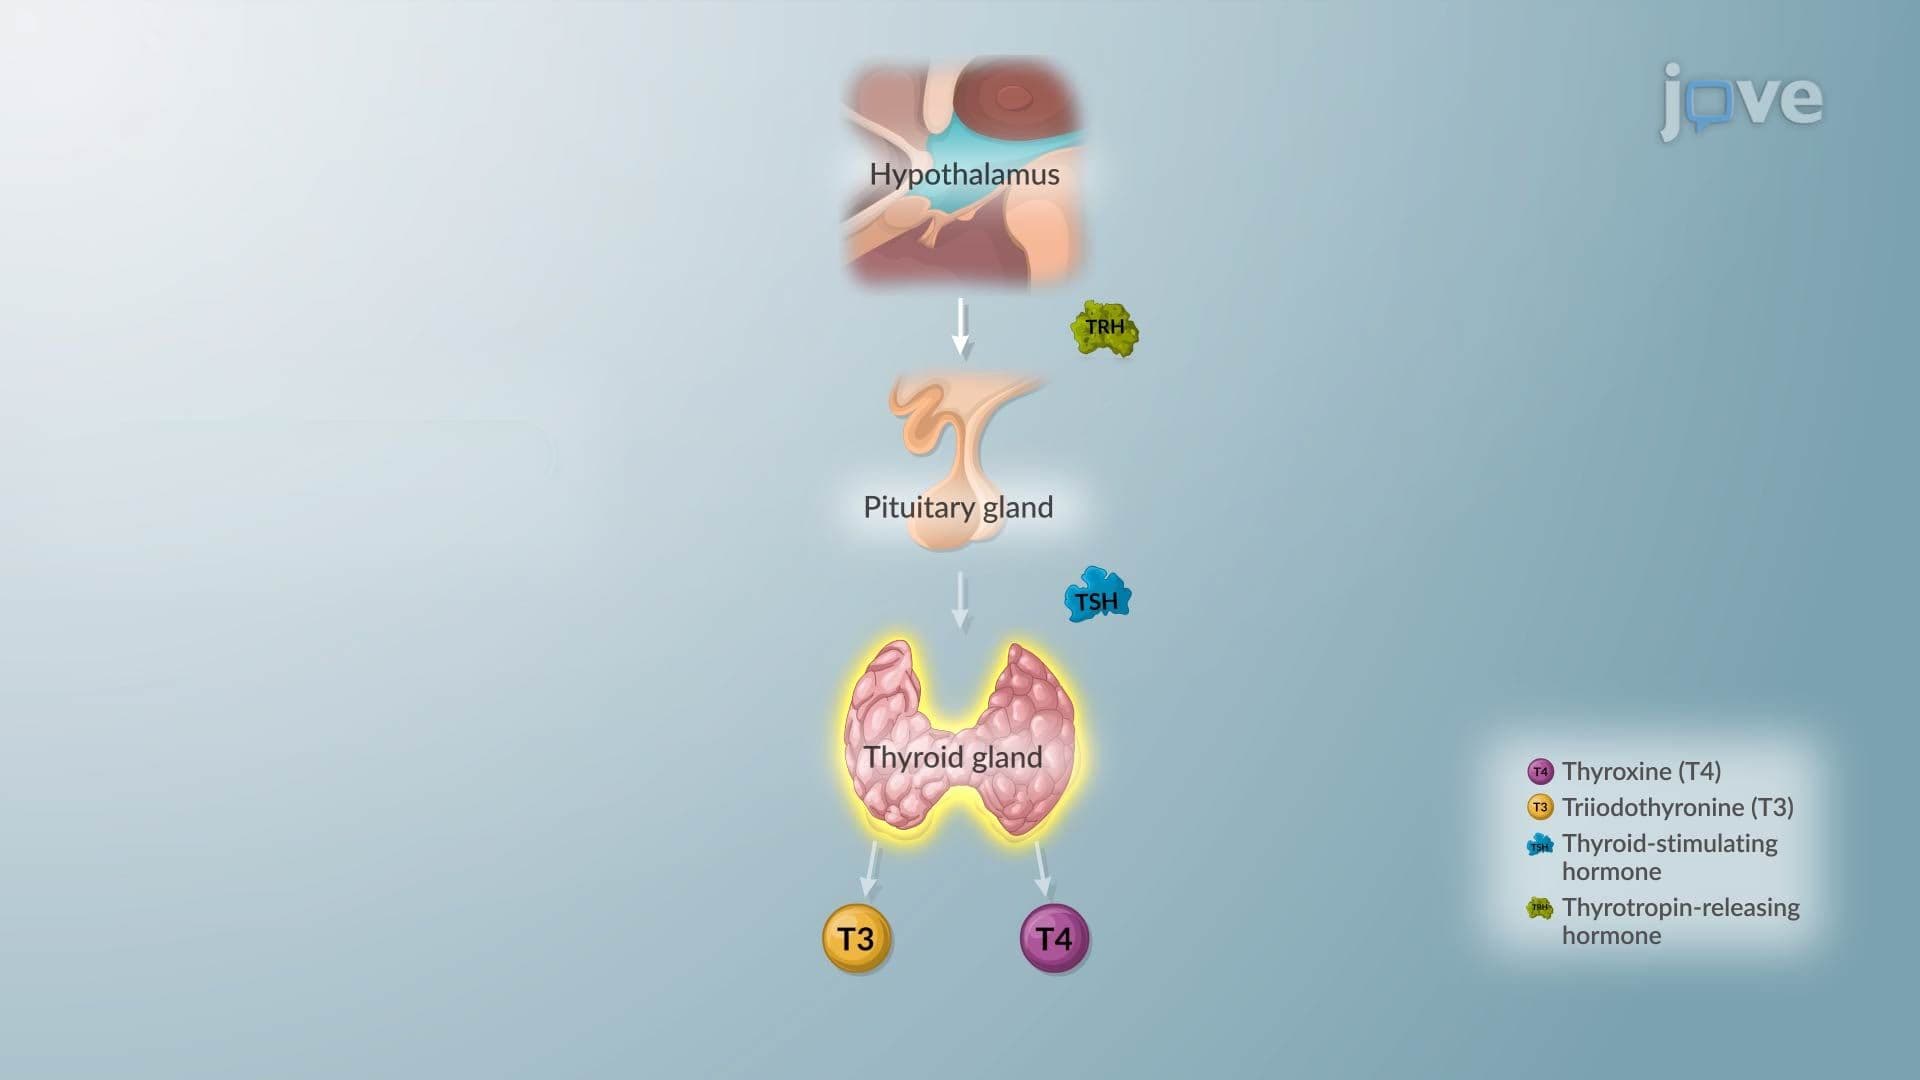
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The...