Related Experiment Video
Updated: May 5, 2026

Author Spotlight: Ex Vivo OCT-Based Multimodal Imaging of Human Donor Eyes for Research into Age-Related Macular Degeneration
Published on: May 26, 2023
Multimodal imaging in persistent placoid maculopathy
Mohamed G Gendy1, Amani A Fawzi1, Robert T Wendel2
1Department of Ophthalmology, Feinberg School of Medicine, Northwestern University, Chicago, Illinois.

Importance:
Persistent placoid maculopathy (PPM) is a rare clinical entity with features that superficially resemble acute posterior multifocal placoid pigment epitheliopathy (APMPPE) and macular serpiginous choroidopathy. It is important to differentiate PPM from APMPPE because both conditions may appear similar at presentation.
Objective:
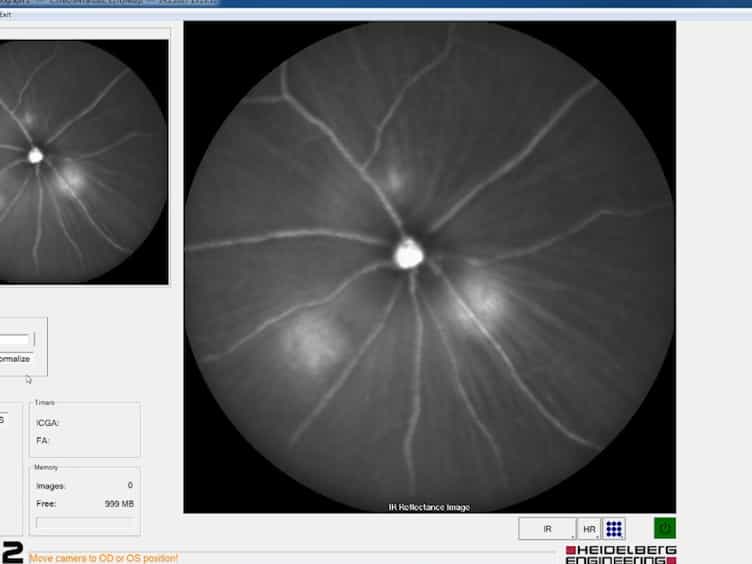
To investigate the short-term and long-term retinal changes in patients with PPM using spectral domain optical coherence tomography (SD-OCT), indocyanine green angiography (ICG-A), fluorescein angiography (FA), and fundus autofluorescence (FAF).
Design, Setting, And Participants:
We performed a retrospective medical record review in 5 patients diagnosed as having PPM at tertiary retinal practices.
Main Outcomes And Measures:
Findings on SD-OCT, FA, digital FAF, and ICG-A images.
Results:
Patients presented within 2 weeks of subjective symptoms. Mean best-corrected visual acuity was 20/144 (range, 20/25-20/400). At presentation, all but 1 patient had bilateral macular lesions. Four eyes developed extramacular lesions during follow-up. On SD-OCT, the acute placoid lesions revealed hyperreflectivity of the outer nuclear layer; disruption of the external limiting membrane, ellipsoid layer, and interdigitation zone; and, in some patients, hyporeflective spaces at the level of absent outer segments. On follow-up, lesions revealed either partial or complete restoration of the outer retinal architecture or they progressed to atrophy. On FA, all placoid lesions were hypofluorescent in early frames and hyperfluorescent in late frames. In the acute stage, ICG-A revealed sharply delineated dense hypofluorescent lesions, which persisted on late frames in all patients. Hypofluorescent lesions faded completely or partially after resolution of the placoid lesions on SD-OCT and clinical examination. Variability was seen on the FAF patterns; most lesions were hyperautofluorescent, except in 1 patient, in whom they were hypoautofluorescent. Bilateral choroidal neovascularization developed in only 1 patient. The mean follow-up was 28 weeks (range, 2-92 weeks). On the final follow-up visit, mean best-corrected visual acuity was 20/125 (range, 20/25-20/400).
Conclusions And Relevance:
On SD-OCT, acute retinal changes in PPM involve the outer nuclear layer, external limiting membrane, ellipsoid layer, and interdigitation zone. The retinal pigment epithelium and choroid are involved in severely affected patients. The variable extent of retinal pigment epithelium involvement was reflected in variable FAF findings. We discuss clinical features that differentiate this entity from other white spots, including acute placoid multifocal pigment epitheliopathy. Additional long-term imaging studies are needed to further clarify the exact location and pathogenesis of this rare disease.
Insights
Persistent placoid maculopathy (PPM) causes outer retinal changes visible on OCT. Imaging reveals outer nuclear layer and ellipsoid zone disruption, aiding differentiation from similar conditions.
Area of Science:
- Ophthalmology
- Retinal Imaging
- Macular Diseases
Background:
- Persistent placoid maculopathy (PPM) is a rare condition that can mimic acute posterior multifocal placoid pigment epitheliopathy (APMPPE).
- Accurate differentiation is crucial due to potential similarities in initial presentation.
Observation:
- This study retrospectively reviewed 5 patients diagnosed with PPM.
- Short-term and long-term retinal changes were evaluated using spectral domain optical coherence tomography (SD-OCT), fluorescein angiography (FA), indocyanine green angiography (ICG-A), and fundus autofluorescence (FAF).
Findings:
- SD-OCT revealed outer nuclear layer, external limiting membrane, ellipsoid layer, and interdigitation zone disruption in acute PPM lesions.
- FA showed hypofluorescence in early frames and hyperfluorescence in late frames.
- ICG-A demonstrated persistent hypofluorescent lesions.
- FAF patterns varied, with most lesions being hyperautofluorescent.
- Some patients experienced outer retinal architecture restoration, while others developed atrophy or choroidal neovascularization.
Implications:
- SD-OCT findings highlight specific outer retinal layer involvement in PPM.
- Imaging modalities like FA, ICG-A, and FAF provide distinct diagnostic clues.
- Further long-term studies are necessary to fully elucidate the pathogenesis of PPM.