Related Experiment Video
Updated: May 5, 2026

A Method for Screening and Validation of Resistant Mutations Against Kinase Inhibitors
Published on: December 7, 2014
Safety and efficacy of vemurafenib in end stage renal failure
Mahesh Iddawela1, Sarah Crook, Leah George
1Goulburn Valley Health, Graham Street, Shepparton 3630, Australia. Mahesh.Iddawela@unimelb.edu.au.

Background:
Serine-threonine inhibitors, such as vemurafenib, are being used increasingly in cancer treatment, and the toxicity and therapeutic benefit need to be balanced carefully both before and during treatment.
Case Presentation:
A patient with metastatic melanoma and end stage renal failure who was on peritoneal dialysis was treated with the serine-threonine kinase inhibitor, vemurafenib. After 5 months of treatment, a substantial response to vemurafenib was observed using imaging, but when he developed a prolonged QTc interval (common toxicity criteria (CTC) grade 3), treatment was interrupted. Vemurafenib was restarted at a reduced dose when the QTc interval returned to normal. The patient has had a significant response to vemurafenib and continued on treatment for 12 months after beginning the therapy.
Conclusion:
This is the first reported case of end stage renal failure in a patient who is taking vemurafenib. Although the patient developed QTc prolongation, it appears to be asymptomatic, and was managed with dose reduction. This case highlights the need for closer QTc monitoring at the start and during treatment.
Insights
Vemurafenib, a serine-threonine kinase inhibitor, effectively treated metastatic melanoma in a patient with end-stage renal failure. Careful QTc monitoring and dose adjustment managed toxicity, enabling continued therapeutic benefit.
Area of Science:
- Oncology
- Pharmacology
- Nephrology
Background:
- Serine-threonine kinase inhibitors like vemurafenib are increasingly used in cancer therapy.
- Balancing toxicity and therapeutic benefit is crucial during cancer treatment.
Observation:
- A patient with metastatic melanoma and end-stage renal failure on peritoneal dialysis received vemurafenib.
- Imaging revealed a substantial response after five months, but treatment was paused due to QTc interval prolongation (CTC grade 3).
- Vemurafenib was restarted at a reduced dose after QTc normalization, with continued significant response.
Findings:
- This is the first reported case of vemurafenib use in a patient with end-stage renal failure.
- Asymptomatic QTc prolongation was successfully managed through dose reduction.
- The patient experienced a significant treatment response over 12 months.
Implications:
- Highlights the importance of vigilant QTc interval monitoring in patients on vemurafenib, especially those with renal impairment.
- Demonstrates the feasibility of managing vemurafenib-induced QTc prolongation with dose adjustments.
- Suggests vemurafenib can be a viable treatment option for metastatic melanoma in patients with end-stage renal failure under careful monitoring.
More Related Videos


Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:15
Renal Drug Excretion: Overview
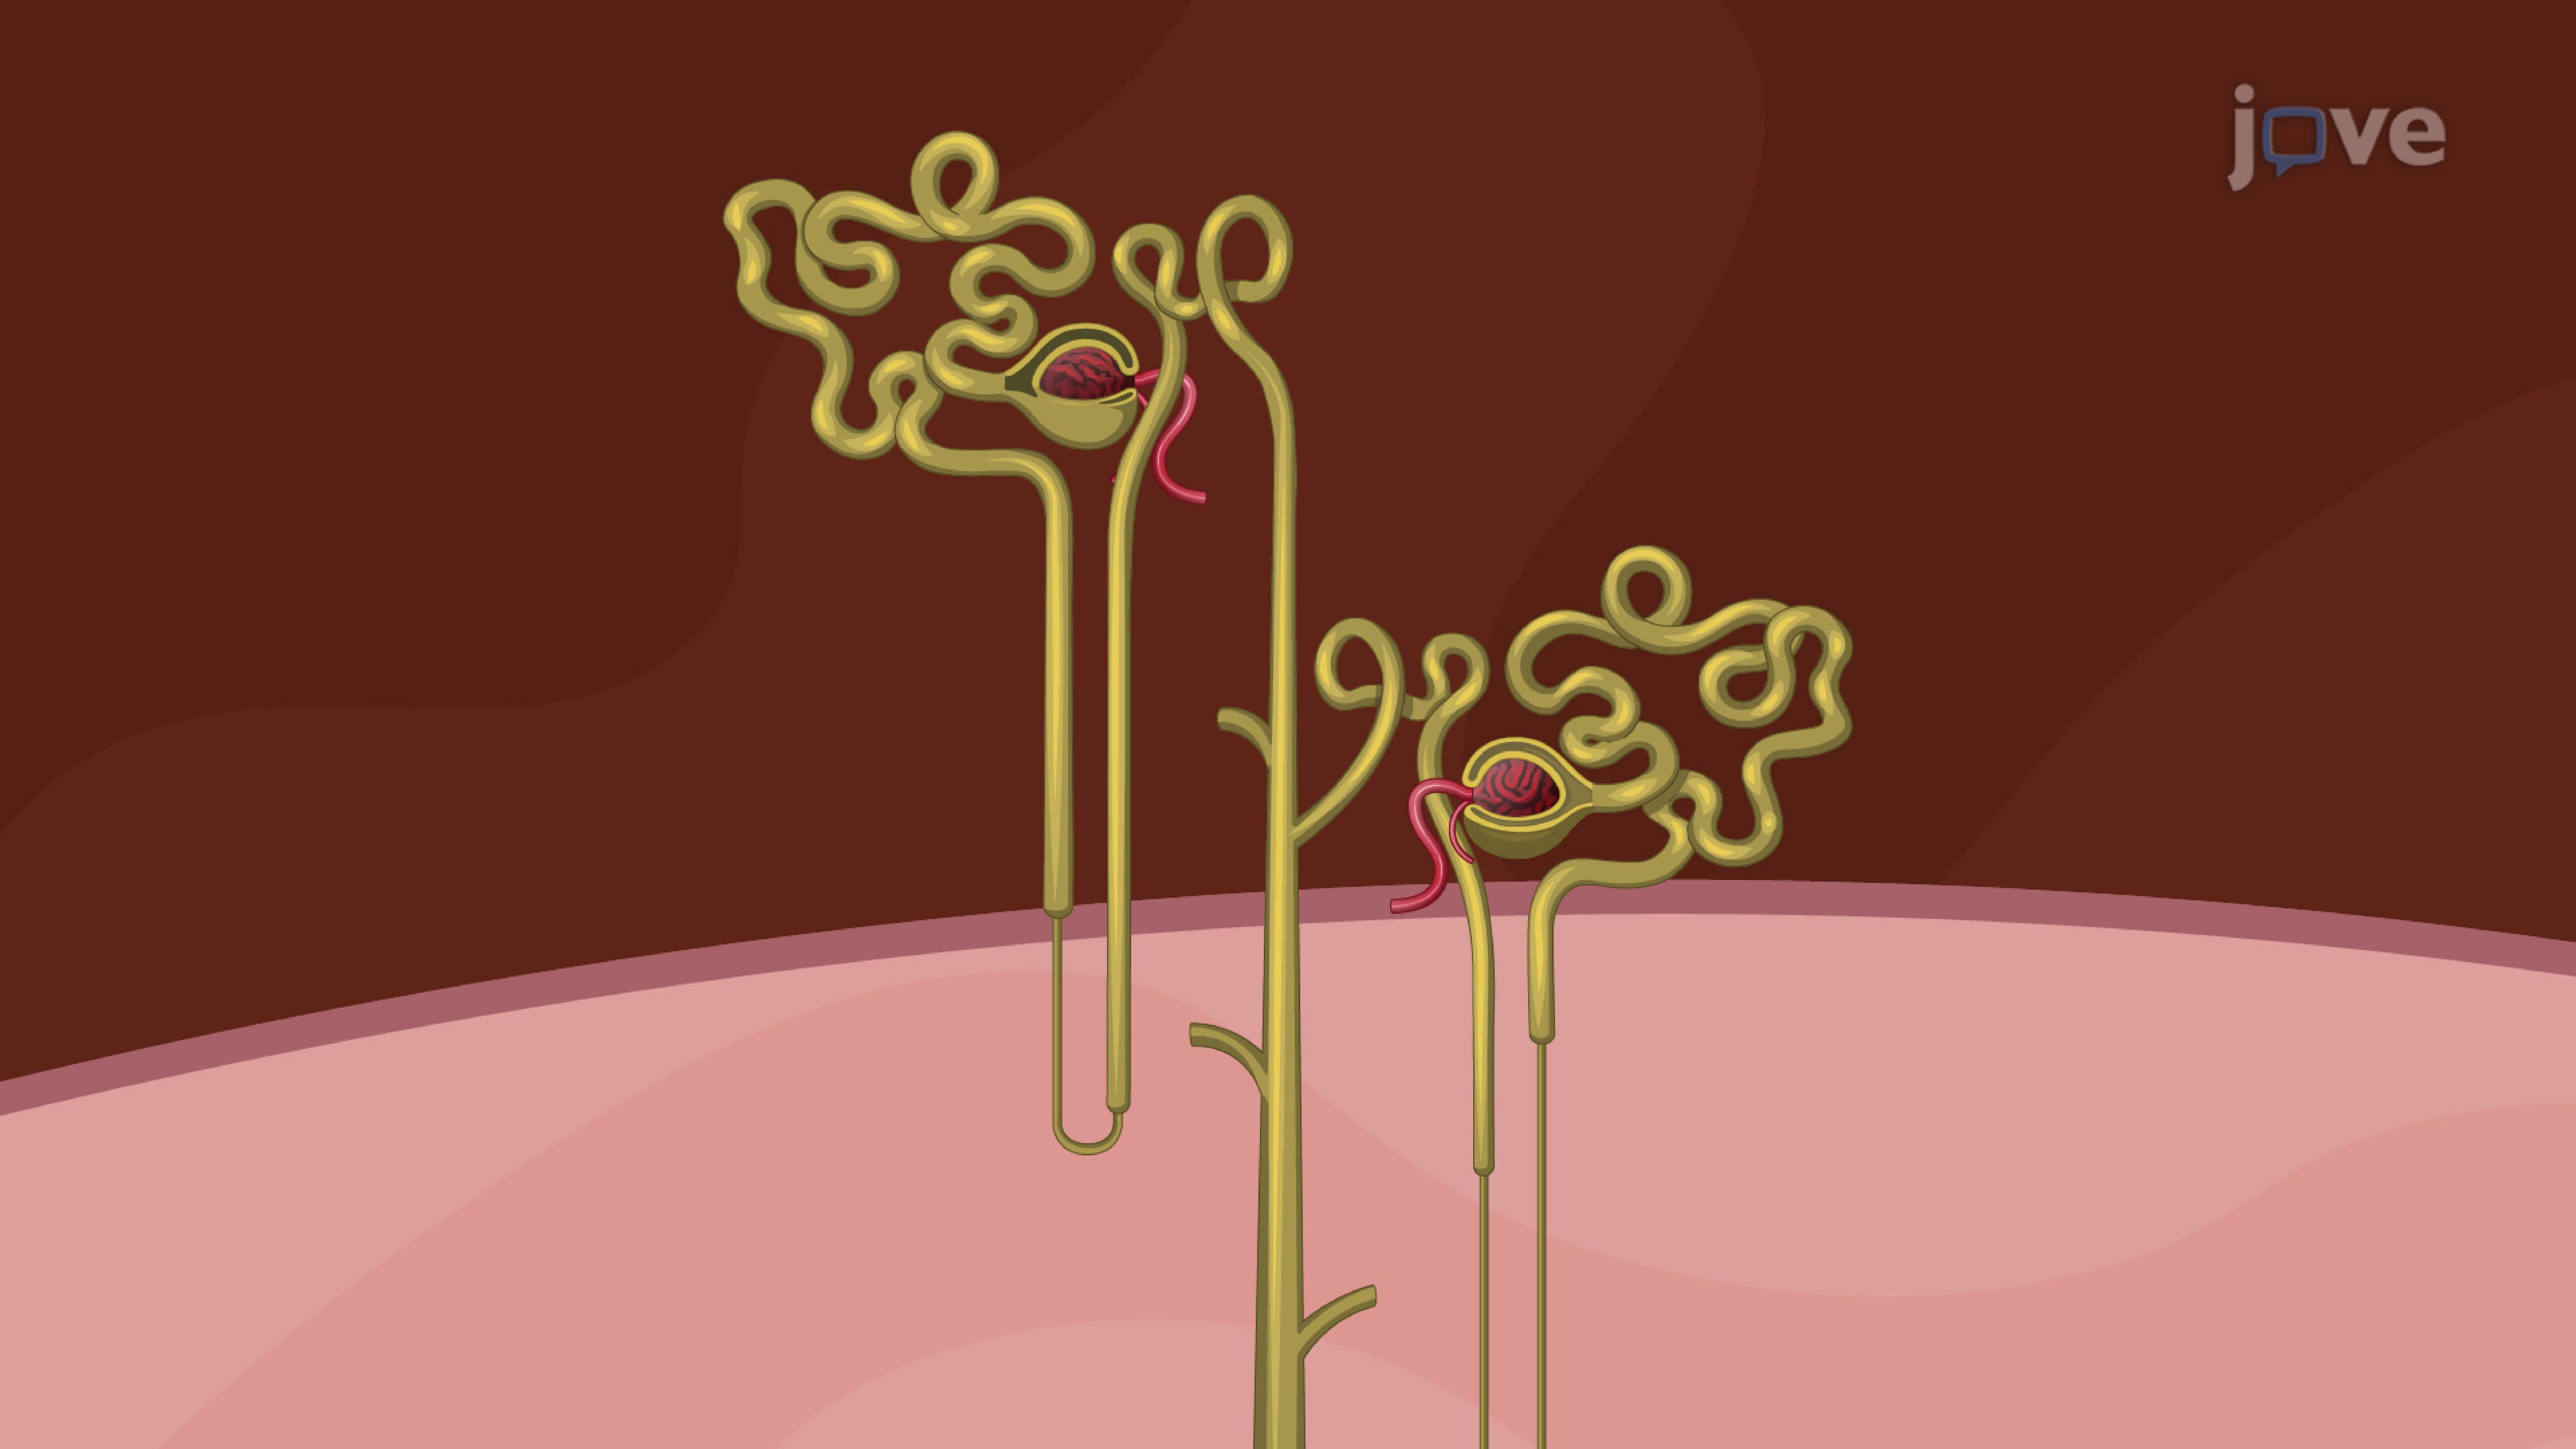
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:06
Renal Drug Clearance: Overview
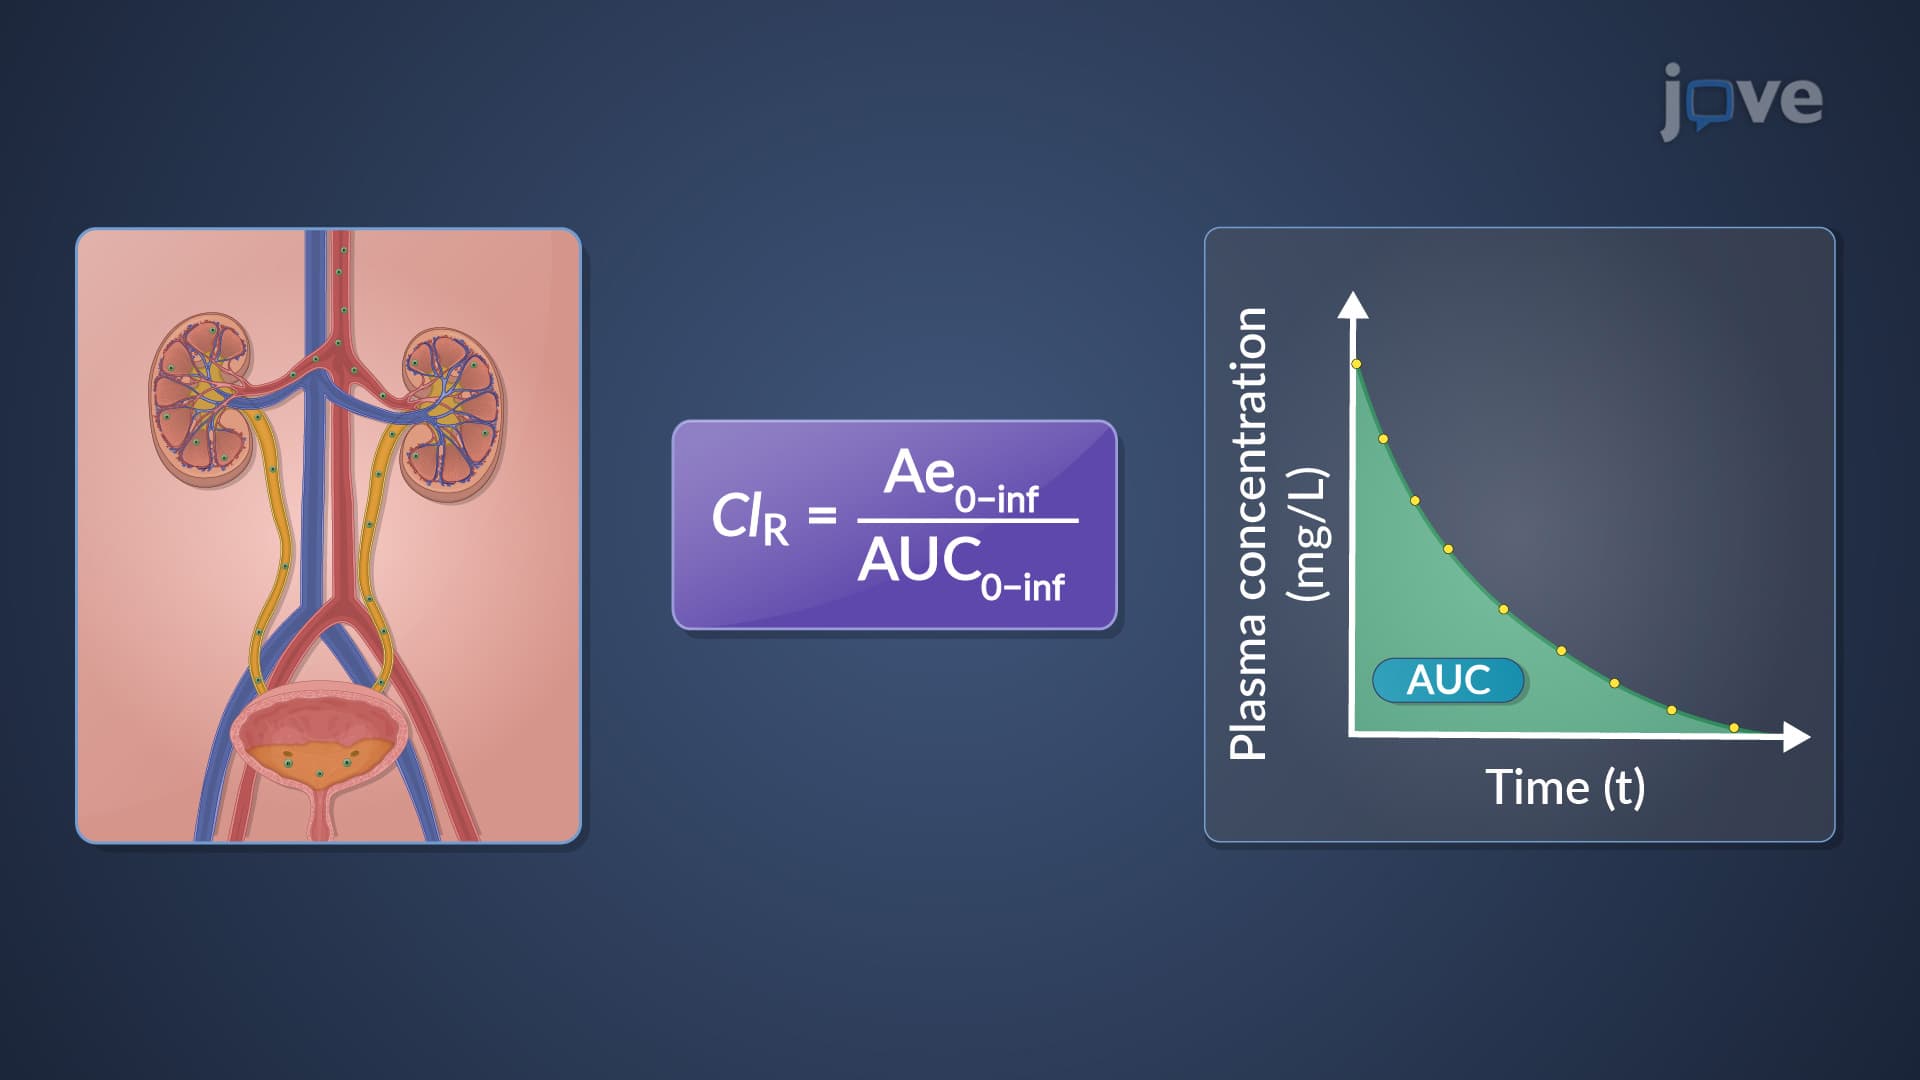
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:28
Renal Drug Excretion: Tubular Secretion
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration