Related Experiment Video
Updated: May 5, 2026


Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
[Control of blood pressure in hypertensive patients on combination therapy]
Alejandro de la Sierra1, Anna Oliveras2, Pedro Armario3
1Servicio de Medicina Interna, Hospital Mutua Terrassa, Universidad de Barcelona, Barcelona, España.

Insights
Blood pressure control in patients on 2-3 antihypertensive drugs is 57%. Microalbuminuria and older age are linked to uncontrolled blood pressure (BP). Fixed-drug combinations improve BP control for those on three agents.
Area of Science:
- Cardiology
- Pharmacology
- Nephrology
Context:
- Hypertension management remains a challenge, with limited understanding of treatment efficacy.
- Optimizing blood pressure (BP) control in patients on multiple antihypertensive agents is crucial for reducing cardiovascular risk.
- Referral units manage complex hypertensive cases, necessitating evaluation of treatment strategies.
Purpose:
- To assess blood pressure (BP) control rates in hypertensive patients receiving two or three antihypertensive agents.
- To identify factors associated with BP control, including patient demographics and treatment regimens.
- To evaluate the impact of fixed-drug combinations versus separate administration on BP control.
Summary:
- A study of 1,337 hypertensive patients (mean age 63 years) on 2-3 antihypertensive drugs found 57% achieved BP control (<140/90mmHg).
- Lack of BP control was associated with older age (12% increased risk per decade) and microalbuminuria (64% increased risk).
- For patients on three agents, fixed-drug combinations (68% control) showed better BP control than separate administration (52% control; P=.025).
Impact:
- Findings highlight the prevalence of suboptimal BP control in patients on complex antihypertensive regimens.
- Identifies microalbuminuria as a significant barrier to achieving BP targets, suggesting closer monitoring.
- Supports the use of fixed-drug combinations for three-agent therapy to enhance blood pressure management and patient outcomes.
Background And Aim:
The impact of antihypertensive treatment on blood pressure (BP) control is fairly unknown. The aim of the study was to evaluate the degree of BP control and its relationship with treatment-related factors in hypertensive patients treated with 2 or 3 agents and attended in referral units.
Patients And Methods:
We studied 1,337 hypertensive subjects (41% women) with a mean age (SD) of 63 (12) years, who were receiving 2 or 3 antihypertensive drugs. The degree of BP control was estimated in a single visit by the proportion of patients with BP below 140/90mmHg.
Results:
BP was controlled in 767 patients (57%). Lack of BP control was related to older age (12% risk for each 10-year increase) and the presence of microalbuminuria (64% risk increase). In those treated with 2 agents, BP control was 61%, without differences between those treated with fixed-drug or free combinations. BP control in those treated with 3 agents was 55%, higher in those receiving 3 agents in a fixed-drug combination (68%) compared with those on 3 agents administered separately (52%; P=.025). Drug classes used in combinations did not influence the degree of BP control.
Conclusions:
The degree of BP control in patients treated with 2 or 3 agents is 57%. Microalbuminuria is related to a lack of BP control. In those receiving 3 agents, the use of fixed-drug combinations is associated with better BP control.


Related Concept Videos
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:18
Hypertension and Regulation of Blood Pressure
 01:23
Hypertension V: Nursing Management
 01:30
Blood Pressure
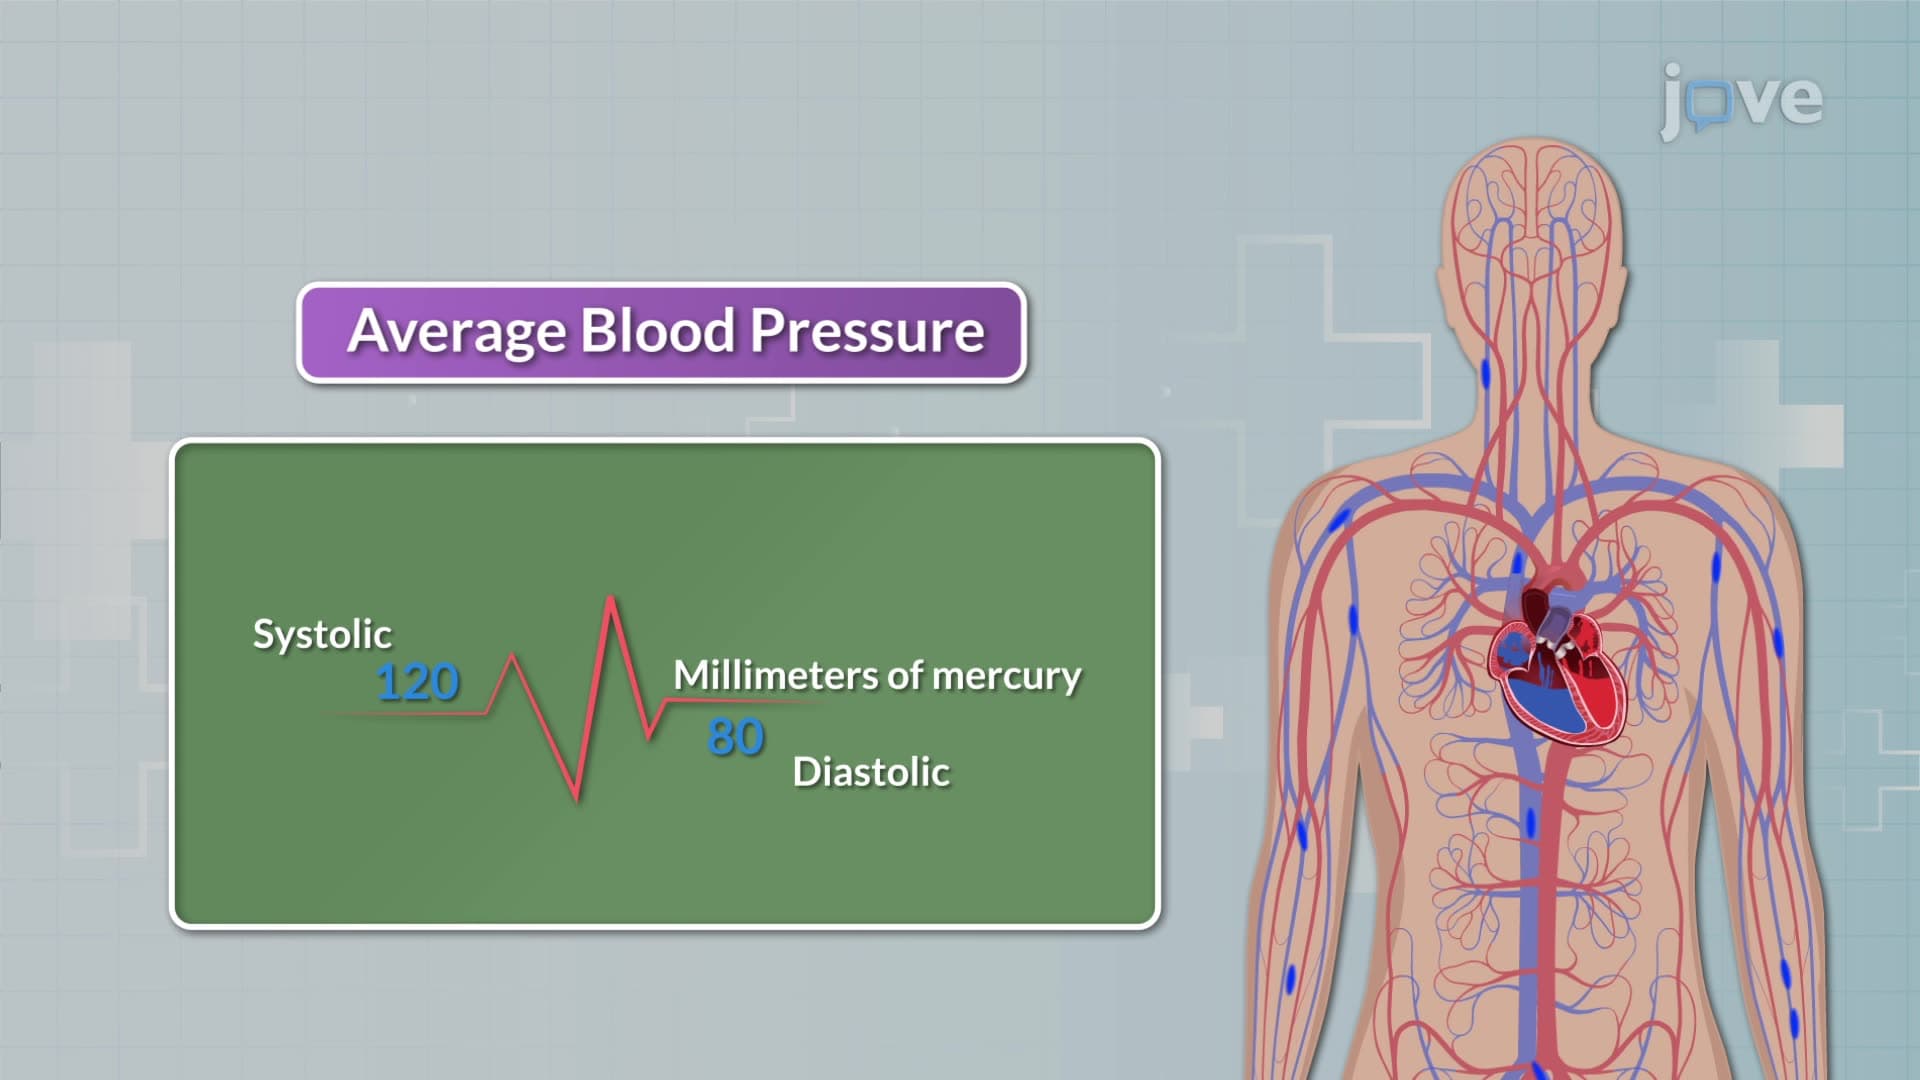
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:24
Blood Pressure
 01:29
Hypertension II: Pathophysiology