Related Experiment Video
Updated: May 5, 2026
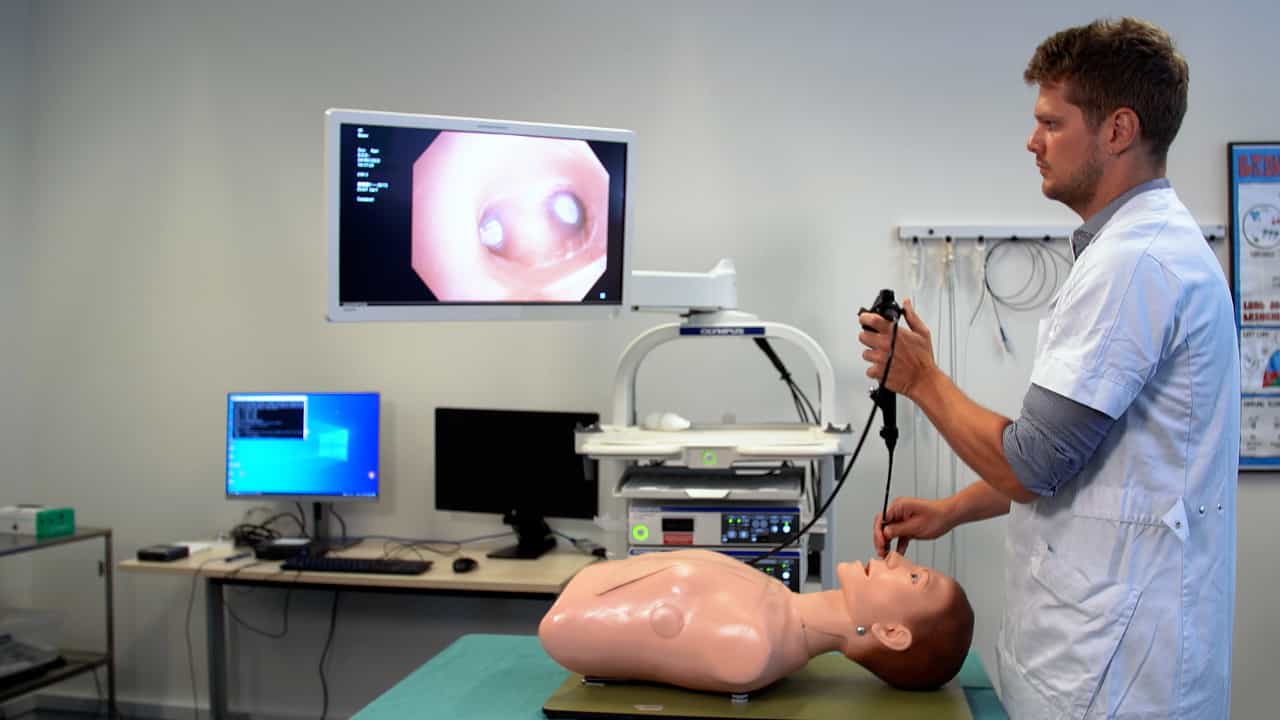
Author Spotlight: Learning Systematic Bronchoscopy in a Simulation-Base Setting
Published on: June 23, 2023
Hospitalist and nonhospitalist adherence to evidence-based quality metrics for bronchiolitis
Russell J McCulloh1, Sarah Smitherman, Solomon Adelsky
1Department of Pediatrics, Hasbro Children's Hospital, Providence, Rhode Island USA. rmcculloh@lifespan.org

Insights
Pediatric hospitalists demonstrate higher adherence to bronchiolitis care guidelines compared to non-hospitalists. This suggests improved quality of care for hospitalized children with bronchiolitis.
Area of Science:
- Pediatric Hospital Medicine
- Infectious Diseases
- Quality Improvement in Healthcare
Background:
- Hospitalists represent an emerging group of pediatric specialists.
- Limited data exist comparing the quality of care provided by hospitalists versus non-hospitalists.
- Bronchiolitis serves as a suitable condition for assessing inpatient pediatric care quality.
Purpose of the Study:
- To establish quality indicators for the evaluation and management of pediatric bronchiolitis based on American Academy of Pediatrics guidelines.
- To compare adherence rates to these quality indicators between hospitalists and non-hospitalists.
Main Methods:
- Retrospective chart review of children admitted with bronchiolitis to two academic centers (2007-2008).
- Data collection focused on evaluation, treatment, length of stay, readmission, and adverse outcomes.
- Analysis of 713 patient charts.
Main Results:
- Hospitalists and non-hospitalists showed similar discontinuation rates for albuterol and racemic epinephrine when there was no objective response.
- Hospitalists were significantly more likely to discontinue unnecessary systemic corticosteroid therapy (75.0% vs. 42.4%, P = .001).
- Hospitalists also demonstrated higher rates of discontinuing unnecessary antibiotic therapy (71.0% vs. 48.6%, P = .007).
Conclusions:
- Hospitalists exhibit superior adherence to specific American Academy of Pediatrics bronchiolitis guidelines.
- This improved adherence suggests a higher quality of inpatient care provided by hospitalists for bronchiolitis.
- The identified quality indicators effectively differentiate physician performance in managing pediatric bronchiolitis.
Objectives:
Hospitalists are a new subgroup of pediatricians. However, data comparing quality of care between hospitalists and nonhospitalists are limited. Bronchiolitis, a common cause of pediatric hospital admission, is an appropriate condition for evaluating inpatient quality of care. The goal of this study was to identify quality indicators for the evaluation and treatment of children hospitalized with bronchiolitis based on the 2006 American Academy of Pediatrics guidelines and to assess differences in adherence rates to these indicators between hospitalist and nonhospitalist pediatricians.
Methods:
This was a retrospective chart review of children admitted to 2 academic centers in 2007 and 2008. Reviewers selected charts with a discharge diagnosis of bronchiolitis and collected data on evaluation, treatment, length of stay, readmission, and adverse outcomes.
Results:
Reviewers analyzed 713 charts. In children without objective response to bronchodilator therapy, hospitalists and nonhospitalists discontinued albuterol and racemic epinephrine similarly. Hospitalists discontinued unnecessary systemic corticosteroid therapy (75.0% vs 42.4%; P= .001) and antibiotic therapy (71.0% vs 48.6%; P= .007) more frequently than nonhospitalists.
Conclusions:
These data suggest hospitalists better adhere to selected portions of the American Academy of Pediatrics bronchiolitis guidelines, thus providing higher quality of care. Quality indicators used in this study can distinguish physician performance in the inpatient management of bronchiolitis.
Related Concept Videos
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:30
Pneumonia III: Complications and Assessment
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...