Related Experiment Video
Updated: May 4, 2026


Symmetric Bihemispheric Postmortem Brain Cutting to Study Healthy and Pathological Brain Conditions in Humans
Published on: December 18, 2016
Cerebral white matter disease is independently associated with BPSD in Alzheimer's disease
Nagaendran Kandiah1, Russell Chander2, Angeline Zhang2
1Dept of Neurology, National Neuroscience Institute, Singapore; Duke-NUS, Singapore.

Objectives:
To study the association between cerebral white matter disease and burden of behavioral and psychological symptoms (BPSD) among patients with moderate to severe AD.
Methods:
Patients with moderate to severe AD having undergone MRI brain, cognitive and behavioral evaluations were studied. BPSD was diagnosed based on established clinical guidelines. White matter hyperintensity (WMH) and medial temporal lobe atrophy (MTA) were quantified by a blinded rater.
Results:
122 AD patients were studied. Age [76.84 vs. 72.70, p = 0.014] and MMSE [11.69 vs. 15.16, p < 0.001] was significantly higher in patients with BPSD. BPSD patients demonstrated higher periventricular [5.44 vs. 4.21, p < 0.001], deep subcortical [5.07 vs. 3.43, p < 0.001], and total WMH [10.51 vs. 7.65, p < 0.001] compared to non-BPSD patients. Higher proportion of BPSD patients had WMH in the highest tertile of severity (82.22% vs. 45.45%, p < 0.001). After correcting for age, baseline cognition and degree of MTA, total WMH remained significantly associated with a diagnosis of BPSD [odds ratio: 1.45 (1.14-1.85; p = 0.002)]. With severe WMH, the association is significantly increased [odds ratio: 4.3 (1.3-12.5); p = 0.016].
Conclusion:
WMH is independently associated with BPSD in moderate to severe AD. Optimizing vascular risk factors may be a strategy to reduce the severity of BPSD in AD.
Insights
Cerebral white matter disease, specifically white matter hyperintensity (WMH), is linked to behavioral and psychological symptoms in Alzheimer's disease (AD). Managing vascular risk factors may help reduce these symptoms in AD patients.
Area of Science:
- Neurology
- Neuroimaging
- Geriatrics
Background:
- Alzheimer's disease (AD) is a progressive neurodegenerative disorder.
- Behavioral and psychological symptoms of dementia (BPSD) are common in AD and significantly impact patient care and quality of life.
- Cerebral white matter disease, particularly white matter hyperintensity (WMH), is increasingly recognized as a relevant factor in AD pathophysiology.
Purpose of the Study:
- To investigate the association between the burden of cerebral white matter disease and the presence of BPSD in patients with moderate to severe AD.
- To determine if white matter hyperintensity (WMH) is an independent predictor of BPSD in this patient population.
Main Methods:
- A cohort of 122 patients with moderate to severe AD was analyzed.
- Magnetic resonance imaging (MRI) was used to quantify white matter hyperintensity (WMH) and medial temporal lobe atrophy (MTA).
- Behavioral and psychological symptoms of dementia (BPSD) were diagnosed using established clinical guidelines, and cognitive function was assessed using the Mini-Mental State Examination (MMSE).
Main Results:
- Patients with BPSD were older and had lower MMSE scores compared to those without BPSD.
- A significantly higher burden of periventricular, deep subcortical, and total white matter hyperintensity (WMH) was observed in patients with BPSD.
- After adjusting for age, baseline cognition, and medial temporal lobe atrophy (MTA), total WMH remained significantly associated with BPSD (OR: 1.45).
- Severe WMH showed a stronger association with BPSD (OR: 4.3).
Conclusions:
- White matter hyperintensity (WMH) is independently associated with behavioral and psychological symptoms of dementia (BPSD) in individuals with moderate to severe Alzheimer's disease.
- The findings suggest that optimizing vascular risk factors could be a potential strategy to mitigate the severity of BPSD in AD patients.
- Cerebral white matter disease represents a modifiable target for managing BPSD in Alzheimer's disease.
More Related Videos


Related Concept Videos
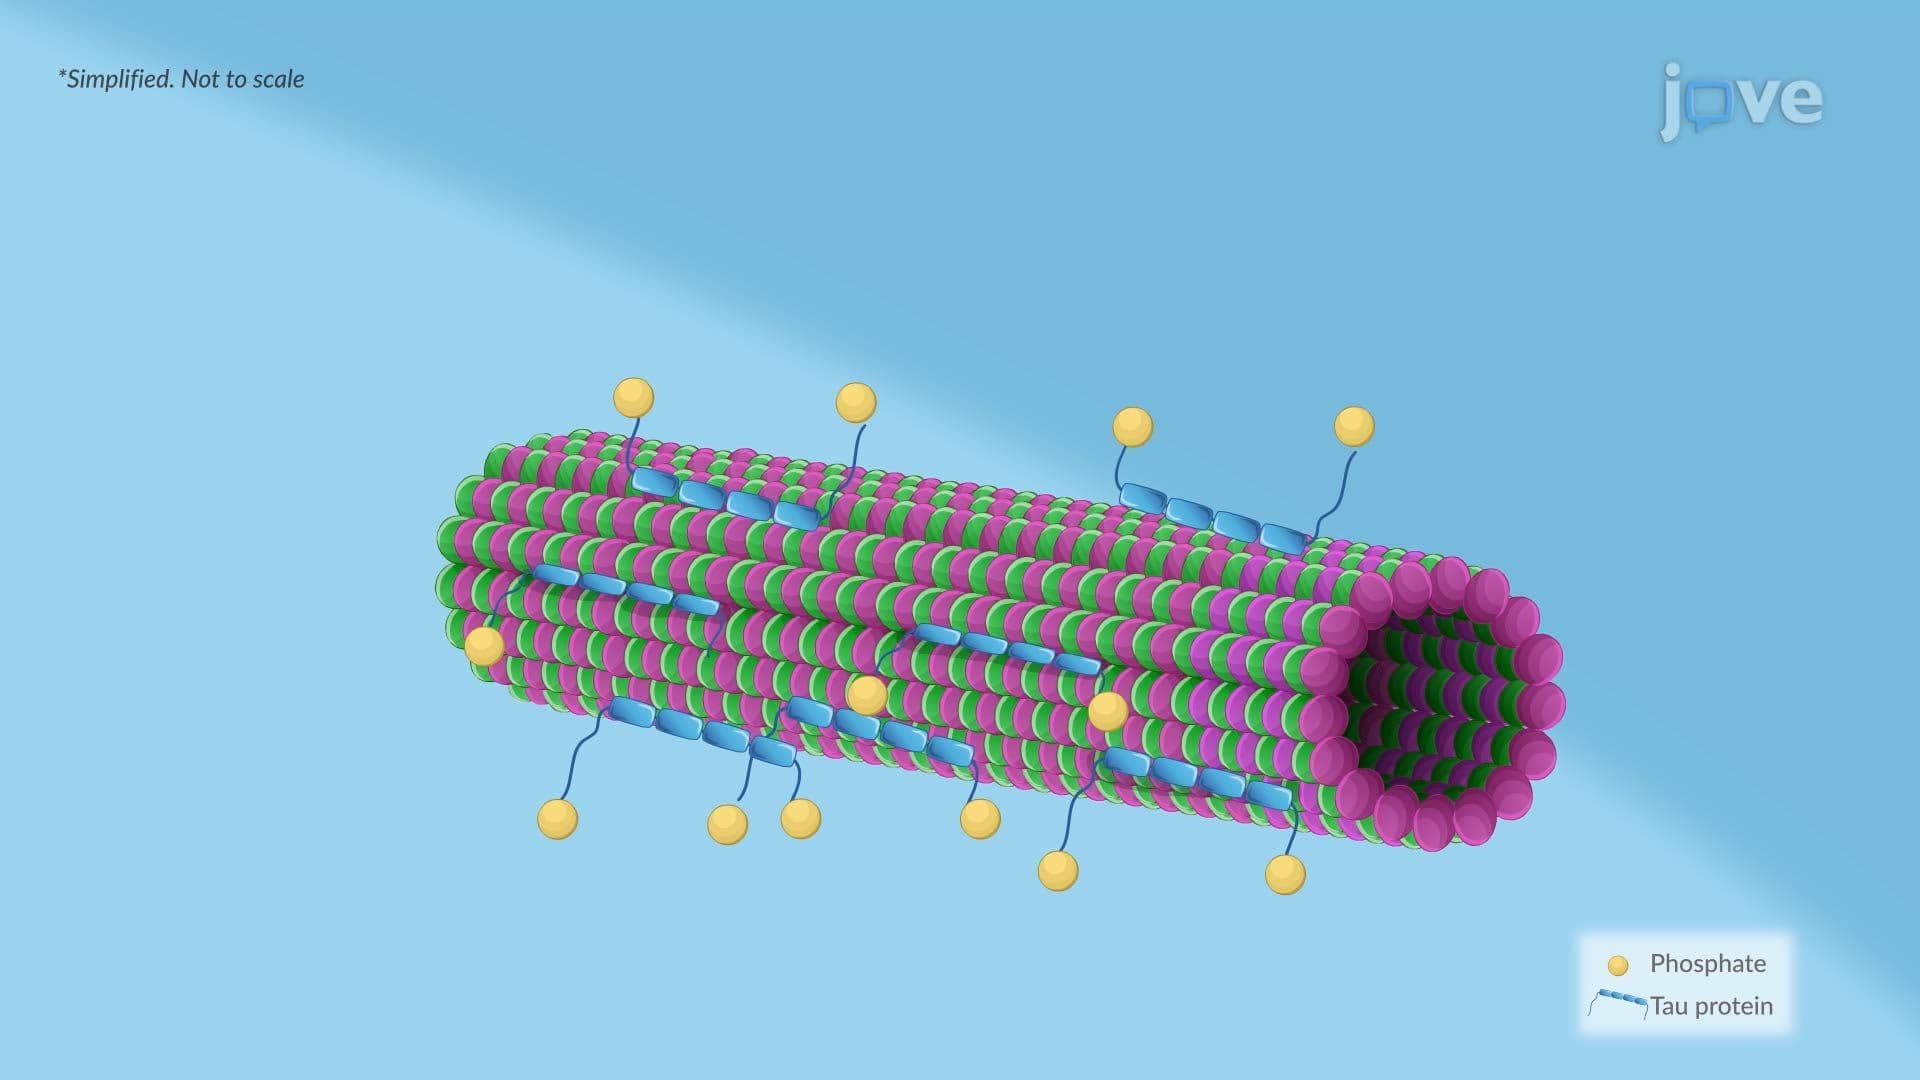 01:23
Alzheimer Disease ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology
 01:29
Alzheimer Disease l: Introduction
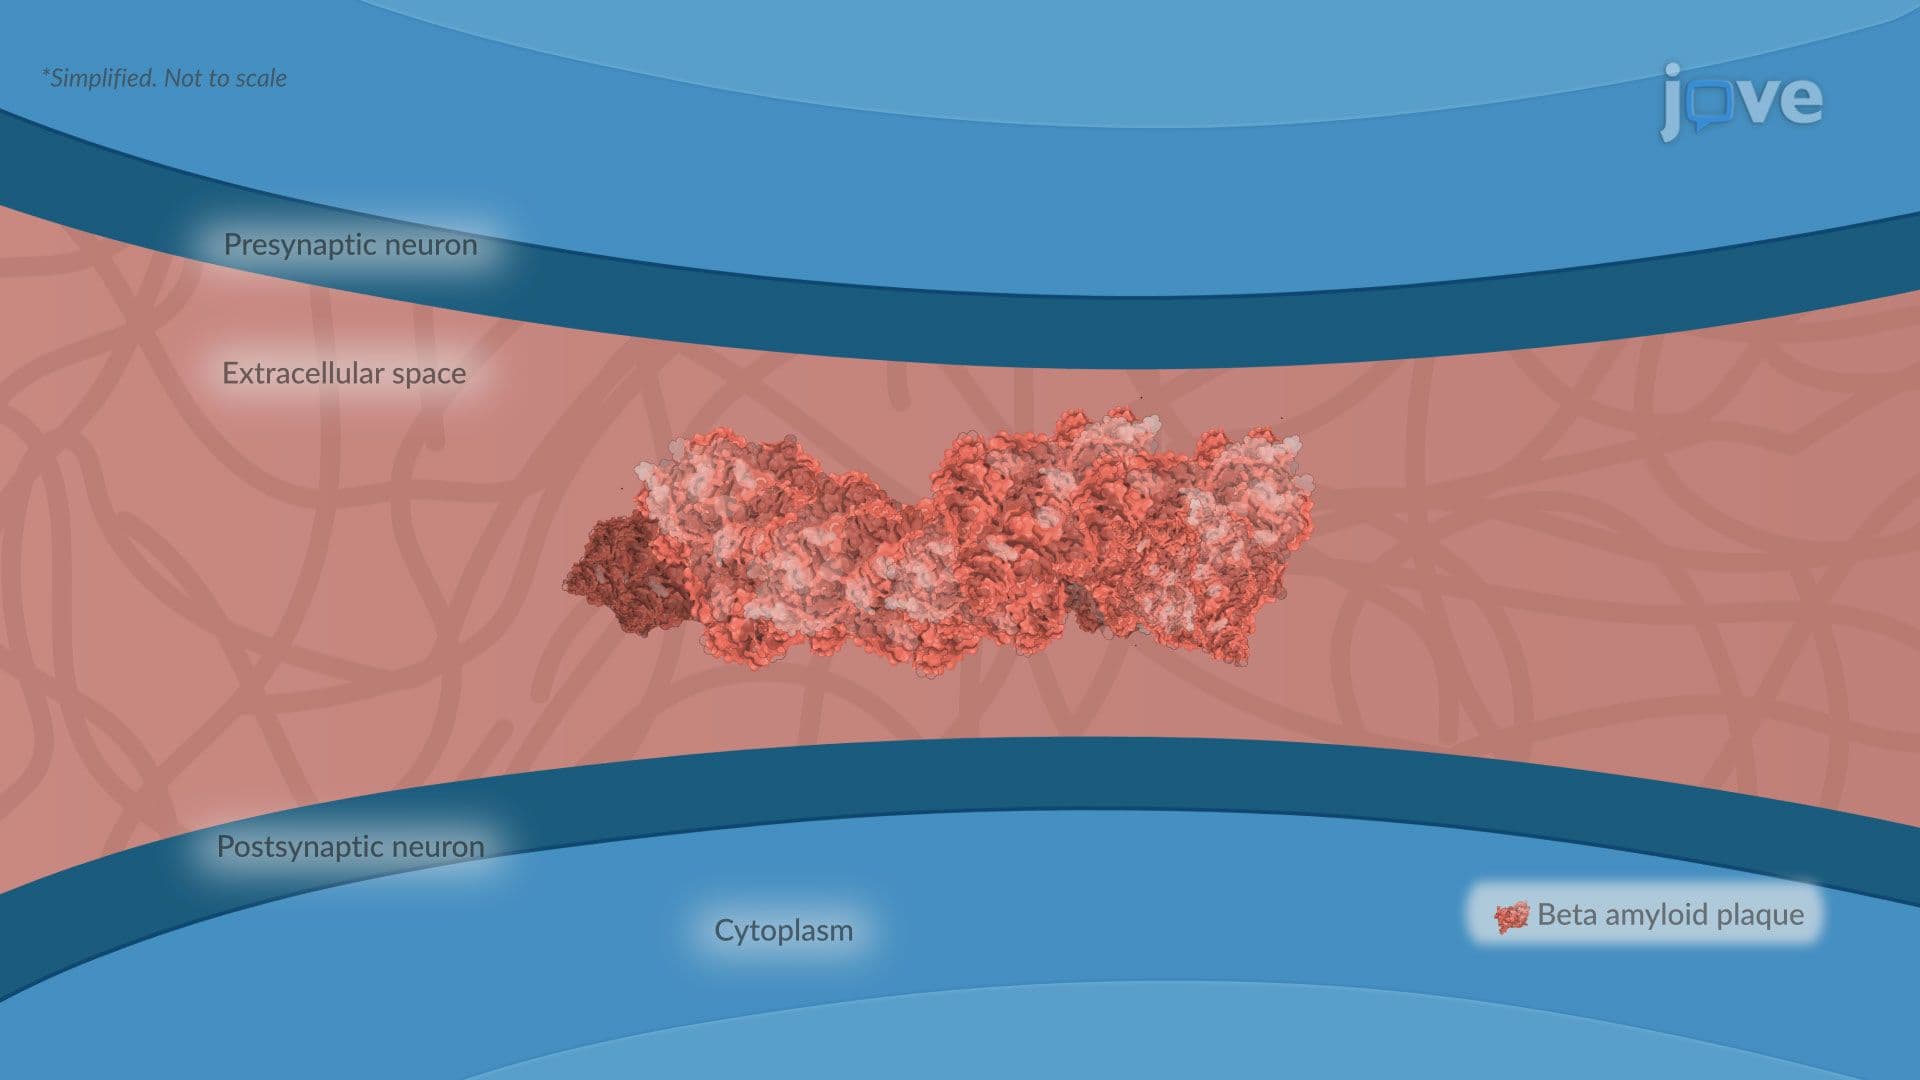 01:22
Dementia l: Introduction
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ...
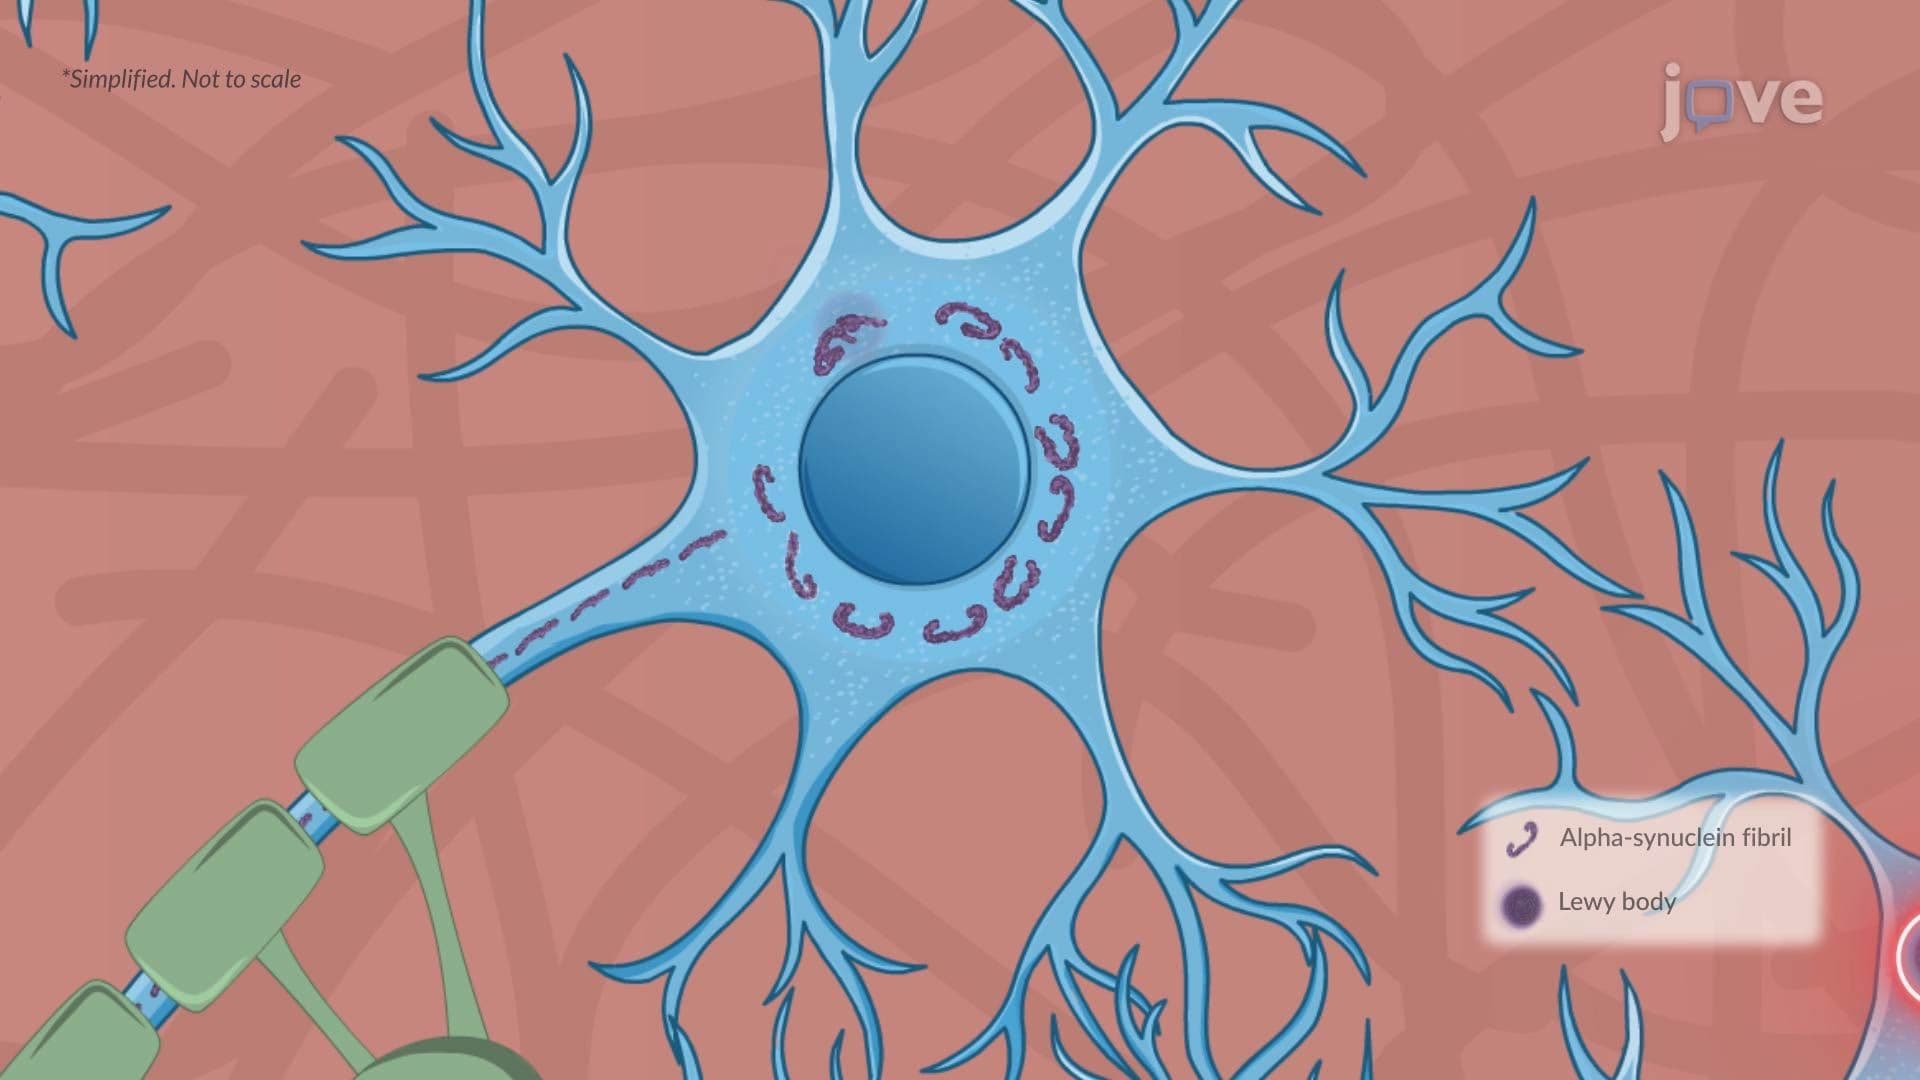 01:24
Parkinson Disease ll: Pathophysiology