Related Experiment Video
Updated: May 4, 2026
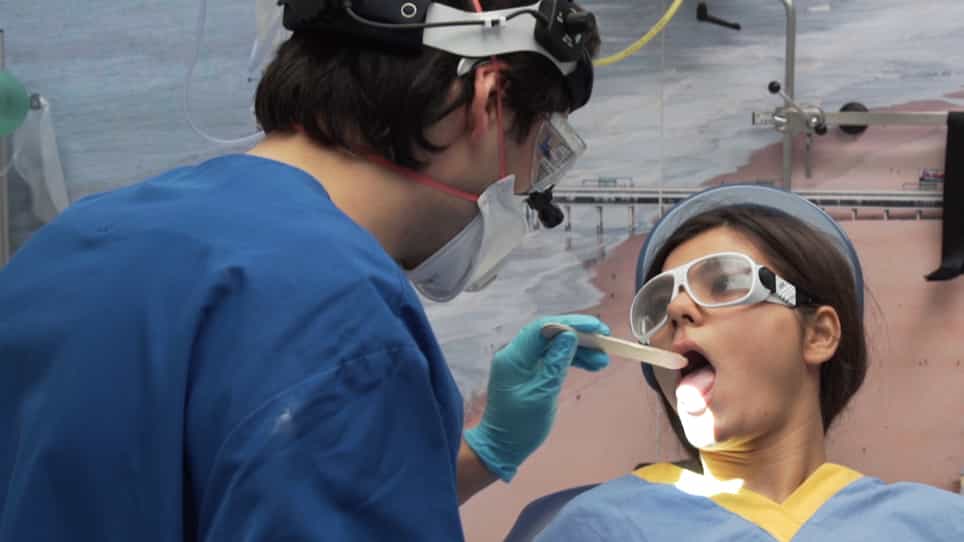

CO2-Lasertonsillotomy Under Local Anesthesia in Adults
Published on: November 6, 2019
High incidence of post-tonsillectomy secondary haemorrhage following coblation tonsillectomy
C V Praveen1, Subashini Parthiban1, R M Terry1
1Princess Royal University Hospital, Farnborough, Kent UK.

Abstract:
To examine the incidence of haemorrhage following tonsillectomy, to explore the usefulness of antibiotic in preventing postoperative haemorrhage and to examine if the haemorrhage depended on the level of expertise of the surgeon. A retrospective review analysing tonsillectomy method, the rate secondary haemorrhage, the grade of operating surgeon. A χ(2) analysis was used to determine the statistical difference between the haemorrhage rates of different tonsillectomy methods. One thousand three hundred and thirty-six tonsillectomies were performed during this period by four different methods: 615 by cold steel dissection, 582 by Coblation, 32 by bipolar dissection and 107 by Helica thermal coagulation. 621 tonsillectomies were performed by Consultant grade and middle grades performed 693 operations. 124 patients (9.3 %) were readmitted with haemorrhage. The secondary haemorrhage requiring surgery for controlling bleeding for cold steel dissection method was 1.5 % compared to 6.7 % for coblation method (P < 0.01 %), 6.3 % for bipolar dissection and 1.9 % for Helica thermal coagulation method. Overall consultants had a post tonsillectomy haemorrhage rate of 5.5 % and middle grades had a rate of 3.7 %. 86.5 % of the patients were already on routine prophylactic oral antibiotics at the time of presentation with haemorrhage needing surgical arrest and 13.5 % were not on antibiotics (P < 0.05 %). There was statistically significant difference in secondary haemorrhage rate between coblation and cold steel dissection methods. Coblation tonsillectomies had an increased need for operative intervention to control secondary haemorrhage. Routine use of antibiotic and expertise of operating surgeon had no bearing on secondary haemorrhage rate.

Related Concept Videos
 01:26
Tonsillitis II: Management
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:30
Tonsillitis I: Introduction
Etiology
Three primary contributing factors have been identified.
 01:29
Suctioning the Nasopharyngeal Airway
Equipment Required
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:30
Epistaxis
Etiology
Possible causes of this condition include high blood pressure, trauma, low humidity, upper respiratory tract infections, allergies, foreign bodies, nasal inhalation of corticosteroids or illicit drugs, excessive use of decongestant nasal sprays, facial or nasal surgery, anatomic malformation, tumors, or systemic...