Related Experiment Video
Updated: May 4, 2026
Multimodality Diagnosis of Mesenteric Ischemia
Published on: July 21, 2023
Giant Meckel diverticulum with enteroliths: a case report of a patient presenting with low back and episodic right
Alicia M Yochum1, Eve E Bonic2, Terry R Yochum3
1Diagnostic Imaging Resident, Logan University, Chesterfield, MO.

Objectives:
The purpose of this case report is to describe a patient who presented with low back pain and episodic right lower quadrant pain who had a long-standing giant Meckel diverticulum with enteroliths.
Clinical Features:
A 49-year-old woman presented to a chiropractic clinic with low back pain and history of intermittent right lower quadrant pain. Lumbar radiography demonstrated calcifications in the pelvic basin that changed position with changes in patient posture. The patient was referred to an abdominal surgeon for consultation and management.
Intervention And Outcome:
Computed tomography identified calcifications in the small bowel in the region of the ileocecal valve. The patient underwent prophylactic diverticulectomy with no complications. Gross pathology revealed a giant Meckel diverticulum measuring 24 inches (60.9 cm) containing 6 enteroliths.
Conclusions:
A timely diagnosis resulted in a favorable surgical outcome for this patient with long-standing giant Meckel diverticulum and enteroliths.
Related Concept Videos
 01:22
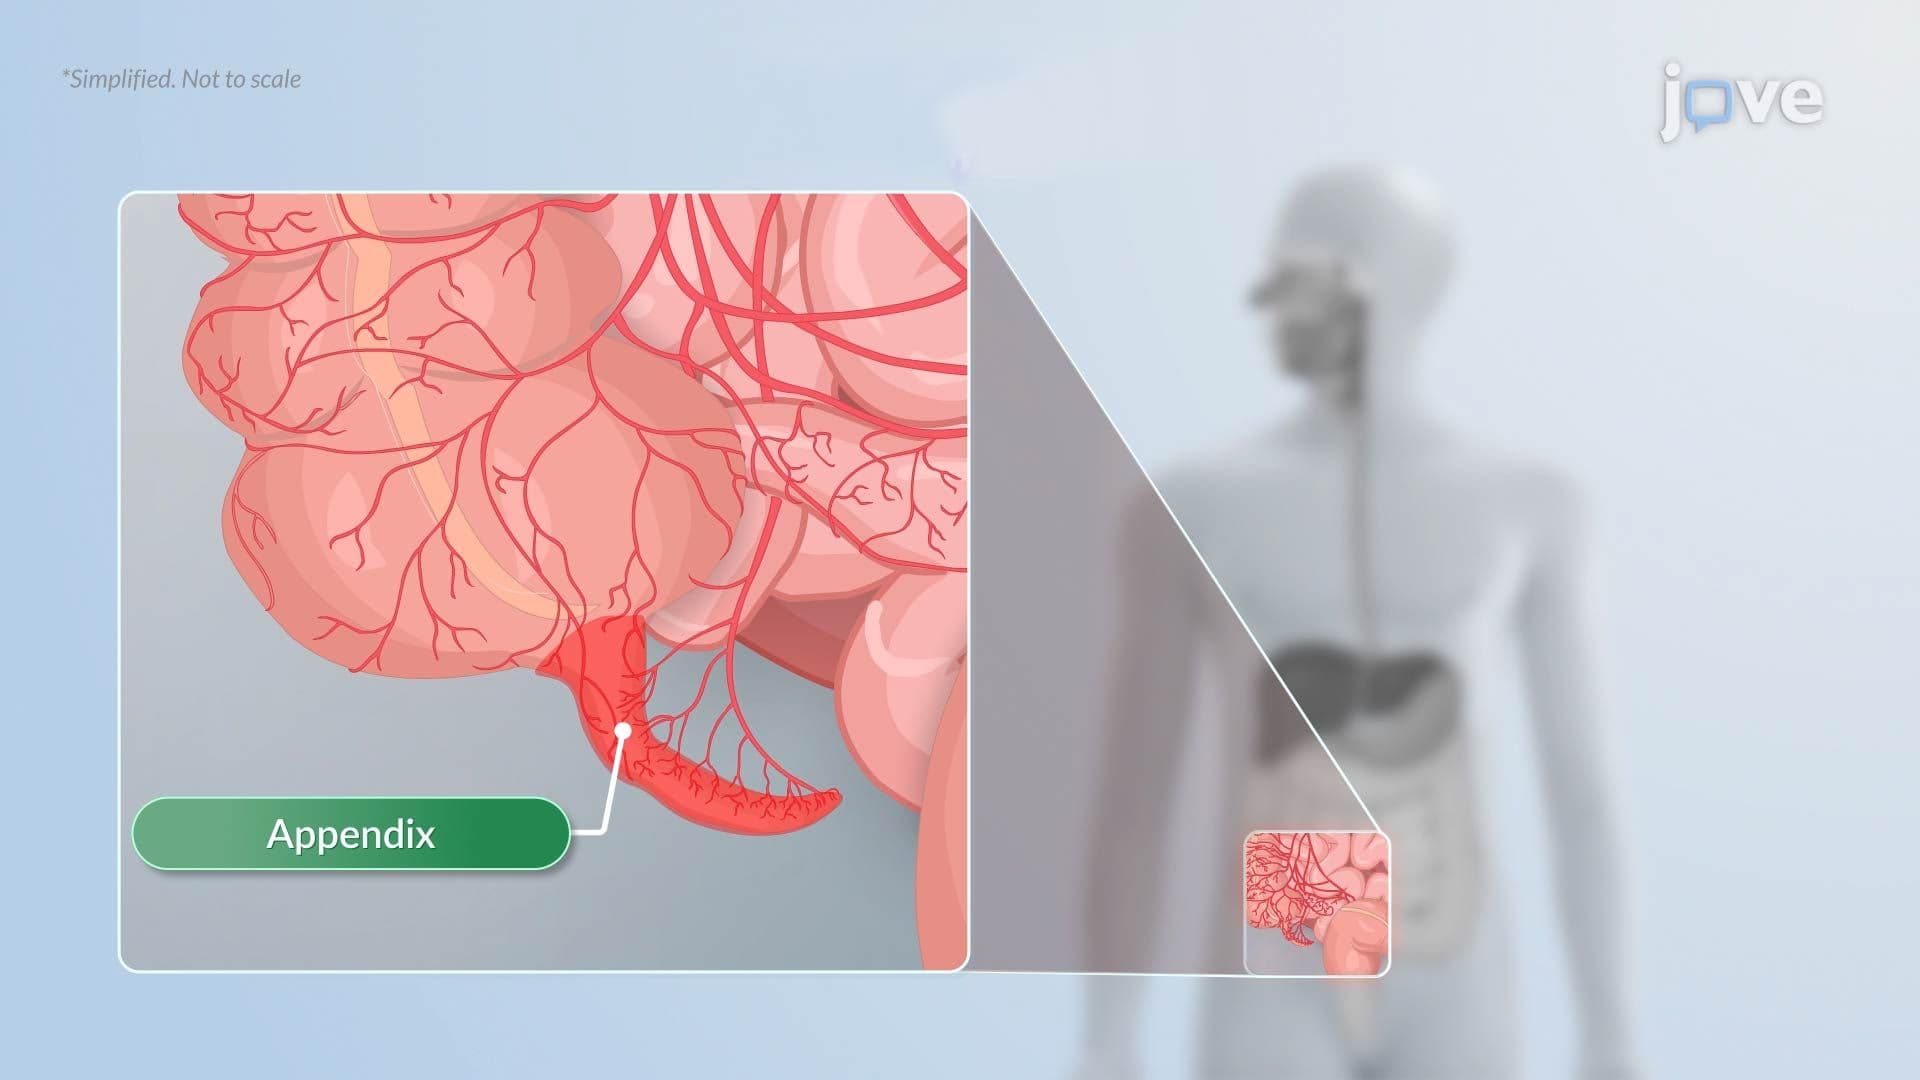
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:27
Diverticular Disease of the Colon
 01:19
Appendicitis
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:07
Intestinal Obstruction II: Pathophysiology