The comparative effectiveness of ventricular shunt placement versus endoscopic third ventriculostomy for initial treatment of hydrocephalus in infants
Related Experiment Video
Updated: May 4, 2026
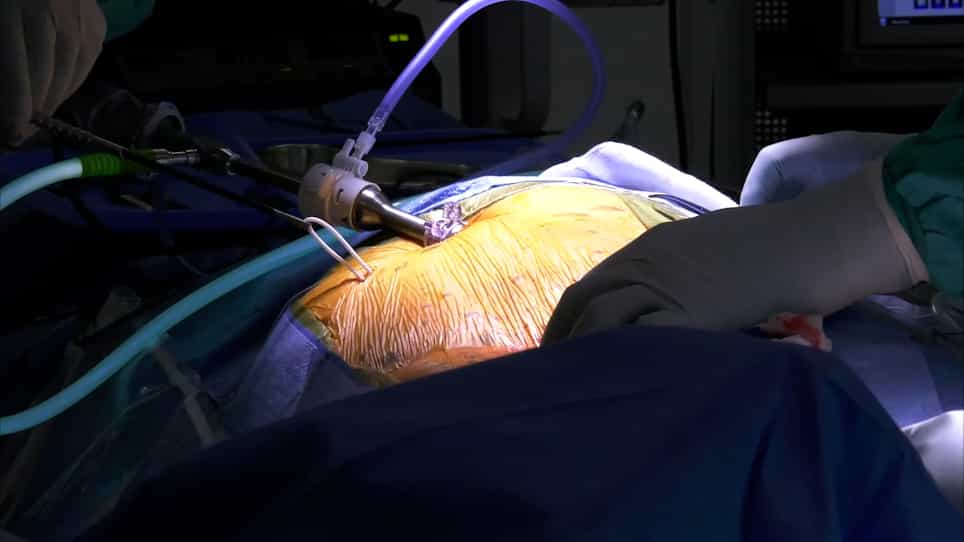
Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022
Sarah C Jernigan1, Jay G Berry, Dionne A Graham
1Department of Neurosurgery.

Insights
Endoscopic third ventriculostomy (ETV) shows higher failure rates for infant hydrocephalus compared to shunt placement within one year. This risk is particularly significant for procedures in the first 90 days of life.
Area of Science:
- Neurosurgery
- Pediatric Surgery
- Medical Technology
Background:
- Infantile hydrocephalus is a critical condition requiring cerebrospinal fluid (CSF) diversion.
- Endoscopic third ventriculostomy (ETV) and shunt placement are primary surgical interventions.
- Comparing the long-term effectiveness of these procedures in infants is crucial for optimal patient outcomes.
Purpose of the Study:
- To compare the 1-year effectiveness of CSF diversion between ETV and shunt therapy in infants with hydrocephalus.
- To analyze failure rates and identify factors influencing treatment outcomes.
Main Methods:
- Retrospective analysis of 5416 infants (≤1 year) with hydrocephalus undergoing ETV or shunt placement.
- Data collected from 41 children's hospitals between 2004-2009 via the Pediatric Health Information Systems database.
- Surgical failure defined as repeat diversion surgery within 1 year; hierarchical regression used for analysis.
Main Results:
- ETV was performed in 16.1% of infants, while shunt placement was used in 83.9%.
- Infants undergoing ETV had higher rates of prematurity and intraventricular hemorrhage.
- ETV demonstrated significantly higher 1-year operative failure rates (64.5%) compared to shunt placement (39.6%).
Conclusions:
- ETV is associated with a greater 1-year CSF diversion failure rate in infants with hydrocephalus compared to shunt placement.
- The increased risk of ETV failure is most pronounced for procedures performed within the first 90 days of life.
- Further research is needed on reoperation rates, costs, and surgeon/hospital experience to determine long-term treatment efficacy.
Object:
The purpose of this study was to compare the effectiveness of CSF diversion with endoscopic third ventriculostomy (ETV) versus shunt therapy in infants with hydrocephalus.
Methods:
The authors conducted a retrospective analysis of 5416 infants 1 year of age or younger with hydrocephalus (congenital or acquired) in whom CSF diversion was performed using either ETV or shunt placement at 41 children's hospitals between 2004 and 2009. Data were obtained from the Pediatric Health Information Systems database. Surgical failure was defined as the need for a repeat diversion operation within 1 year of initial surgery. The authors compared failure rates of ETV and shunt, as well as patient demographics and clinical characteristics, using hierarchical regression according to treatment group.
Results:
During the period examined, 872 infants (16.1%) initially underwent ETV and 4544 (83.9%) underwent ventricular shunt placement. The median infant age was 37 days (IQR 11-122 days) for both ETV and shunt placement. More infants who underwent ETV rather than shunt placement were born prematurely (41.6% vs 23.9%, respectively; p < 0.01) and had intraventricular hemorrhage (45.4% vs 17.5%, respectively; p < 0.01). Higher operative failure rates at 1 year were observed in infants who underwent ETV as opposed to shunt surgery (64.5% vs 39.6%, respectively; OR 2.9 [95% CI 2.3-3.5], p < 0.01). After controlling for prematurity, intraventricular hemorrhage, and spina bifida, ETV remained associated with a higher risk of failure (OR 2.6 [95% CI 2.1-3.2]).
Conclusions:
In infants with hydrocephalus, a greater 1-year CSF diversion failure rate may occur after ETV compared with shunt placement. This risk is most significant for procedures performed within the first 90 days of life. Further investigation of the need for multiple reoperations, cost, and impact of surgeon and hospital experience is necessary to distinguish which treatment is more effective in the long term.