Related Experiment Video
Updated: May 4, 2026
A Reproducible Intensive Care Unit-Oriented Endotoxin Model in Rats
Published on: February 20, 2021
Acute bacterial meningitis in the intensive care unit and risk factors for adverse clinical outcomes: retrospective
D Fernandes1, J Gonçalves-Pereira2, S Janeiro3
1Infectious Disease and Tropical Medicine Department, Egas Moniz Hospital, CHLO, Lisbon, Portugal; Polyvalent Intensive Care Unit, São Francisco Xavier Hospital, CHLO, Lisbon, Portugal.

Background:
Bacterial meningitis constitutes a medical emergency. Its burden has driven from childhood to the elderly and the immunocompromised population. However, the admission of patients with bacterial meningitis to the intensive care unit (ICU) has been sparsely approached, as have the prognostic factors associated with an adverse clinical outcome.
Methods:
We performed a retrospective analysis during a 7-year period of patients older than 18 years admitted to 2 polyvalent ICUs. Clinical, demographic, and outcome data were collected to evaluate its clinical impact on the outcome of patients with acute bacterial meningitis.
Results:
We identified 65 patients with the diagnosis of acute bacterial meningitis (mean Acute Physiology and Chronic Health Evaluation II, 23; hospital mortality, 40%). Upon clinical presentation, their most frequent signs were fever (84%), seizures (21.5%), and a low Glasgow Coma Scale (GCS) score (GCS<8; 58.4%). Fifty-five patients (85%) required organ support. A definite microbiological diagnosis was achieved in 45 patients. An adverse clinical outcome was noted in 46 patients (71%). These patients were older (P=.005), had higher Physiology and Chronic Health Evaluation II score (P=.022), and had lower GCS (P=.022). In the multivariate analysis, older age (per year; adjusted odds ratio [aOR], 1.059) was associated with an adverse outcome, whereas a higher GCS (per point; aOR, 0.826) and presence of fever upon admission (aOR, 0.142) increase the chance of a good recovery.
Conclusions:
Patients with acute bacterial meningitis admitted to ICU had substantial morbidity and mortality. Those with low GCS or absence of fever have a particularly high risk of an adverse outcome.
Insights
Bacterial meningitis in the ICU has high mortality. Low Glasgow Coma Scale (GCS) scores and absence of fever predict poor outcomes for these critically ill patients.
Area of Science:
- Critical Care Medicine
- Infectious Diseases
- Neurology
Background:
- Bacterial meningitis is a critical illness with significant morbidity and mortality.
- Limited research exists on intensive care unit (ICU) admissions for bacterial meningitis and associated prognostic factors.
- Understanding outcomes in immunocompromised and elderly populations is crucial.
Purpose of the Study:
- To investigate the clinical impact and prognostic factors of acute bacterial meningitis in ICU patients.
- To identify predictors of adverse clinical outcomes in this patient cohort.
Main Methods:
- Retrospective analysis of patients over 18 years old admitted to two polyvalent ICUs over a 7-year period.
- Collection of clinical, demographic, and outcome data.
- Evaluation of prognostic factors for adverse outcomes.
Main Results:
- 65 patients with acute bacterial meningitis were identified, with a 40% hospital mortality rate.
- Common symptoms included fever (84%), seizures (21.5%), and low Glasgow Coma Scale (GCS) scores (58.4%).
- Older age, higher Acute Physiology and Chronic Health Evaluation II scores, and lower GCS were associated with adverse outcomes. Fever upon admission predicted a better prognosis.
Conclusions:
- Patients with acute bacterial meningitis admitted to the ICU experience substantial morbidity and mortality.
- Low GCS scores and absence of fever are key indicators of a particularly high risk for adverse outcomes.
- These findings highlight critical factors for risk stratification and management in ICU settings.


Related Concept Videos
 01:22
Bacterial Meningitis I: Introduction
 01:26
Bacterial Meningitis II: Pathophysiology
 01:18
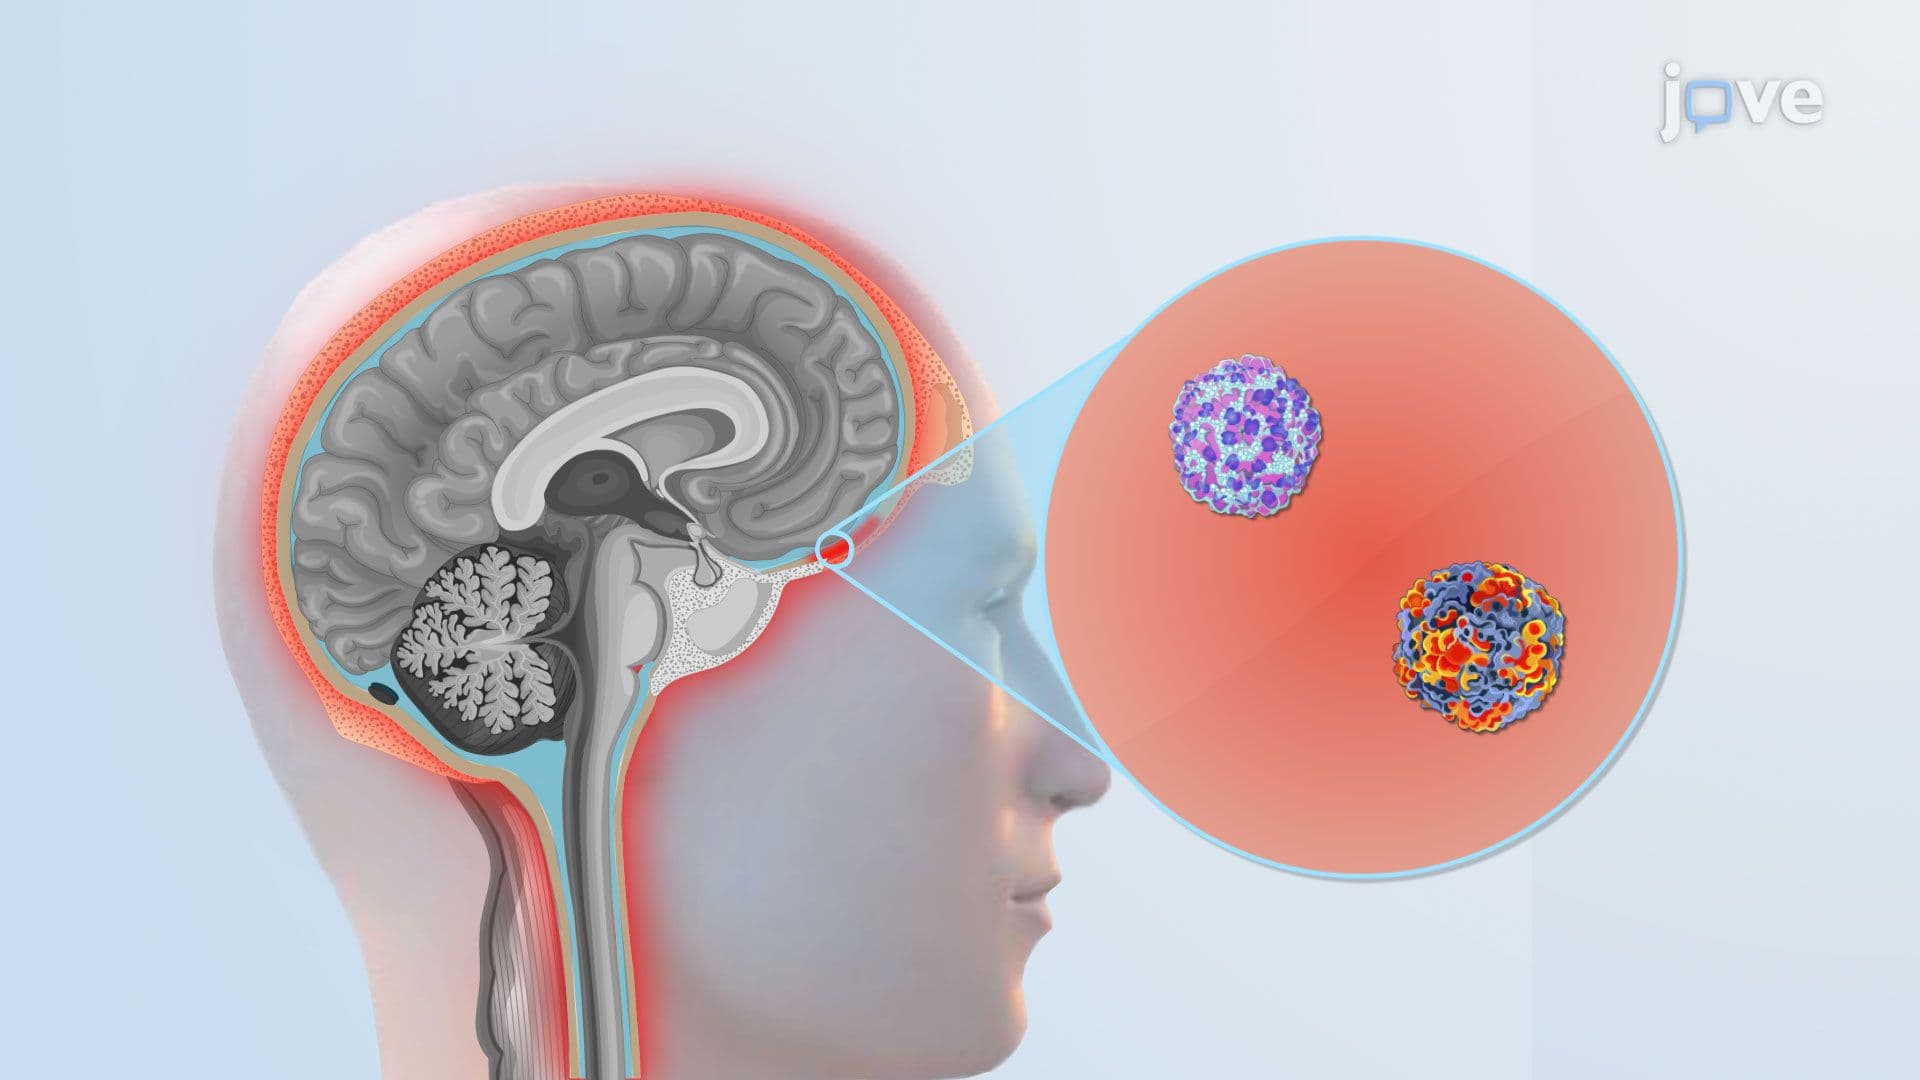
Viral Meningitis
 01:26
Brain Abscess l: Introduction
 01:29
Pneumonia I: Introduction
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...