Related Experiment Video
Updated: May 3, 2026


A Mouse Model of Intestinal Partial Obstruction
Published on: March 5, 2018
Intestinal muscularis propria increases in thickness with corrected gestational age and is focally attenuated in
Sarah Lai1, Weiming Yu2, Laurie Wallace1
1Division of Pediatic Surgery, Alberta Children's Hospital, University of Calgary, Calgary, Alberta, Canada.

Insights
Isolated intestinal perforation (IIP) in infants involves thinner intestinal muscles. This study shows muscle thickness increases with corrected gestational age, suggesting primary repair is suitable for IIP.
Area of Science:
- Neonatal surgery
- Pediatric pathology
- Gastrointestinal development
Background:
- Intestinal perforations are common in premature infants, often misdiagnosed as necrotizing enterocolitis.
- Isolated intestinal perforation (IIP) is linked to muscularis propria absence, but its developmental origins are unclear.
Purpose of the Study:
- To investigate the relationship between corrected gestational age (CGA) and intestinal muscle development in controls and infants with IIP.
- To understand the developmental trajectory of intestinal muscle layers in relation to IIP.
Main Methods:
- Histological examination of intestinal specimens from stillbirths and infants (8-48 weeks' CGA) between 2005-2012.
- Analysis of muscularis mucosa, circular, and longitudinal muscle thickness in 12 IIP patients and controls.
- Statistical comparison using linear regression and ANOVA.
Main Results:
- A linear correlation was observed between CGA and the thickness of circular and longitudinal muscles in control and normal intestinal segments.
- Intestinal segments affected by IIP exhibited significantly thinner circular and longitudinal muscles compared to adjacent normal segments and controls (p<0.05).
Conclusions:
- Intestinal muscularis propria thickness progressively increases with corrected gestational age.
- Focal attenuation of muscle layers in IIP suggests a localized developmental issue, supporting primary surgical repair.
Purpose:
Intestinal perforations are common in premature infants, leading to a diagnostic dilemma between necrotizing enterocolitis and isolated intestinal perforation (IIP). IIP is thought to result from a congenital or acquired absence of the muscularis propria. However, developmental events leading to IIP are not well understood. This study examines the relationship between corrected gestational age (CGA) and intestinal muscle development in controls and patients with IIP.
Methods:
Specimens from stillbirths and infants undergoing intestinal surgery from 8 to 48weeks' CGA were collected from 2005 to 2012. Twelve patients with IIP were identified. Control specimens were collected during 25 fetal autopsies and 39 bowel resections. In each case, three sections of intestine were examined histologically for muscularis mucosa, circular and longitudinal muscle thickness. Comparisons of control and perforated specimens were performed via linear regression and ANOVA.
Results:
Controls and adjacent normal segments in IIP showed a linear relationship between thickness of circular and longitudinal muscles with CGA. Circular and longitudinal muscles were thinner in perforated segments than in adjacent normals and CGA-matched controls (p<0.05).
Conclusion:
Intestinal muscularis propria increases in thickness with CGA. Muscle thickness is focally attenuated in patients with isolated intestinal perforations, while the remaining intestine is normal, suggesting that primary repair is an appropriate treatment.
More Related Videos

Related Concept Videos
 01:20
Histology of the Gastrointestinal (GI) Tract
The mucosa is sometimes called a mucous membrane due to its mucus-secreting features. This membrane is composed of epithelium, which directly interacts with ingested substances, and the lamina propria, a layer...
 01:27
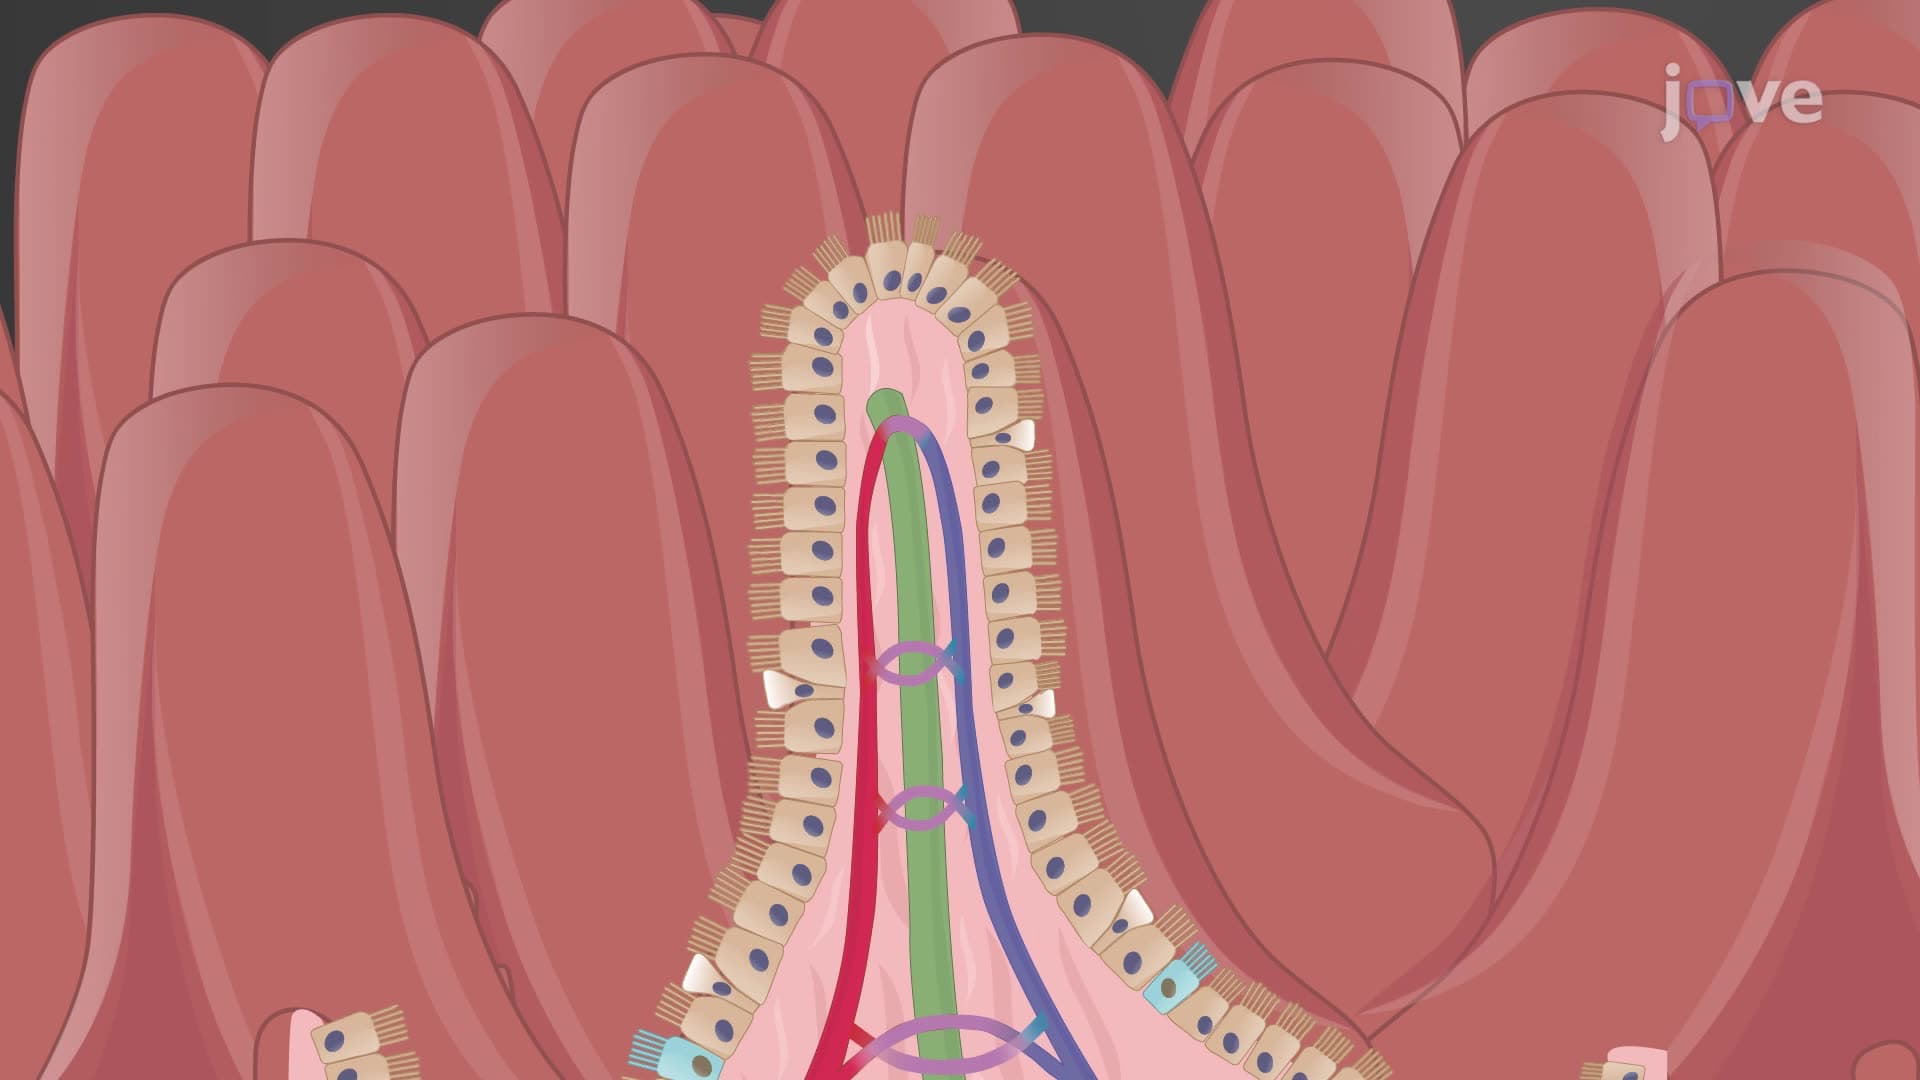
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:26
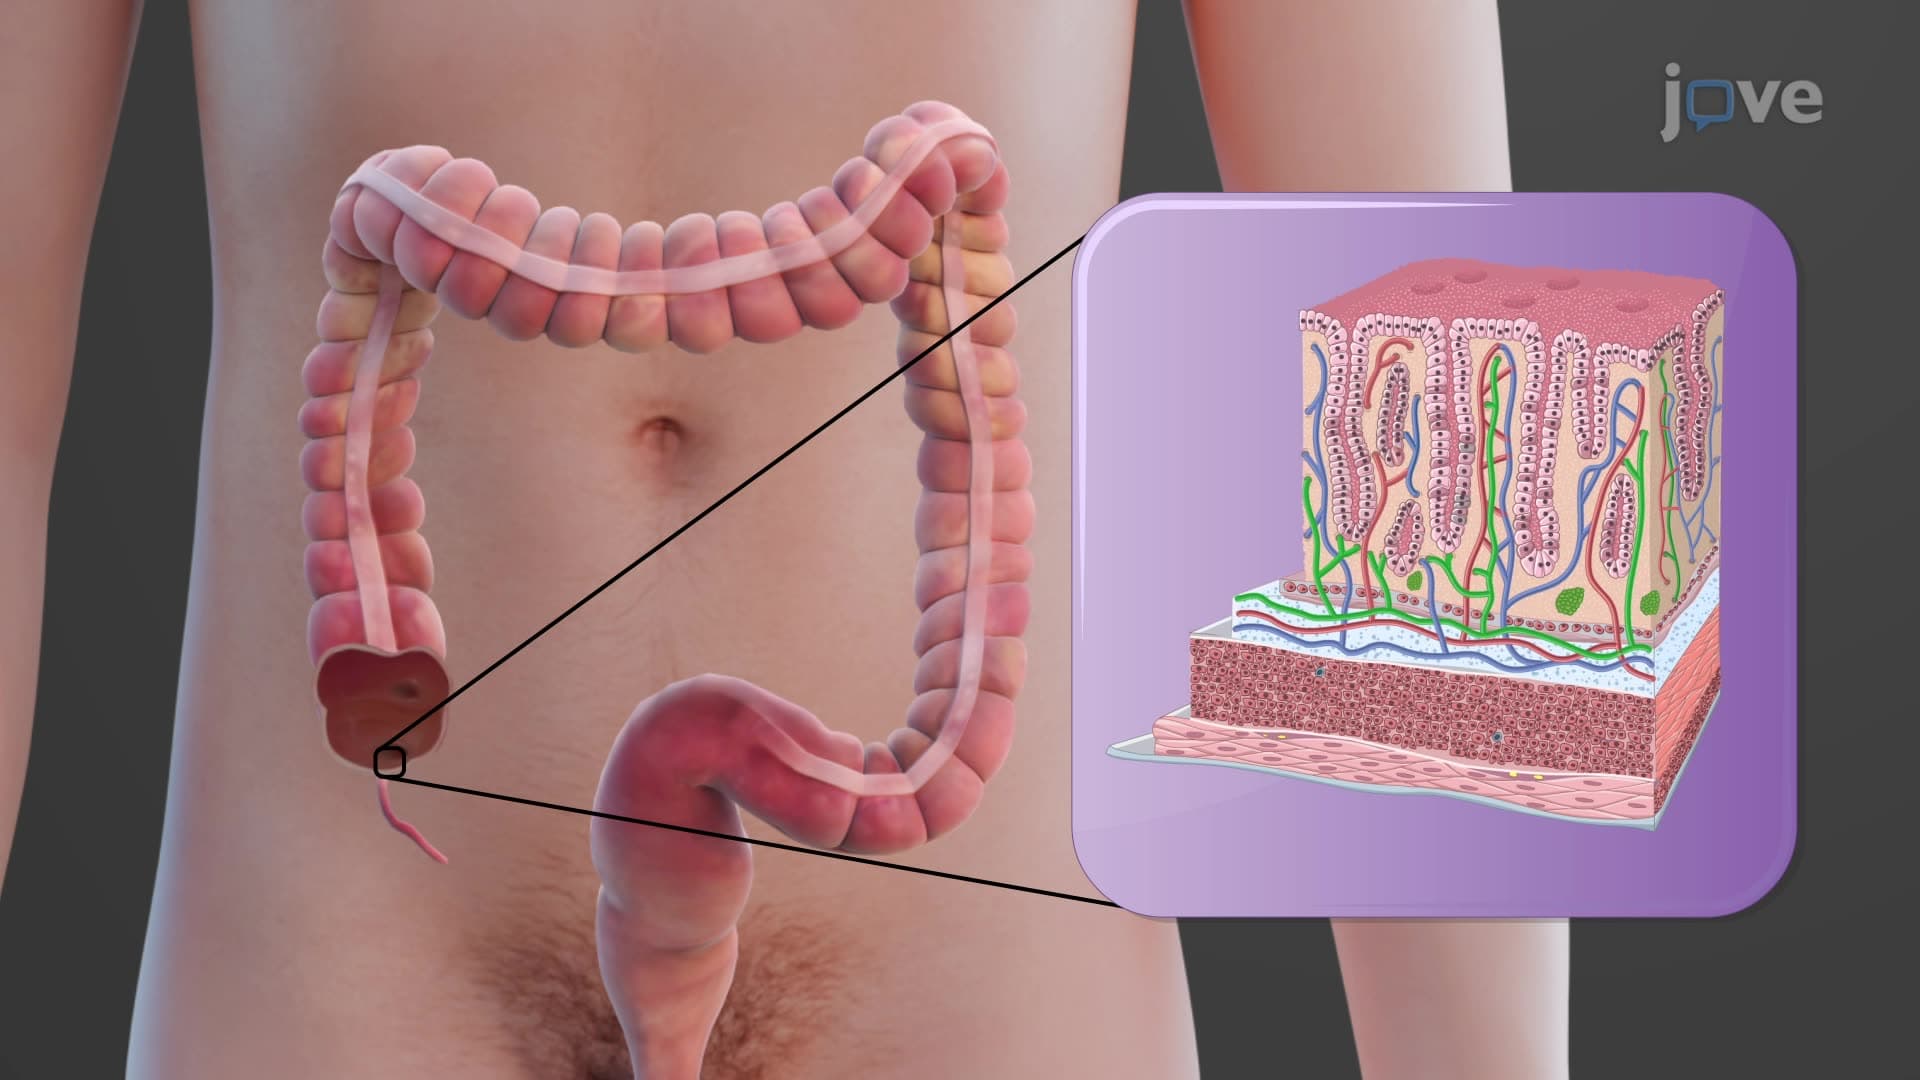
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:07
Intestinal Obstruction II: Pathophysiology
 01:29
Intestinal Obstruction I: Introduction
 01:23
Renewal of Intestinal Stem Cells