Related Experiment Video
Updated: May 3, 2026

Author Spotlight: A Novel Protocol for Intracameral Injections to Enhance Precision in Rodent Ophthalmology
Published on: May 31, 2024
Injectable multiple sclerosis medications: a patient survey of factors associated with injection-site reactions
Thomas M Stewart1, Zung Vu Tran1
1Rocky Mountain MS Center, Westminster, CO, USA (TMS), and the Department of Biostatistics & Informatics, Colorado School of Public Health, University of Colorado Anschutz Medical Campus, Aurora, CO, USA (ZVT).

Although injection-site reactions (ISRs) occur with US Food and Drug Administration-approved injectable disease-modifying therapies (DMTs) for multiple sclerosis, there are currently few reports of real-world data on ISR management strategies or possible correlations between ISRs and patient demographics, disease characteristics, and missed injections. Patient-reported data on the use of DMTs, patient demographic and disease characteristics, missed injections, and ISR reduction strategies were collected via e-mail, a patient registry (www.ms-cam.org), and a Web-based survey. Of the 1380 respondents, 1201 (87%) indicated that they had used injectable DMTs, of whom 377 (31%) had used intramuscular (IM) interferon beta-1a (IFNβ-1a), 172 (14%) had used subcutaneous (SC) IFNβ-1a, 183 (15%) had used SC IFNβ-1b, and 469 (39%) had used glatiramer acetate (GA). The majority of respondents were older (73% were ≥40 years), female (79%), married or living with a partner (72%), white (94%), and nonsmoking (82%). Injection-site reaction incidence, grouped according to severity, varied among DMTs, with IM IFNβ-1a causing significantly (P < .001) fewer mild, moderate, or severe ISRs than the other therapies. Female sex and younger age were significantly (P < .05) associated with more moderate ISRs among users of IM IFNβ-1a, SC IFNβ-1b, and GA. Nonwhites reported severe ISRs more often than whites. For all DMTs injection-site massage and avoidance of sensitive sites were the most frequently used strategies to minimize ISRs. These data may help identify patients with characteristics associated with a higher risk for ISRs, allowing health-care professionals to provide anticipatory guidance to patients at risk for decreased adherence or discontinuation.
Although injection-site reactions (ISRs) occur with US Food and Drug Administration-approved injectable disease-modifying therapies (DMTs) for multiple sclerosis, there are currently few reports of real-world data on ISR management strategies or possible correlations between ISRs and patient demographics, disease characteristics, and missed injections. Patient-reported data on the use of DMTs, patient demographic and disease characteristics, missed injections, and ISR reduction strategies were collected via e-mail, a patient registry (www.ms-cam.org), and a Web-based survey. Of the 1380 respondents, 1201 (87%) indicated that they had used injectable DMTs, of whom 377 (31%) had used intramuscular (IM) interferon beta-1a (IFNβ-1a), 172 (14%) had used subcutaneous (SC) IFNβ-1a, 183 (15%) had used SC IFNβ-1b, and 469 (39%) had used glatiramer acetate (GA). The majority of respondents were older (73% were ≥40 years), female (79%), married or living with a partner (72%), white (94%), and nonsmoking (82%). Injection-site reaction incidence, grouped according to severity, varied among DMTs, with IM IFNβ-1a causing significantly (P < .001) fewer mild, moderate, or severe ISRs than the other therapies. Female sex and younger age were significantly (P < .05) associated with more moderate ISRs among users of IM IFNβ-1a, SC IFNβ-1b, and GA. Nonwhites reported severe ISRs more often than whites. For all DMTs injection-site massage and avoidance of sensitive sites were the most frequently used strategies to minimize ISRs. These data may help identify patients with characteristics associated with a higher risk for ISRs, allowing health-care professionals to provide anticipatory guidance to patients at risk for decreased adherence or discontinuation.
More Related Videos
 04:41
Lumbar Intrathecal Injection of SOD1-ASOs for Precise CNS Targeting and Predictive Efficacy in Human SOD1-G93A ALS Mice
Published on: February 24, 2026
 10:57
Intramuscular Injections Along the Motor End Plates: A Minimally Invasive Approach to Shuttle Tracers Directly into Motor Neurons
Published on: July 13, 2015
Related Concept Videos
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections
 01:28
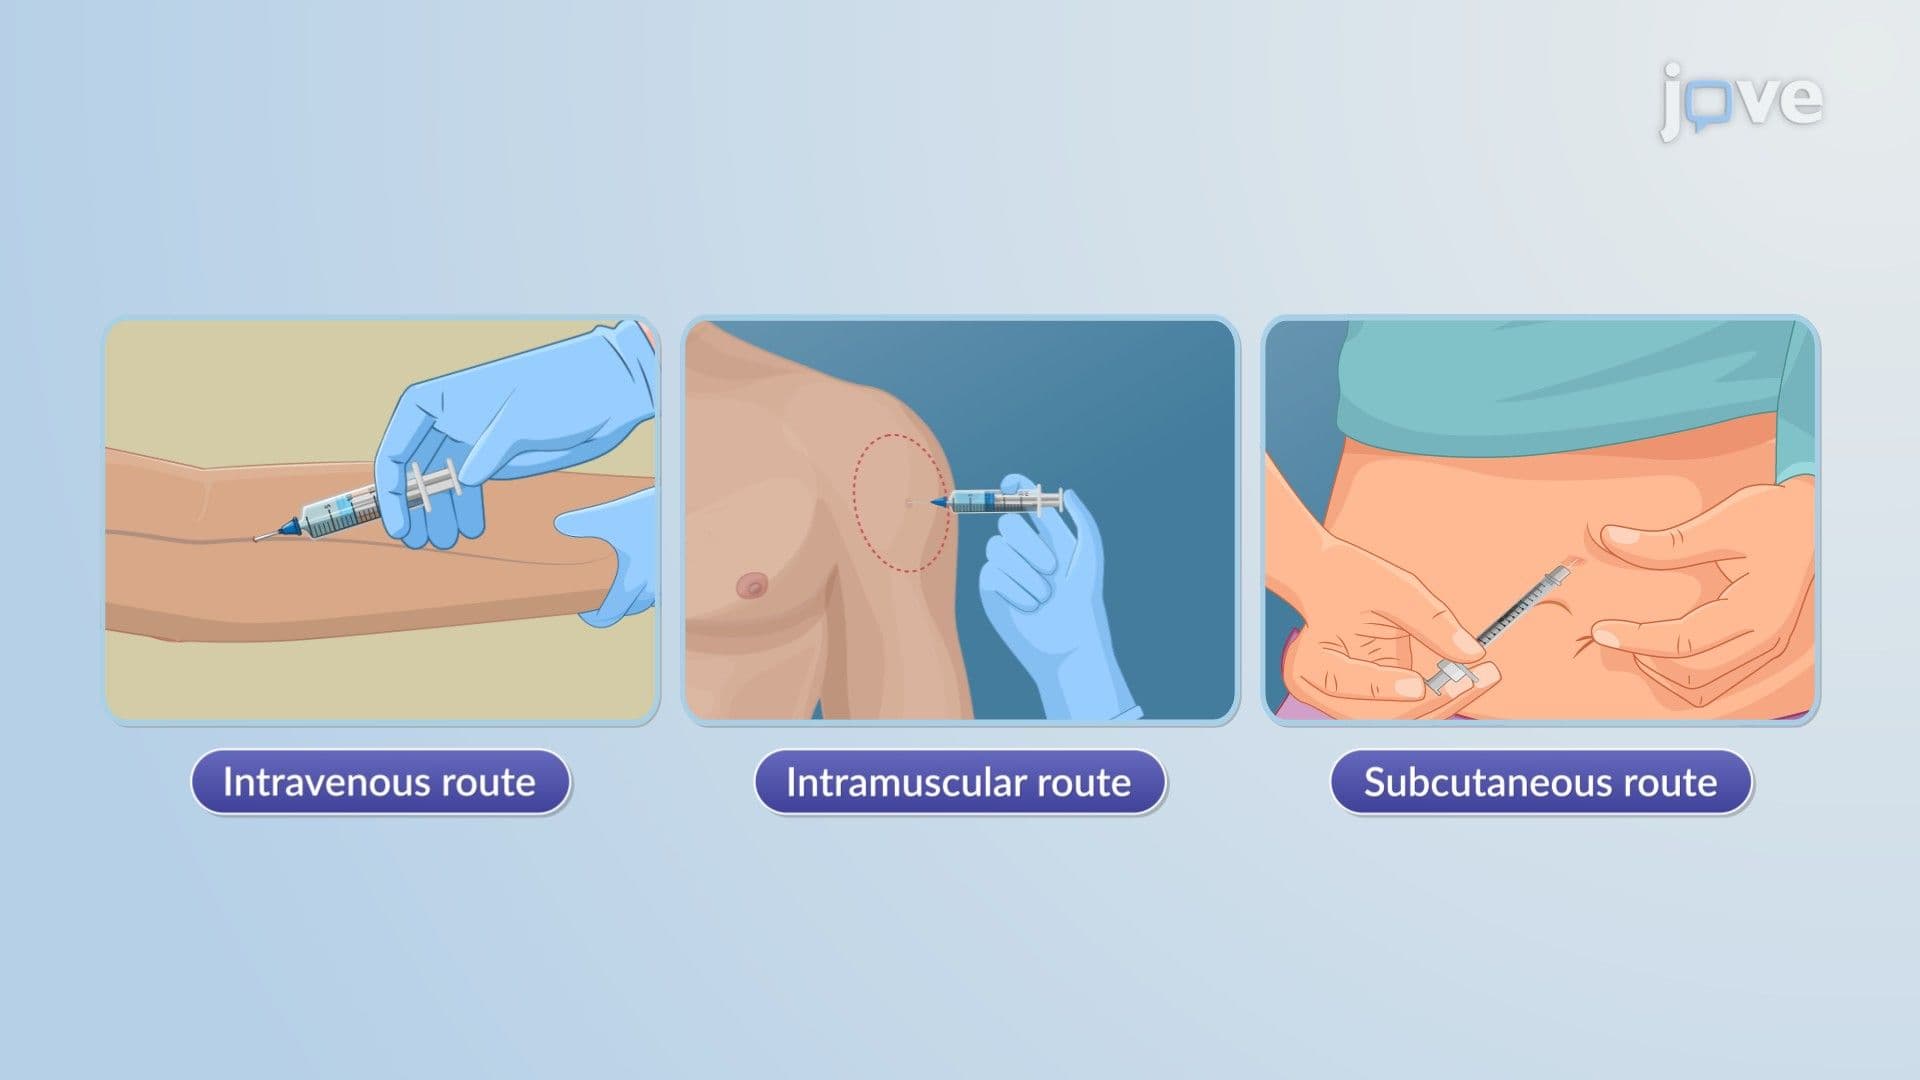
Parenteral Drug Delivery Systems: Injectables, Implants, and Infusion Devices
 01:19
Hypersensitivity Reactions: Immune-Complex Reactions
 01:27
Allergic Drug Reactions
 01:19
Multiple Sclerosis l: Introduction
 01:25
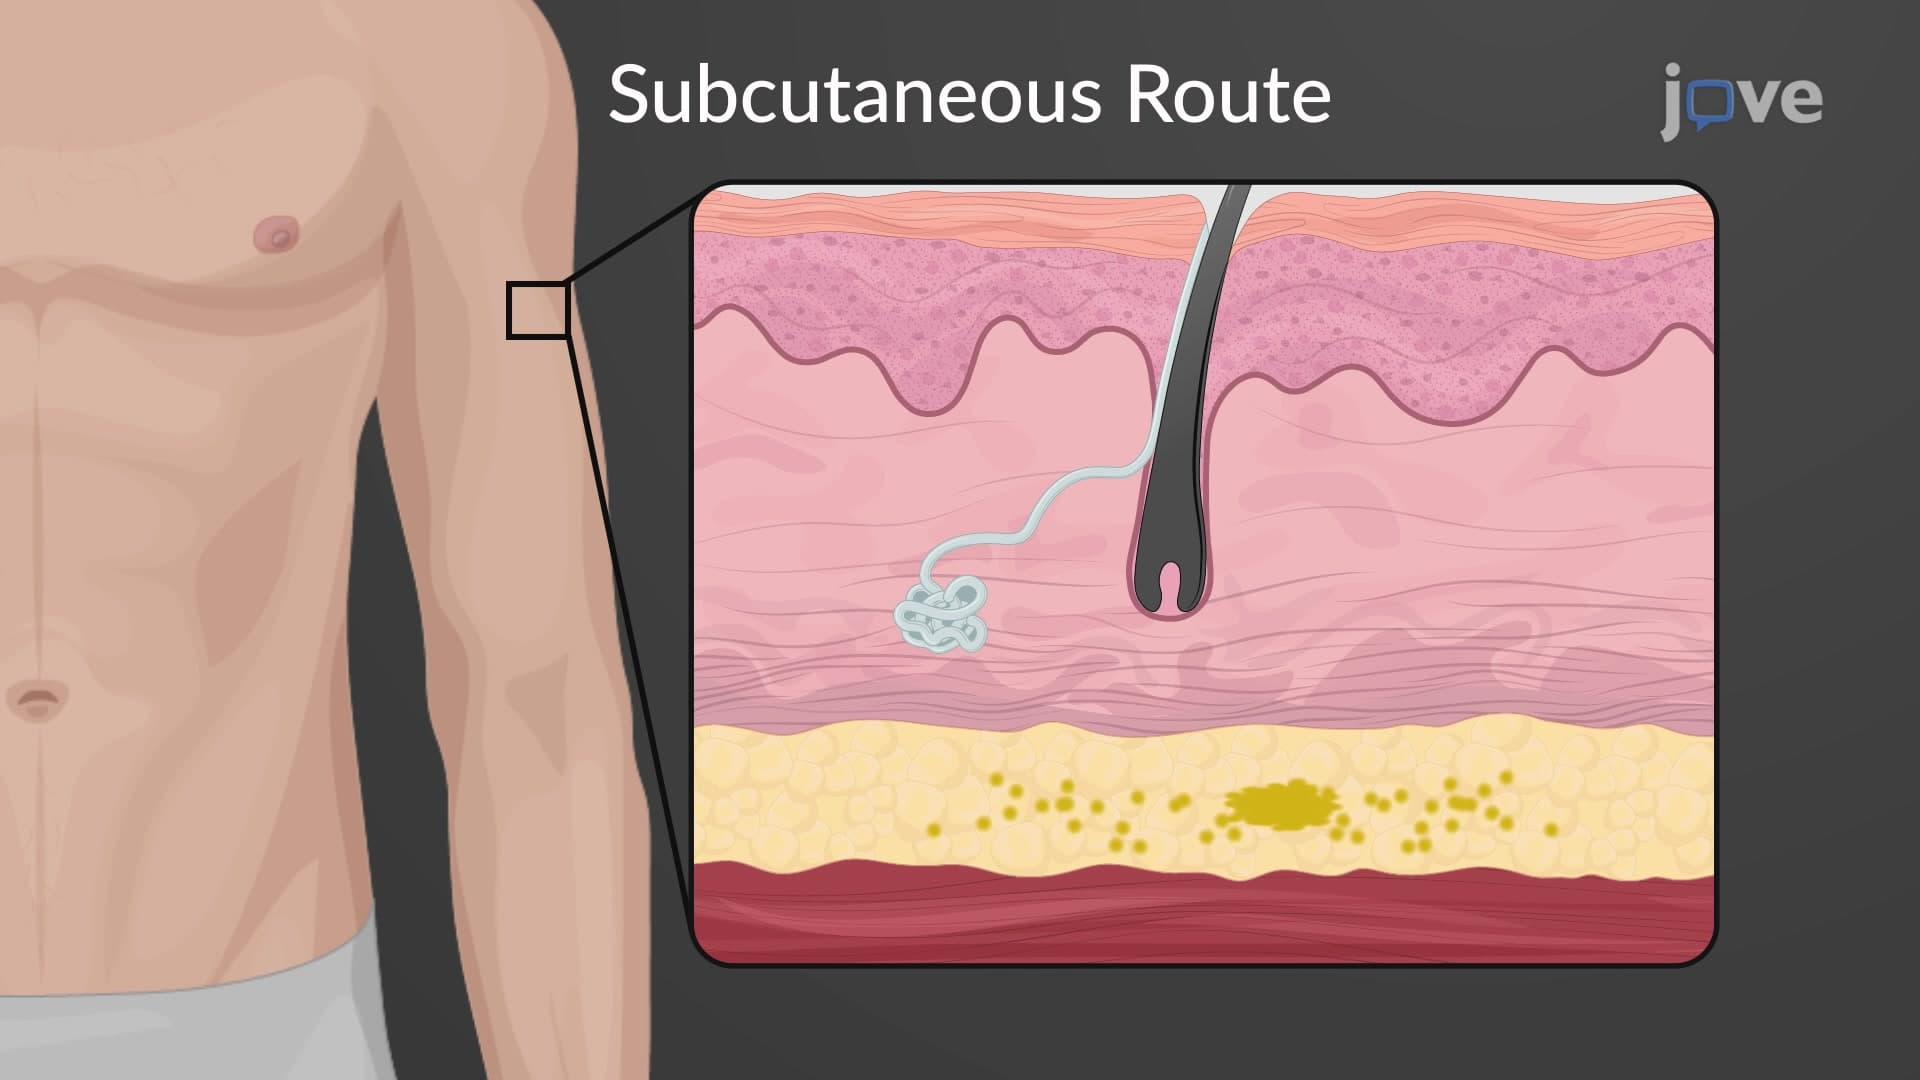
Routes of Drug Administration: Parenteral
The intravenous route (IV) of drug administration can be further categorized into two types. The bolus injection administers the entire dose rapidly, while an intravenous infusion slowly delivers smaller doses steadily.
The IV route is often...