Related Experiment Video
Updated: May 3, 2026
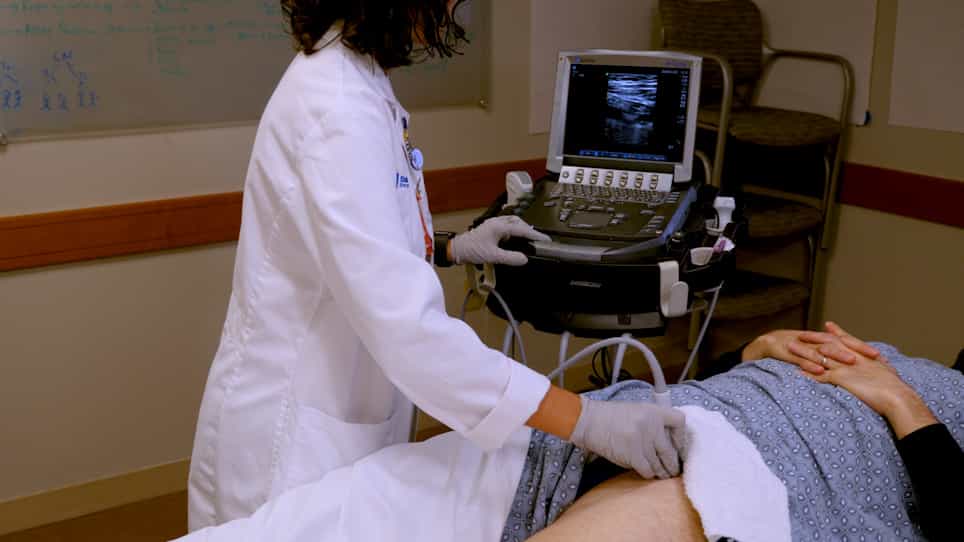
Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
Incremental health care resource utilization and economic burden of venous thromboembolism recurrence from a U.S.
J Lin1, M Lingohr-Smith, W J Kwong
1Novosys Health, 7 Crestmont Ct., Flemington, NJ 08822, USA. jay.lin@novosyshealth.com.

Insights
Venous thromboembolism (VTE) recurrence leads to significant healthcare costs, with 11-15% of patients experiencing a repeat event within a year. High costs are concentrated in the 30 days post-event, highlighting the need for improved VTE prevention strategies.
Area of Science:
- Cardiovascular Medicine
- Health Economics
- Epidemiology
Background:
- Venous thromboembolism (VTE) is a major cause of cardiovascular death and incurs substantial healthcare costs.
- While the cost of a single VTE event is known, data on the economic burden of VTE recurrence are limited.
Purpose of the Study:
- To determine the rate and predictors of VTE recurrence within one year in the US.
- To evaluate the incremental healthcare resource utilization and costs associated with VTE recurrence.
Main Methods:
- Analysis of US commercial and Medicare databases (2008-2010) for patients aged 18+ with VTE.
- Inclusion criteria: 12 months pre/post-index VTE coverage, anticoagulant initiation within 30 days.
- Recurrence defined as VTE hospitalization/ER visit; predictors assessed using proportional hazards models; costs analyzed using generalized linear models.
Main Results:
- VTE recurrence within 12 months was 15.4% in commercially insured and 11.4% in Medicare populations.
- Higher comorbidity (Charlson Comorbidity Index) predicted recurrence in both groups.
- Recurrent VTE patients incurred significantly higher healthcare costs (all-cause and VTE-related), driven by inpatient care within 30 days post-index event.
Conclusions:
- VTE recurrence is associated with substantial healthcare utilization, particularly inpatient care within 30 days of the initial event.
- A significant economic burden of recurrent VTE is incurred shortly after the initial event.
- High recurrence rates necessitate improved anticoagulation and preventative strategies to reduce VTE's healthcare and economic impact.
Background:
The third leading cause of cardiovascular-associated death, venous thromboembolism (VTE), represents a significant health care and economic burden. Although the burden of a one-time VTE event has been assessed, there are limited data regarding the burden of VTE recurrence.
Objective:
To assess the rate and predictors of VTE recurrence within 1 year in the United States and evaluate the incremental health care resource utilization and costs associated with such VTE recurrences.
Methods:
Patients (≥ 18 years) diagnosed with deep vein thrombosis and/or pulmonary embolism between January 1, 2008, and December 31, 2010, were identified from the Truven Health Analytics MarketScan Commercial and Medicare databases. The earliest VTE diagnosis was defined as the index VTE event. Patients were required to have 12 months of continuous insurance coverage before (baseline period) and after (follow-up period) the index event. Patients were further required to have initiated anticoagulant usage within 30 days of the index VTE event and have at least 30 days of treatment. The incidence of recurrent VTE, defined as a hospitalization or emergency room (ER) visit with a VTE diagnosis in the follow-up period, was determined for the commercially insured and Medicare populations separately. A proportional hazards model was used to assess the predictors of time to VTE recurrences. All cause and VTE-related health care resource utilization including hospitalizations, length of stay, outpatient medical service claims, and outpatient pharmacy claims were assessed along with the associated costs incurred during the 30-day and 12-month post-index event periods. Commercially insured and Medicare patients with and without recurrent VTE were evaluated and compared separately. Generalized linear models were used to further assess the incremental cost burden of recurrent VTE.
Results:
Among the commercially insured population, 29,275 patients were diagnosed with VTE and received anticoagulant therapy. A recurrence of VTE associated with a hospitalization or ER visit occurred within 12 months of the index VTE in 15.4% of patients with a mean time to recurrence of 74.1 days. Among the Medicare insured population (n = 14,509), 11.4% of patients experienced another VTE with a mean time to recurrence of 115.6 days. A consistent predictor of VTE recurrence across both populations was greater comorbidity as indicated by Charlson Comorbidity Index scores. Among commercially insured VTE patients, total payments for health care resource utilization for all causes, including inpatient, outpatient medical services, and outpatient pharmacy use were higher for patients with a recurrent VTE relative to those without a recurrent VTE ($82,110 [$106,918] vs. $36,918 [$54,852], P less than 0.001). The primary driver for the higher health care payments was greater use of inpatient care. Total payments for VTE-related resource use was also greater for patients with a VTE recurrence ($38,591 [$51,479] vs. $15,123 [$22,186], P less than 0.001) with the majority (62.9%) attributed to care that took place within 30 days of the index VTE. After adjustment for key patient characteristics, VTE recurrence was associated with 2.2-fold and 3.0-fold higher post-index health care payments for all causes and for VTE-related claims, respectively. Similar results were observed for the Medicare population.
Conclusions:
VTE recurrence associated with a hospitalization or ER visit is associated with substantial health care resource utilization, which is primarily inpatient care undergone within the first 30 days following an initial VTE event. Thus, a sizeable portion of the economic burden of recurrent VTE is also incurred during this short period of time following an initial VTE event. Given that rates of VTE recurrence were high among patients identified as having received anticoagulant treatment, strategies to improve anticoagulation therapy among VTE patients in addition to other preventative measures are needed to lessen the health care and economic burdens of VTE.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:27
Pulmonary Embolism III: Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system...