Related Experiment Video
Updated: May 3, 2026

Author Spotlight: Using Point-of-Care Ultrasound for Comprehensive Evaluation of the Abdominal Aorta
Published on: September 8, 2023
Perforated appendicitis: an underappreciated mimic of intussusception on ultrasound
Beverley Newman1, Matthew Schmitz, Rakhee Gawande
1Department of Radiology, Stanford University, Lucile Packard Children's Hospital, 725 Welch Road, MC 5913, Stanford, CA, 94305, USA, bevn@stanford.edu.

Insights
Ruptured appendicitis can mimic intussusception on ultrasound, causing delays. Careful review of imaging and clinical signs can help differentiate these conditions, improving diagnosis and treatment for pediatric patients.
Area of Science:
- Pediatric Radiology
- Diagnostic Imaging
- Gastrointestinal Diseases
Background:
- Ruptured appendicitis in children can present with ultrasound (US) findings that closely resemble intussusception.
- This mimicry can lead to diagnostic delays, unnecessary imaging, and suboptimal treatment.
Purpose of the Study:
- To identify key clinical and imaging features that distinguish ruptured appendicitis from intussusception on ultrasound.
- To improve diagnostic accuracy and reduce delays in pediatric cases.
Main Methods:
- Retrospective review of initial US images from six pediatric patients with surgically confirmed perforated appendicitis.
- Independent and consensus review by three pediatric radiologists.
- Correlation with subsequent imaging (US, fluoroscopy, CT) and clinical data.
Main Results:
- Initial US studies showed a "target sign" (multiple rings), often misinterpreted as intussusception.
- Central echogenicity was misidentified as mesenteric fat, but represented appendicolith or debris.
- Perilesional hyperechogenicity represented inflamed fat surrounding the appendix.
- CT scans confirmed a double-ring appearance correlating with US findings.
- All six children were ultimately diagnosed with perforated appendicitis via surgery.
Conclusions:
- Contained perforated appendicitis can present with US findings indistinguishable from intussusception.
- Clinical correlation and multiplanar US evaluation are crucial for suspecting perforated appendicitis.
- CT can be used for confirmation when sonographic suspicion arises.
Background:
We encountered multiple cases in which the US appearance of ruptured appendicitis mimicked intussusception, resulting in diagnostic and therapeutic delay and multiple additional imaging studies.
Objective:
To explore the clinical and imaging discriminatory features between the conditions.
Materials And Methods:
Initial US images in six children (age 16 months to 8 years; 4 boys, 2 girls) were reviewed independently and by consensus by three pediatric radiologists. These findings were compared and correlated with the original reports and subsequent US, fluoroscopic, and CT images and reports.
Results:
All initial US studies demonstrated a multiple-ring-like appearance (target sign, most apparent on transverse views) with diagnostic consensus supportive of intussusception. In three cases, US findings were somewhat discrepant with clinical concerns. Subsequently, four of the six children had contrast enemas; two were thought to have partial or complete intussusception reduction. Three had a repeat US examination, with recognition of the correct diagnosis. None of the US examinations demonstrated definite intralesional lymph nodes or mesenteric fat, but central echogenicity caused by debris/appendicolith was misinterpreted as fat. All showed perilesional hyperechogenicity that, in retrospect, represented inflamed fat "walling off" of the perforated appendix. There were four CTs, all of which demonstrated a double-ring appearance that correlated with the US target appearance, with inner and outer rings representing the dilated appendix and walled-off appendiceal rupture, respectively. All six children had surgical confirmation of perforated appendicitis.
Conclusion:
Contained perforated appendicitis can produce US findings closely mimicking intussusception. Clinical correlation and careful multiplanar evaluation should allow for sonographic suspicion of perforated appendicitis, which can be confirmed on CT if necessary.
More Related Videos
 05:50
Author Spotlight: Point-of-Care Ultrasound for Gastric Content Assessment and Risk Stratification in Perioperative Care
Published on: September 22, 2023
 07:20
Intraoperative Detection of Subtle Endometriosis: A Novel Paradigm for Detection and Treatment of Pelvic Pain Associated with the Loss of Peritoneal Integrity
Published on: December 21, 2012
Related Concept Videos
 01:22
Appendicitis-I: Introduction
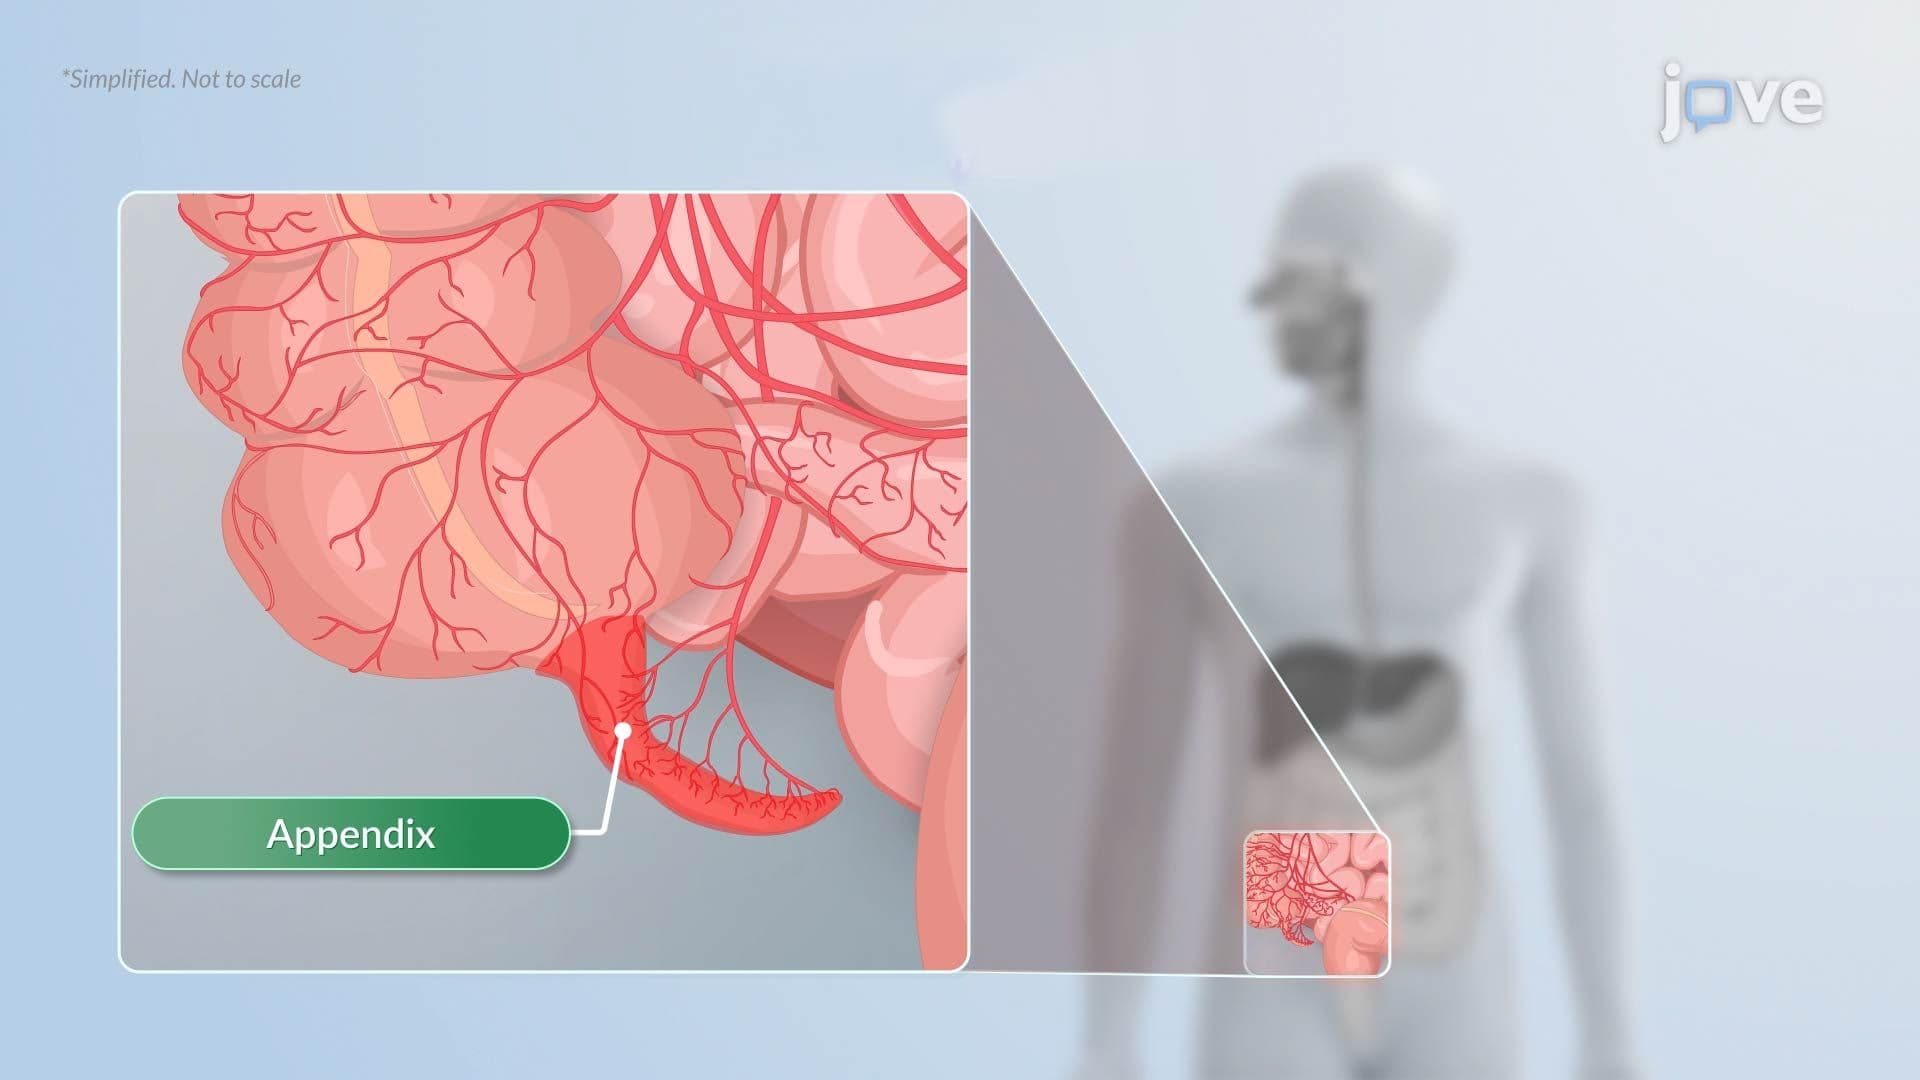
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:19
Appendicitis
 01:29
Intestinal Obstruction I: Introduction
 01:27
Diverticular Disease of the Colon
 01:07
Intestinal Obstruction II: Pathophysiology
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...