Related Experiment Video
Updated: May 3, 2026
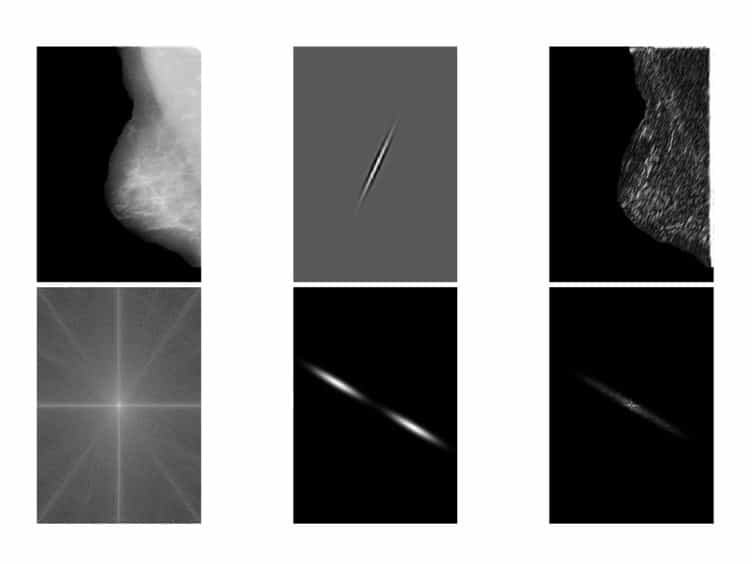

Detection of Architectural Distortion in Prior Mammograms via Analysis of Oriented Patterns
Published on: August 30, 2013
Breast cancer detected with screening US: reasons for nondetection at mammography
Min Sun Bae1, Woo Kyung Moon, Jung Min Chang
1From the Department of Radiology, Seoul National University College of Medicine, 28 Yongon-dong, Chongno-gu, Seoul 110-744, Korea (M.S.B., W.K.M., J.M.C., H.R.K., W.H.K., N.C., B.L.Y., S.H.L., E.B.R., M.S.); Department of Radiology, Seoul Metropolitan Government Seoul National University, Boramae Medical Center, Seoul, Korea (A.Y.); and Department of Radiology, Konkuk University Medical Center, Seoul, Korea (M.Y.K.).

Purpose:
To retrospectively review the mammograms of women with breast cancers detected at screening ultrasonography (US) to determine the reasons for nondetection at mammography.
Materials And Methods:
This study received institutional review board approval, and informed consent was waived. Between 2003 and 2011, a retrospective database review revealed 335 US-depicted cancers in 329 women (median age, 47 years; age range, 29-69 years) with Breast Imaging Reporting and Data System breast density type 2-4. Five blinded radiologists independently reviewed the mammograms to determine whether the findings on negative mammograms should be recalled. Three unblinded radiologists re-reviewed the mammograms to determine the reasons for nondetection by using the reference location of the cancer on mammograms obtained after US-guided wire localization or breast magnetic resonance imaging. The number of cancers recalled by the blinded radiologists were compared with the reasons for nondetection determined by the unblinded radiologists.
Results:
Of the 335 US-depicted cancers, 63 (19%) were recalled by three or more of the five blinded radiologists, and 272 (81%) showed no mammographic findings that required immediate action. In the unblinded repeat review, 263 (78%) cancers were obscured by overlapping dense breast tissue, and nine (3%) were not included at mammography owing to difficult anatomic location or poor positioning. Sixty-three (19%) cancers were considered interpretive errors. Of these, 52 (82%) were seen as subtle findings (46 asymmetries, six calcifications) and 11 (18%) were evident (six focal asymmetries, one distortion, four calcifications).
Conclusion:
Most breast cancers (81%) detected at screening US were not seen at mammography, even in retrospect. In addition, 19% had subtle or evident findings missed at mammography.

