Related Experiment Video
Updated: Oct 11, 2026

Demonstration of the Sequence Alignment to Predict Across Species Susceptibility Tool for Rapid Assessment of Protein Conservation
Published on: February 10, 2023
[Pharmacology and dosage of thyrostatic drugs]
A Passath1, G Leb, H Warnkross
1Medizinischen Universitätsklinik Graz.

Abstract:
The iodine organification in thyroid gland was inhibited by application of Thyrostatic (Methimazole, Carbimazole) and consequently, thyroid hormone production and excretion were diminished. Carbimazole is converted to Methimazole in vivo and in vitro. Equivalent doses of Carbimazole and Methimazole are 0.6 to 1.0. Methimazole penetrates through the placenta, therefore established therapy with Methimazole (or Carbimazole) and thyroid hormone are contradicted in states of gravidity. In hyperthyroidism, preferred therapy strategy is accepted as Methimazole and/or Carbimazole only and in low doses, respectively (40-60 mg Methimazole as first step, consequently to doses down to 5-10 mg daily); accompaning rates of hematopoetic damage are dose responded.
More Related Videos


Related Concept Videos
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:24
Antiasthma Drugs: Methylxanthines
Theophylline is thought to inhibit phosphodiesterase enzymes, increasing intracellular levels of cyclic adenosine monophosphate (cAMP) and cyclic guanosine monophosphate (cGMP). This rise in cAMP and cGMP concentrations stimulates cardiac function,...
 01:24
Drug Toxicity: Dose-Dependent Reactions
 01:25
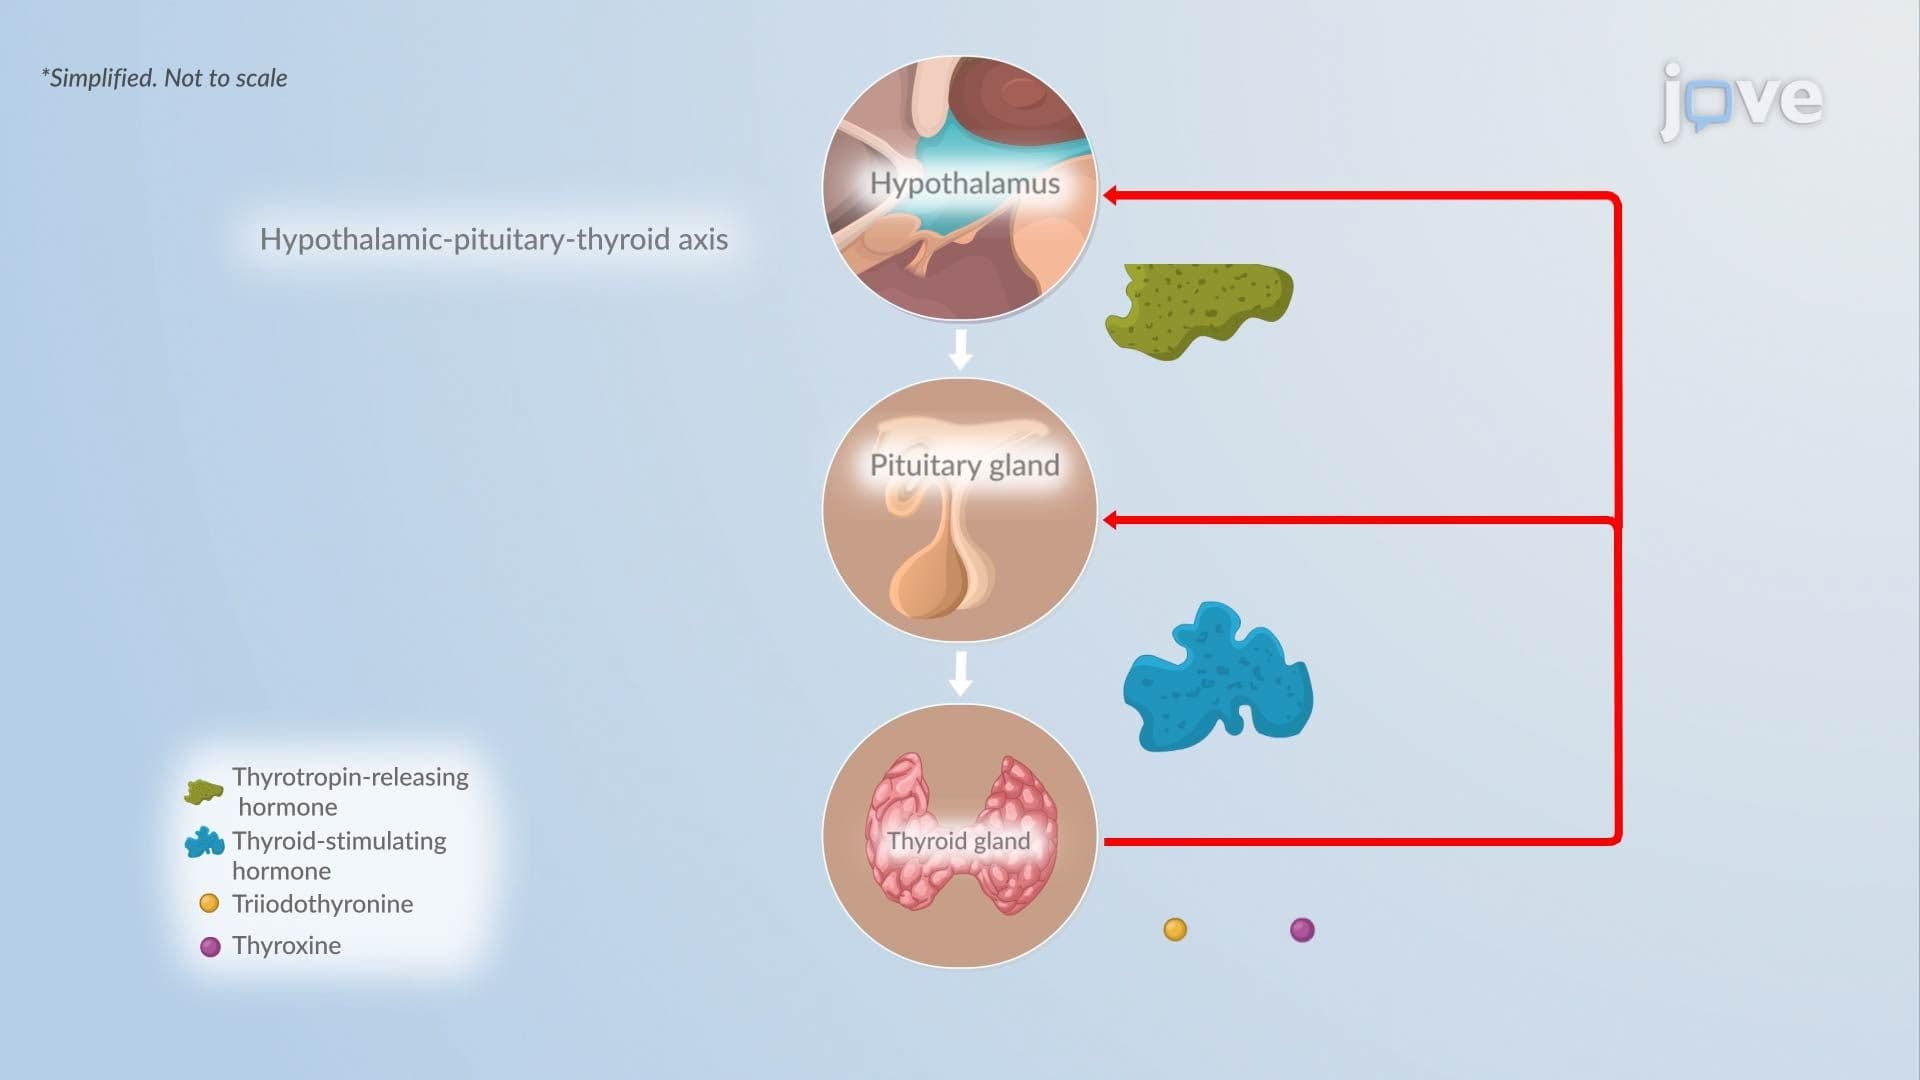
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology