Birth volume and the quality of obstetric care in rural hospitals
Katy B Kozhimannil1, Peiyin Hung, Shailendra Prasad
1Division of Health Policy and Management, University of Minnesota School of Public Health, Minneapolis, Minnesota; University of Minnesota Rural Health Research Center, Minneapolis, Minnesota.

Background:
Childbirth is the most common reason for hospitalization in the United States. Assessing obstetric care quality is critically important for patients, clinicians, and hospitals in rural areas.
Methods:
The study used hospital discharge data from the Statewide Inpatient Databases, Healthcare Cost and Utilization Project, Agency for Healthcare Research and Quality, for 9 states (Colorado, Iowa, Kentucky, New York, North Carolina, Oregon, Vermont, Washington, and Wisconsin) to identify all births in rural hospitals with 10 or more births/year in 2002 (N = 94,356) and 2010 (N = 103,880). Multivariate logistic regression was used to assess the relationship between hospital annual birth volume, measured as low (10-110), medium (111-240), medium-high (241-460) or high (>460), and 3 measures of obstetric care quality (low-risk cesarean rates for term, vertex, and singleton pregnancies with no prior cesarean; nonindicated cesarean; and nonindicated induction) and 2 patient safety measures (episiotomy and perineal laceration).
Results:
The odds of low-risk and nonindicated cesarean were lower in medium-high and high-volume rural hospitals compared with low-volume hospitals after controlling for maternal demographic and clinical factors. In low-volume hospitals, odds of labor induction without medical indication were higher than in medium-volume hospitals, but not significantly different from medium-high or high-volume hospitals. Odds of episiotomy were greater in medium-high or high-volume hospitals than in low-volume hospitals. The likelihood of perineal laceration did not differ significantly by birth volume.
Conclusions:
Obstetric quality and safety outcomes vary significantly across rural hospitals by birth volume. Better performance is not consistently associated with either lower or higher volume facilities.
Related Concept Videos
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:26
Methods Of Healthcare Delivery System
Managed Care System:
The managed care system is designed to control the cost while maintaining the quality of care. The patient's care from admission to discharge is planned by the primary care provider or the case manager, also known as the gatekeeper. In a managed care system, the number of care providers is...
 01:29
Issues And Trends In Healthcare Delivery System
Cost Containment
Payment for healthcare services has historically promoted adoption of costly and often unnecessary or inefficient...
 01:26
Blood Studies I: ABG and VBG
Arterial Blood Gas (ABG)
Arterial Blood Gas (ABG) studies are crucial for assessing the lungs' ability to supply oxygen and remove carbon dioxide, reflecting the patient's ventilation status. They also help understand the kidneys' capacity to...
 01:30
Primary Healthcare Services
In 1978, international leaders convened in Alma-Ata, Kazakhstan, for what would be a pivotal event in global health. The Alma-Ata Declaration was the first to call...
 01:15
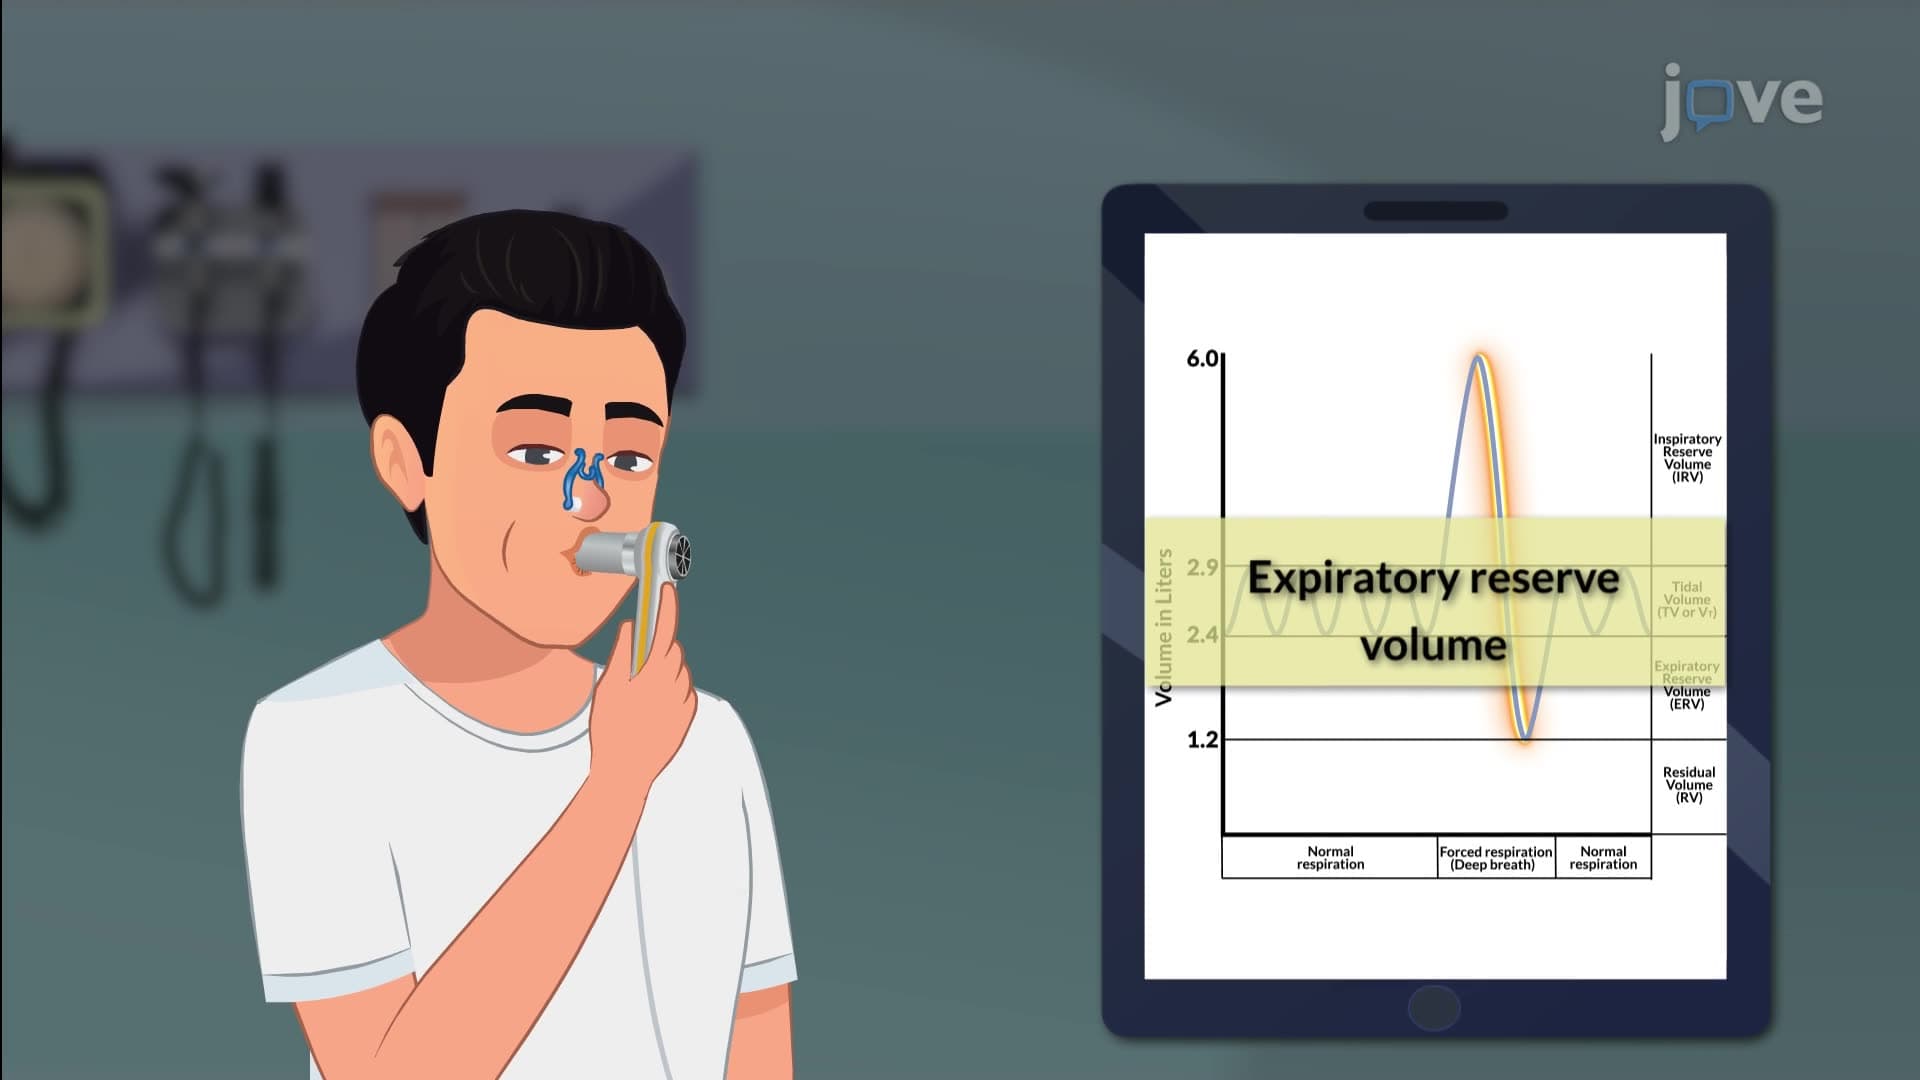
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...