Related Experiment Video For craniofacial pain
Updated: May 3, 2026
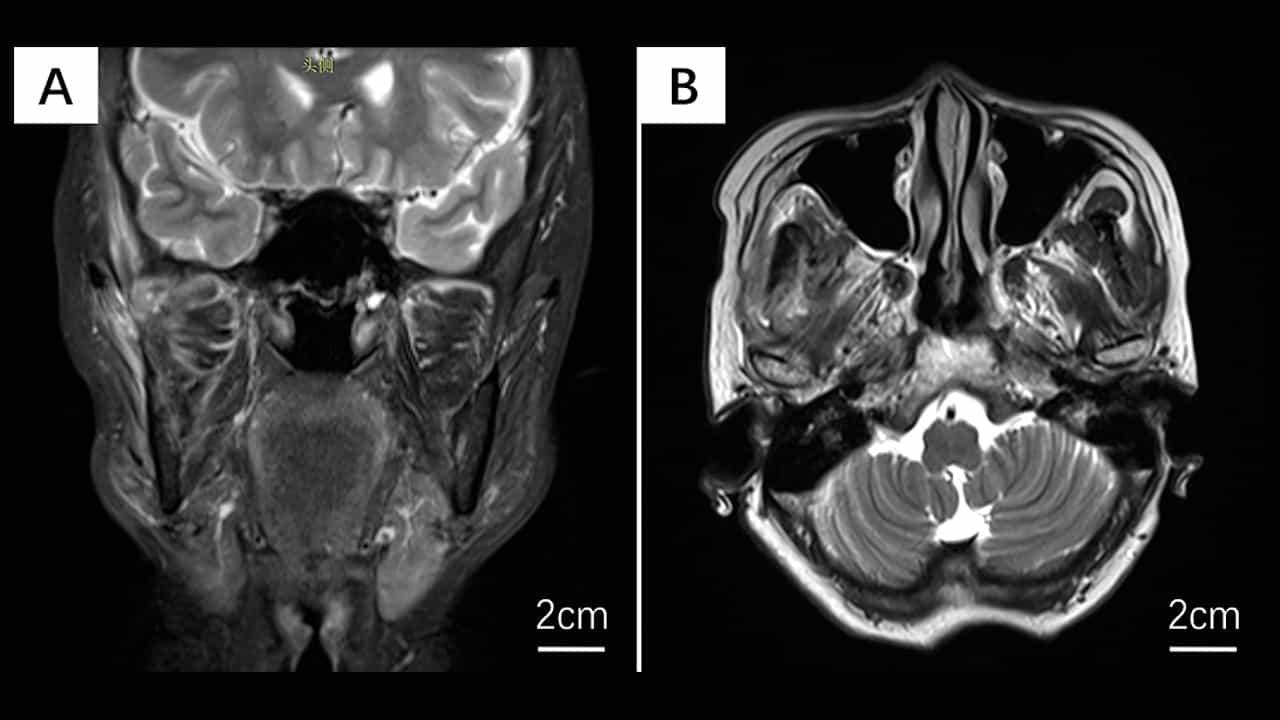

Lateral Molar Approach-Driven Transoral Endoscopic Procedure for Benign Infratemporal Fossa Tumor Resection
Published on: August 15, 2025
Craniofacial pain secondary to occult head and neck tumors
Kathryn M Van Abel1, Sid Starkman, Ashley G O'Reilly
1Department of Otolaryngology-Head and Neck Surgery, Mayo Clinic School of Medicine, Rochester, Minnesota, USA.

Objectives:
To review the natural history of occult head and neck malignancy presenting with facial pain and evaluate the risk factors, diagnostic workup, and management of facial pain in the setting of occult malignancy.
Study Design:
Retrospective chart review.
Setting:
Tertiary care center.
Subjects And Methods:
All patients presenting from 1980 to 2010 with facial pain and a delayed diagnosis of a head and neck cancer were reviewed.
Results:
Thirty-eight patients were included. Onset of pain was rapid or sudden in 94.7%, intermittent in 84.2%, and sharp in 86.8%. Facial nerve weakness was present in 15.8%. Five patients had a history of locoregional skin cancer, and 14% had a history of malignancy. Average delay to diagnosis was 18.4 months. On average, the suspicious lesion was identified on the second scan (mean, 2.1; range, 1-4 scans). Diagnosis was suggested by magnetic resonance imaging in 54.8% and computed tomography in 38.7% of patients. The most common pathology was squamous cell carcinoma (39.5%), and the predominant location was the parotid gland (28.9%). Surgical resection (66%) was the most common intervention. In patients who received treatment and had clinical follow-up available for review, 97.0% (32/33) reported symptomatic improvement.
Conclusions:
In our series, sudden-onset, intermittent, sharp facial pain without resolution or improvement was associated with occult malignancy and should be considered in the differential diagnosis for facial pain. Based on the high incidence of early negative imaging, consideration should be given to repeat imaging when there is concern for malignancy. Therapeutic interventions often result in improvement of facial pain.

Related Concept Videos
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...