Related Experiment Video
Updated: May 3, 2026
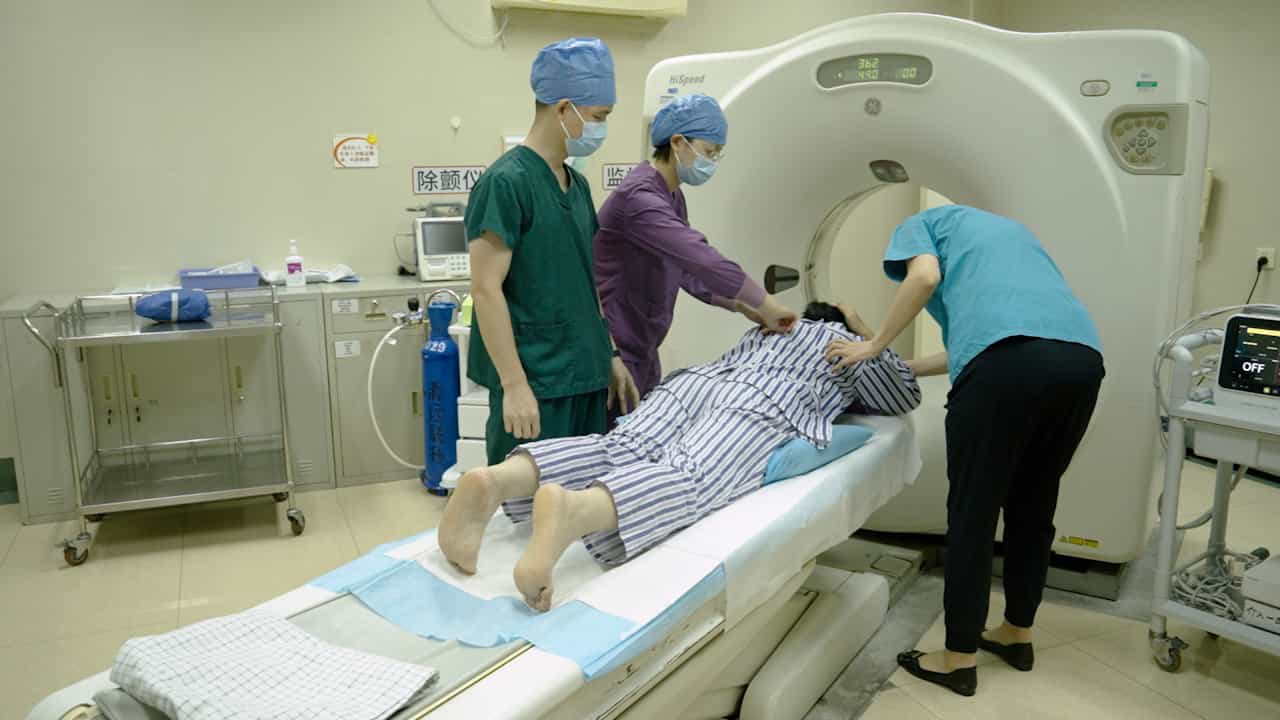

Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Specialty use among patients with treated hypertension in a patient-centered medical home
David T Liss1, Paul A Fishman, Carolyn M Rutter
1Division of General Internal Medicine and Geriatrics, Northwestern University, Feinberg School of Medicine, 750 N. Lake Shore Drive, 10th floor, Chicago, IL, 60611, USA, david.liss@northwestern.edu.

Background:
Little is known about how delivery of primary care in the patient-centered medical home (PCMH) influences outpatient specialty care use.
Objective:
To describe changes in outpatient specialty use among patients with treated hypertension during and after PCMH practice transformation.
Design:
One-group, 48-month interrupted time series across baseline, PCMH implementation and post-implementation periods.
Patients:
Adults aged 18-85 years with treated hypertension.
Intervention:
System-wide PCMH redesign implemented across 26 clinics in an integrated health care delivery system, beginning in January 2009.
Main Measures:
Resource Utilization Band variables from the Adjusted Clinical Groups case mix software characterized overall morbidity burden (low, medium, high). Negative binomial regression models described adjusted annual differences in total specialty care visits. Poisson regression models described adjusted annual differences in any use (yes/no) of selected medical and surgical specialties.
Key Results:
Compared to baseline, the study population averaged 7% fewer adjusted specialty visits during implementation (P < 0.001) and 4% fewer adjusted specialty visits in the first post-implementation year (P = 0.02). Patients were 12% less likely to have any cardiology visits during implementation and 13% less likely during the first post-implementation year (P < 0.001). In interaction analysis, patients with low morbidity had at least 27% fewer specialty visits during each of 3 years following baseline (P < 0.001); medium morbidity patients had 9% fewer specialty visits during implementation (P < 0.001) and 5% fewer specialty visits during the first post-implementation year (P = 0.007); high morbidity patients had 3% (P = 0.05) and 5% (P = 0.009) higher specialty use during the first and second post-implementation years, respectively.
Conclusions:
Results suggest that more comprehensive primary care in this PCMH redesign enabled primary care teams to deliver more hypertension care, and that many needs of low morbidity patients were within the scope of primary care practice. New approaches to care coordination between primary care teams and specialists should prioritize high morbidity, clinically complex patients.
Related Concept Videos
 01:23
Hypertension V: Nursing Management
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 01:30
Heart Failure V: Medical Management
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.