Related Experiment Video
Updated: May 3, 2026

Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Cerebral oxygenation during the Richalet hypoxia sensitivity test and cycling time-trial performance in severe
Nicolas Bourdillon1, Jui-Lin Fan, Bengt Kayser
1ISSUL institute of Sport Sciences, University of Lausanne, Lausanne, 1015, Switzerland, nicolas.bourdillon@gmail.com.

Background:
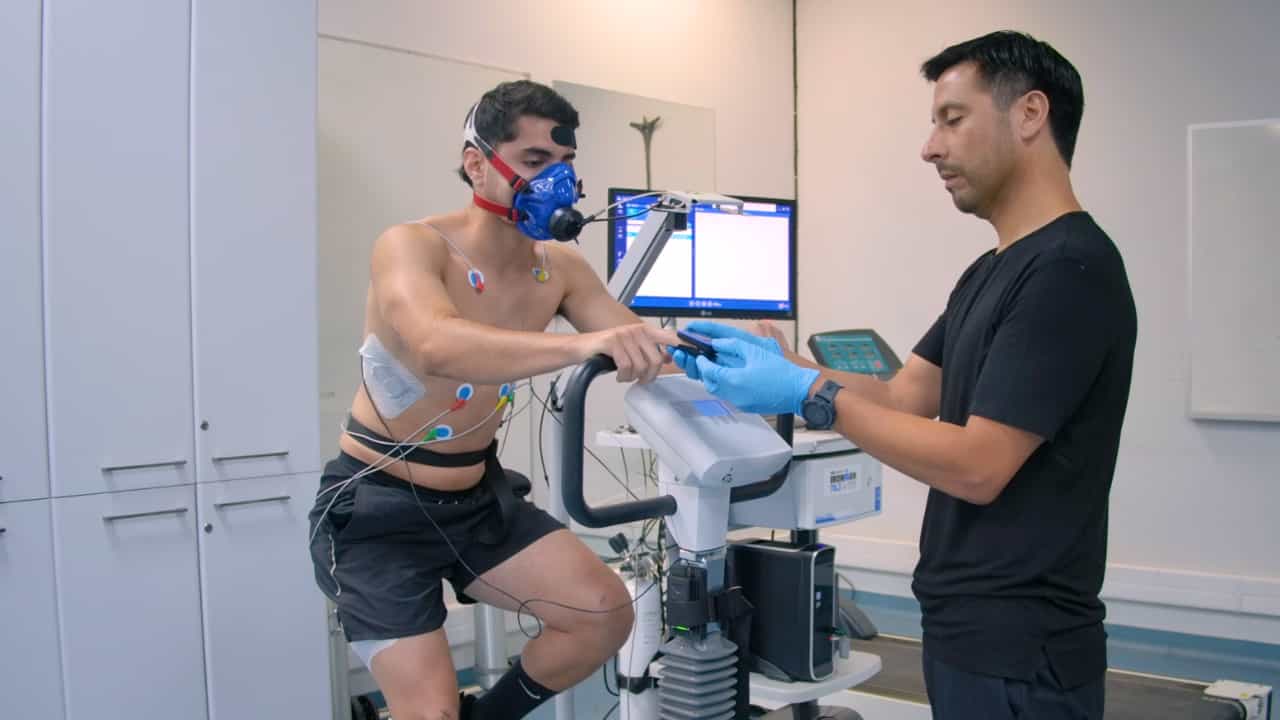
The Richalet hypoxia sensitivity test (RT), which quantifies the cardiorespiratory response to acute hypoxia during exercise at an intensity corresponding to a heart rate of ~130 bpm in normoxia, can predict susceptibility of altitude sickness. Its ability to predict exercise performance in hypoxia is unknown.
Objectives:
Investigate: (1) whether cerebral blood flow (CBF) and cerebral tissue oxygenation (O2Hb; oxygenated hemoglobin, HHb; deoxygenated hemoglobin) responses during RT predict time-trial cycling (TT) performance in severe hypoxia; (2) if subjects with blunted cardiorespiratory responses during RT show greater impairment of TT performance in severe hypoxia.
Study Design:
Thirteen men [27 ± 7 years (mean ± SD), Wmax: 385 ± 30 W] were evaluated with RT and the results related to two 15 km TT, in normoxia and severe hypoxia (FIO2 = 0.11).
Results:
During RT, mean middle cerebral artery blood velocity (MCAv: index of CBF) was unaltered with hypoxia at rest (p > 0.05), while it was increased during normoxic (+22 ± 12 %, p < 0.05) and hypoxic exercise (+33 ± 17 %, p < 0.05). Resting hypoxia lowered cerebral O2Hb by 2.2 ± 1.2 μmol (p < 0.05 vs. resting normoxia); hypoxic exercise further lowered it to -7.6 ± 3.1 μmol below baseline (p < 0.05). Cerebral HHb, increased by 3.5 ± 1.8 μmol in resting hypoxia (p < 0.05), and further to 8.5 ± 2.9 μmol in hypoxic exercise (p < 0.05). Changes in CBF and cerebral tissue oxygenation during RT did not correlate with TT performance loss (R = 0.4, p > 0.05 and R = 0.5, p > 0.05, respectively), while tissue oxygenation and SaO2 changes during TT did (R = -0.76, p < 0.05). Significant correlations were observed between SaO2, MCAv and HHb during RT (R = -0.77, -0.76 and 0.84 respectively, p < 0.05 in all cases).
Conclusions:
CBF and cerebral tissue oxygenation changes during RT do not predict performance impairment in hypoxia. Since the changes in SaO2 and brain HHb during the TT correlated with performance impairment, the hypothesis that brain oxygenation plays a limiting role for global exercise in conditions of severe hypoxia remains to be tested further.

Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Hypoxia
Types of Hypoxia
There are four primary types of hypoxia, each resulting from a different cause:
1. Anemic hypoxia: This type occurs due to insufficient oxygen delivery caused by a lack of red blood cells (RBCs) or RBCs with abnormal or...
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is...
 01:27
Oxygen Transport in the Blood
 01:23
Acute Respiratory Failure-IV