Related Experiment Video
Updated: May 3, 2026


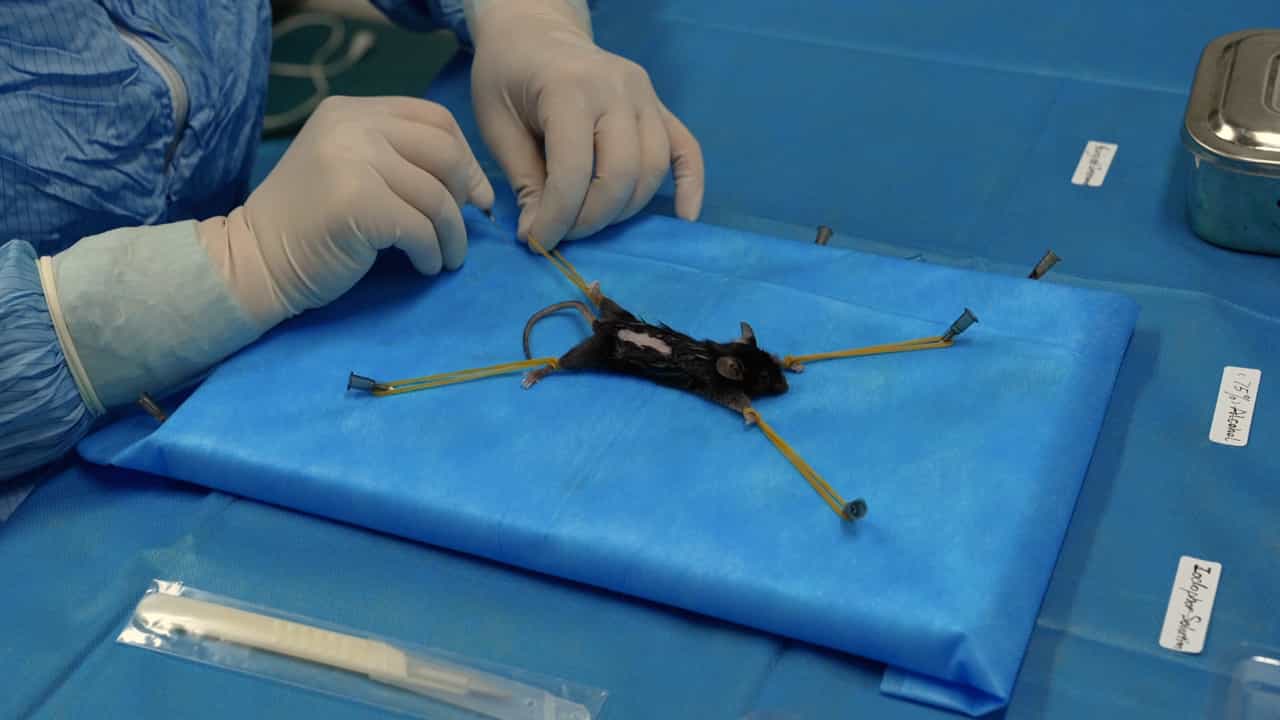
A Hyperandrogenic Mouse Model to Study Polycystic Ovary Syndrome
Published on: October 2, 2018
Hyperandrogenic oligomenorrhea and metabolic risks across menopausal transition
Alex J Polotsky1, Amanda A Allshouse, Sybil L Crawford
1Department of Obstetrics and Gynecology (A.J.P., A.A.A., N.S.), University of Colorado Denver, and Department of Biostatistics and Informatics (A.A.A.), School of Public Health, University of Colorado Denver, Aurora, Colorado 80045; Department of Epidemiology, Preventive, and Behavioral Medicine (S.L.C.), University of Massachusetts Medical School, Worcester, Massachusetts 01655; School of Public Health (S.D.H.), University of Michigan, Ann Arbor, Michigan 48109; Department of Community Health (N.K.), Boonshoft School of Medicine, Wright State University, Dayton, Ohio 45420; Department of Endocrinology and Preventive Cardiology (R.K.), Rush University, Chicago, Illinois 60612; and Department of Obstetrics and Gynecology (R.S.L.), Penn State College of Medicine, Hershey, Pennsylvania 17033.

Context:
Although there is evidence of metabolic risks in young women with irregular menses and androgen excess, persistence of risks after menopause is unclear.
Objective:
The objective of the study was to determine the impact of menopause on the cardiometabolic profile in women with high androgens and a history of menstrual irregularity.
Methods:
Study of Women's Health Across the Nation is a longitudinal cohort study. Data from 1929 women without metabolic syndrome (MetS) at baseline were analyzed for incidence of MetS, self-reported stroke, and myocardial infarction. Cox hazard ratios (HRs) were estimated, adjusting for age, ethnicity, body mass, smoking, menopausal status, and study site.
Results:
Among MetS-free women at baseline, 497 new cases were identified during 20 249 woman-years of follow-up over 12 years. Women with hyperandrogenemia (HA) and oligomenorrhea (Oligo) developed incident cases of MetS at a comparable rate compared with their counterparts: eumenorrheic, normoandrogenic women [HR 1.4 (0.9-2.2)], oligomenorrheic, normoandrogenic women [HR 1.3 (0.8-2.2)], and eumenorrheic hyperandrogenic women [HR 1.2 (0.7-1.8)]. Smoking and obesity were the strongest predictors of incident MetS. There was no significant difference in incidence of self-reported stroke or MI by HA/Oligo status.
Conclusions:
Longitudinal evidence suggests that a history of androgen excess and menstrual irregularity is not associated with worsening of metabolic health after menopause. Our findings challenge the notion that a history of concurrent HA and Oligo reflects ongoing cardiometabolic risk in postmenopausal women.
More Related Videos
 05:32
Author Spotlight: Investigating the Relationship Between FSH and Pathophysiological Changes in Perimenopausal Women - Insights from a Mouse Model
Published on: August 11, 2023
 14:26
A Method to Study the Impact of Chemically-induced Ovarian Failure on Exercise Capacity and Cardiac Adaptation in Mice
Published on: April 7, 2014
Related Concept Videos
 01:28
Menopause
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:24
Disorders of the Female Reproductive System
 01:40
Hormonal Regulation
 01:33
Hormonal Regulation