Related Experiment Video
Updated: May 3, 2026
Author Spotlight: Integrating Ultrasound Imaging with Biochemical Markers for Thyroid Disease Diagnosis
Published on: February 9, 2024
A 2013 survey of clinical practice patterns in the management of primary hypothyroidism
Henry B Burch1, Kenneth D Burman, David S Cooper
1Endocrinology Division (H.B.B.), Walter Reed National Military Medical Center, Bethesda, Maryland 20889, and Uniformed Services University of Health Sciences, Bethesda, Maryland 20814; Endocrinology Section (K.D.B.), Washington Hospital Center, Washington, DC 20010; Georgetown University Medical Center (K.D.B.), Washington, DC 20007; Division of Endocrinology (D.S.C.), The Johns Hopkins University School of Medicine, Baltimore, Maryland 21205; Division of Endocrinology (J.V.H.), Beth Israel Deaconess Medical Center, Boston, Massachusetts 02215; and Harvard Medical School (J.V.H.), Boston, Massachusetts 02115.

Context:
In 2012, comprehensive clinical practice guidelines (CPGs) were published regarding the management of hypothyroidism.
Objective:
We sought to document current practices in the management of primary hypothyroidism and compare these results with recommendations made in the 2012 American Thyroid Association (ATA)/American Association of Clinical Endocrinologists (AACE) hypothyroidism CPGs. In addition, we sought to examine differences in management among international members of U.S.-based endocrine societies and to compare survey results with those obtained from a survey of ATA members performed 12 years earlier.
Methods:
Clinical members of The Endocrine Society (TES), the ATA, and the AACE were asked to take a web-based survey consisting of 30 questions dealing with testing, treatment, and modulating factors in the management of primary hypothyroidism.
Results:
In total, 880 respondents completed the survey, including 618 members of TES, 582 AACE members, and 208 ATA members. North American respondents accounted for 67.6%, Latin American 9.7%, European 9.2%, Asia and Oceania 8.1%, and Africa and Middle East 5.5%. Overt hypothyroidism would be treated using l-T4 alone by 99.2% of respondents; 0.8% would use combination l-T4 and liothyronine (l-T3) therapy. Generic l-T4 would be used by 49.3% and a brand name by 49.9%. The rate of replacement would be gradual (38.5%); an empiric dose, adjusted to achieve target (33.6%); or a calculated full replacement dose (27.8%). A target TSH of 1.0 to 1.9 mU/L was favored in the index case, but 3.0 to 3.9 mU/L was the most commonly selected TSH target for an octogenarian. Persistent hypothyroid symptoms despite achieving a target TSH would prompt testing for other causes by 84.3% of respondents, a referral to primary care by 11.3%, and a change to l-T4 plus l-T3 therapy by 3.6%. Evaluation of persistent symptoms would include measurement of T3 levels by 21.9% of respondents. Subclinical disease with a TSH 5.0 to 10.0 mU/L would be treated without further justification by 21.3% of respondents, or in the presence of positive thyroid peroxidase antibodies (62.3%), hypothyroid symptoms (60.9%), high low-density lipoprotein (52.9%), or goiter (46.6%). The TSH target for a newly pregnant patient was <2.5 mU/L for 96.1% of respondents, with 63.5% preferring a TSH target <1.5 mU/L. Thyroid hormone levels would be checked every 4 weeks during pregnancy by 67.7% and every 8 weeks by an additional 21.4%. A hypothyroid patient with TSH of 0.5 mU/L who becomes pregnant would receive an immediate l-T4 dose increase by only 36.9% of respondents.
Conclusion:
The current survey of clinical endocrinologists catalogs current practice patterns in the management of hypothyroidism and demonstrates 1) a nearly exclusive preference for l-T4 alone as initial therapy, 2) the widespread use of age-specific TSH targets for replacement therapy, 3) a low threshold for treating mild thyroid failure, 4) meticulous attention to TSH targets in the pregnant and prepregnant woman, and 5) a highly variable approach to both the rate and means of restoring euthyroidism for overt disease. Both alignment and focal divergence from recent CPGs are demonstrated.
Related Concept Videos
 01:23
Hypothyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:20
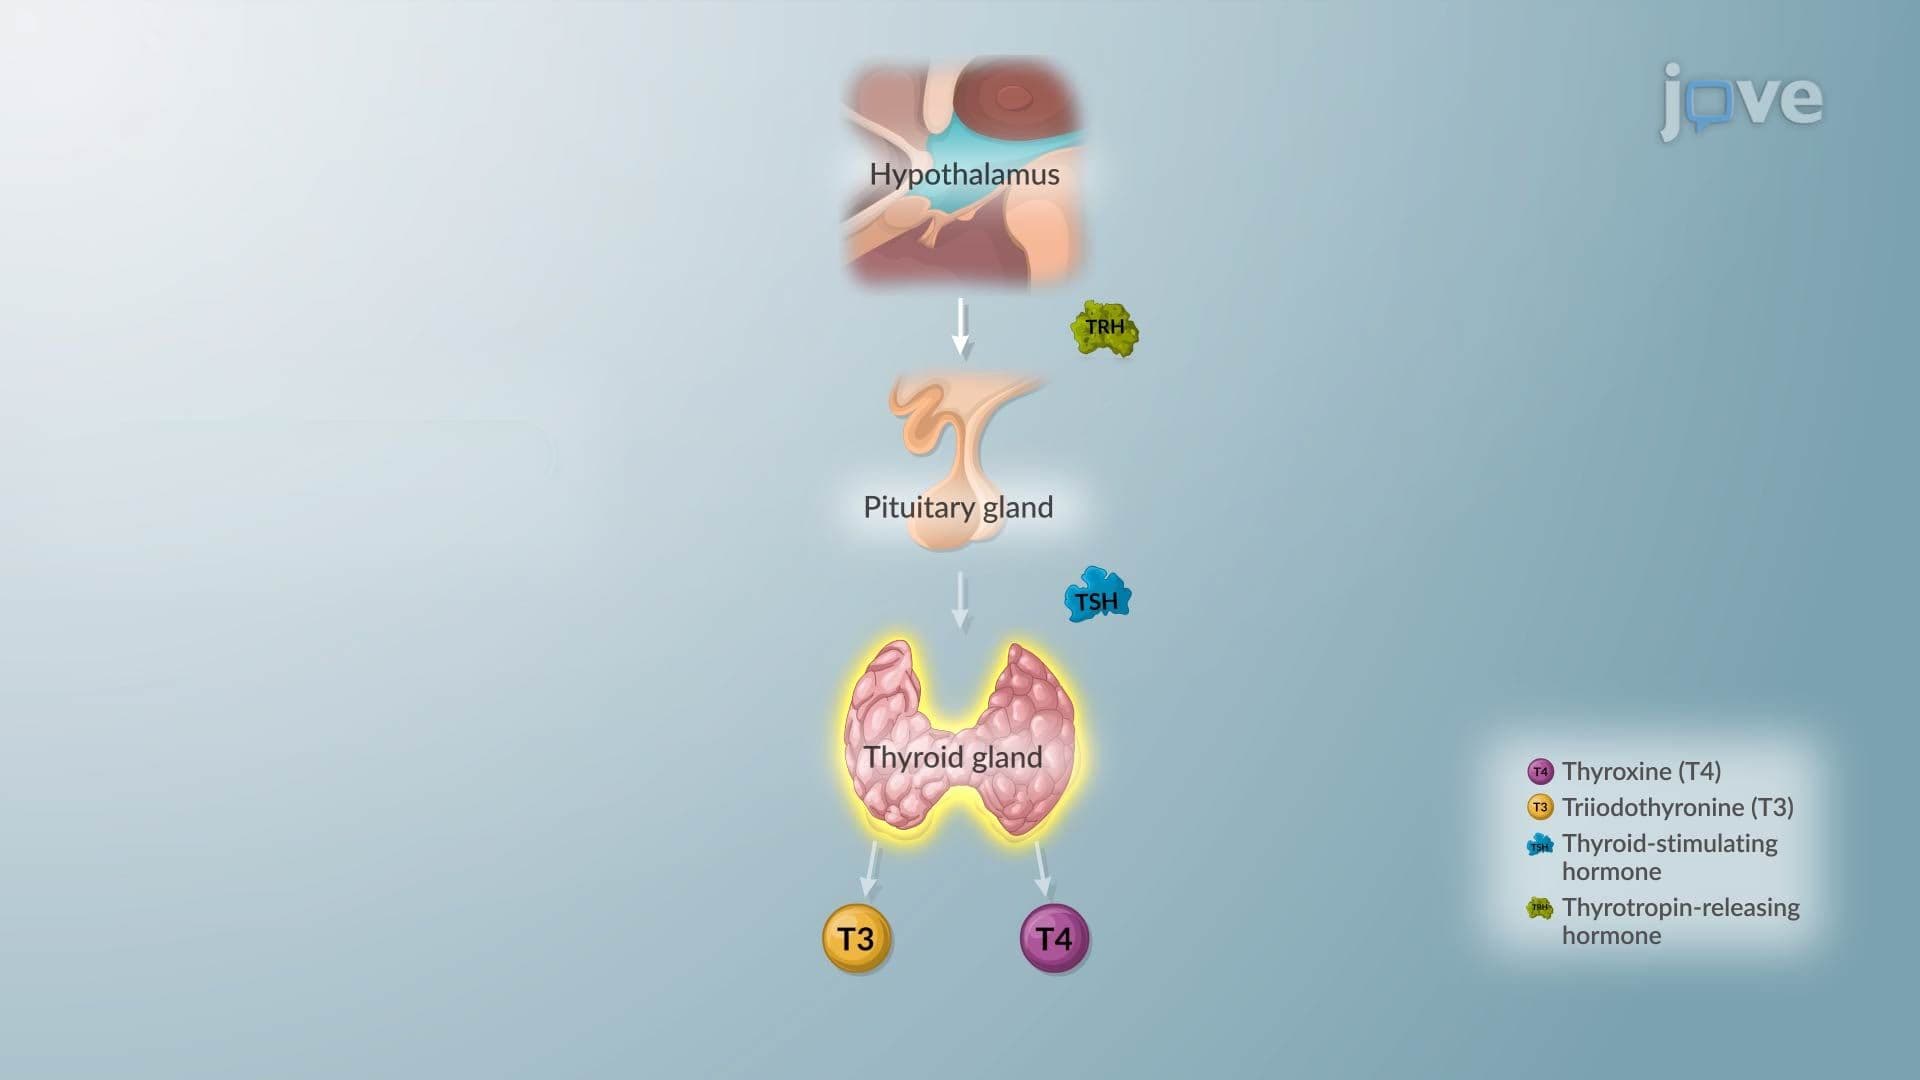
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The...
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:28
Graves' Disease I: Introduction