Related Experiment Video
Updated: May 3, 2026


A Cell Culture Model for Producing High Titer Hepatitis E Virus Stocks
Published on: June 26, 2020
An update on hepatitis B, D, and E viruses
1University of California San Francisco, San Francisco, CA, USA.

Insights
Non-HCV viral hepatitis, including hepatitis B virus (HBV) and hepatitis D virus (HDV) coinfection, poses significant liver disease risks, particularly in HIV-infected individuals. Treatment options exist but require careful consideration for optimal patient outcomes.
Area of Science:
- Hepatology
- Infectious Diseases
- Virology
Background:
- Non-hepatitis C virus (HCV) viral hepatitis remains a significant cause of liver disease, especially in individuals with human immunodeficiency virus (HIV).
- Hepatitis B virus (HBV) is a leading cause of cirrhosis globally, with a substantial risk of decompensated liver disease.
- Hepatitis D virus (HDV) coinfection with HBV exacerbates liver disease severity and mortality.
Purpose of the Study:
- To summarize current understanding and treatment approaches for non-HCV viral hepatitis, focusing on HBV, HDV, and hepatitis E virus (HEV) in the context of HIV infection.
- To highlight the clinical significance and management challenges of viral hepatitis in immunocompromised populations.
Main Methods:
- Review of existing literature and clinical guidelines on HBV, HDV, and HEV management.
- Summary of expert presentation on viral hepatitis in HIV-infected individuals.
Main Results:
- Chronic HBV infection treatment involves peginterferon alfa, entecavir, or tenofovir.
- HBV/HDV coinfection leads to more severe hepatitis and increased mortality compared to HBV monoinfection.
- Peginterferon alfa is the primary treatment for HDV infection.
- Hepatitis E virus (HEV) can cause chronic infection in immunosuppressed patients, rapidly leading to cirrhosis, with no established treatment guidelines for HIV-infected individuals.
Conclusions:
- Non-HCV viral hepatitis, particularly HBV/HDV coinfection and chronic HEV in HIV-infected persons, presents serious risks for liver disease progression.
- Current treatment strategies for HBV and HDV are established, but management of HEV in this population requires further guideline development.
Abstract:
Although newer and more effective treatments are now available for hepatitis C virus (HCV) infection, non-HCV viral hepatitis remains an important cause of liver disease, especially among HIV-infected individuals. Hepatitis B virus (HBV) is the leading cause of cirrhosis worldwide, and approximately one-quarter of patients with cirrhosis develop decompensated liver disease within 5 years. Initial treatment for chronic HBV infection includes peginterferon alfa, entecavir, and tenofovir. Approximately 15 million of the estimated 350 million individuals with chronic HBV infection have evidence of exposure to hepatitis D (delta) virus (HDV), which requires hepatitis B surface antigen for transmission and packaging. HBV/HDV coinfection is associated with more severe acute hepatitis and higher mortality than acute HBV monoinfection. Chronic coinfection is associated with a higher risk of cirrhosis and decompensated liver disease. The mainstay of treatment for HDV infection is peginterferon alfa for at least 48 weeks. Cases of hepatitis E virus (HEV) infection in HIV-infected persons have been reported. HEV infection can become chronic in immunosuppressed patients, and chronic infection is associated with rapid development of cirrhosis. There are no established guidelines for treating HEV infection in HIV-infected persons. This article summarizes a presentation by Jennifer Price, MD, at the IAS-USA continuing education program held in San Francisco, California, in June 2013.


Related Concept Videos
 01:25
Hepatitis
 01:28
Viral Hepatitis I: Introduction
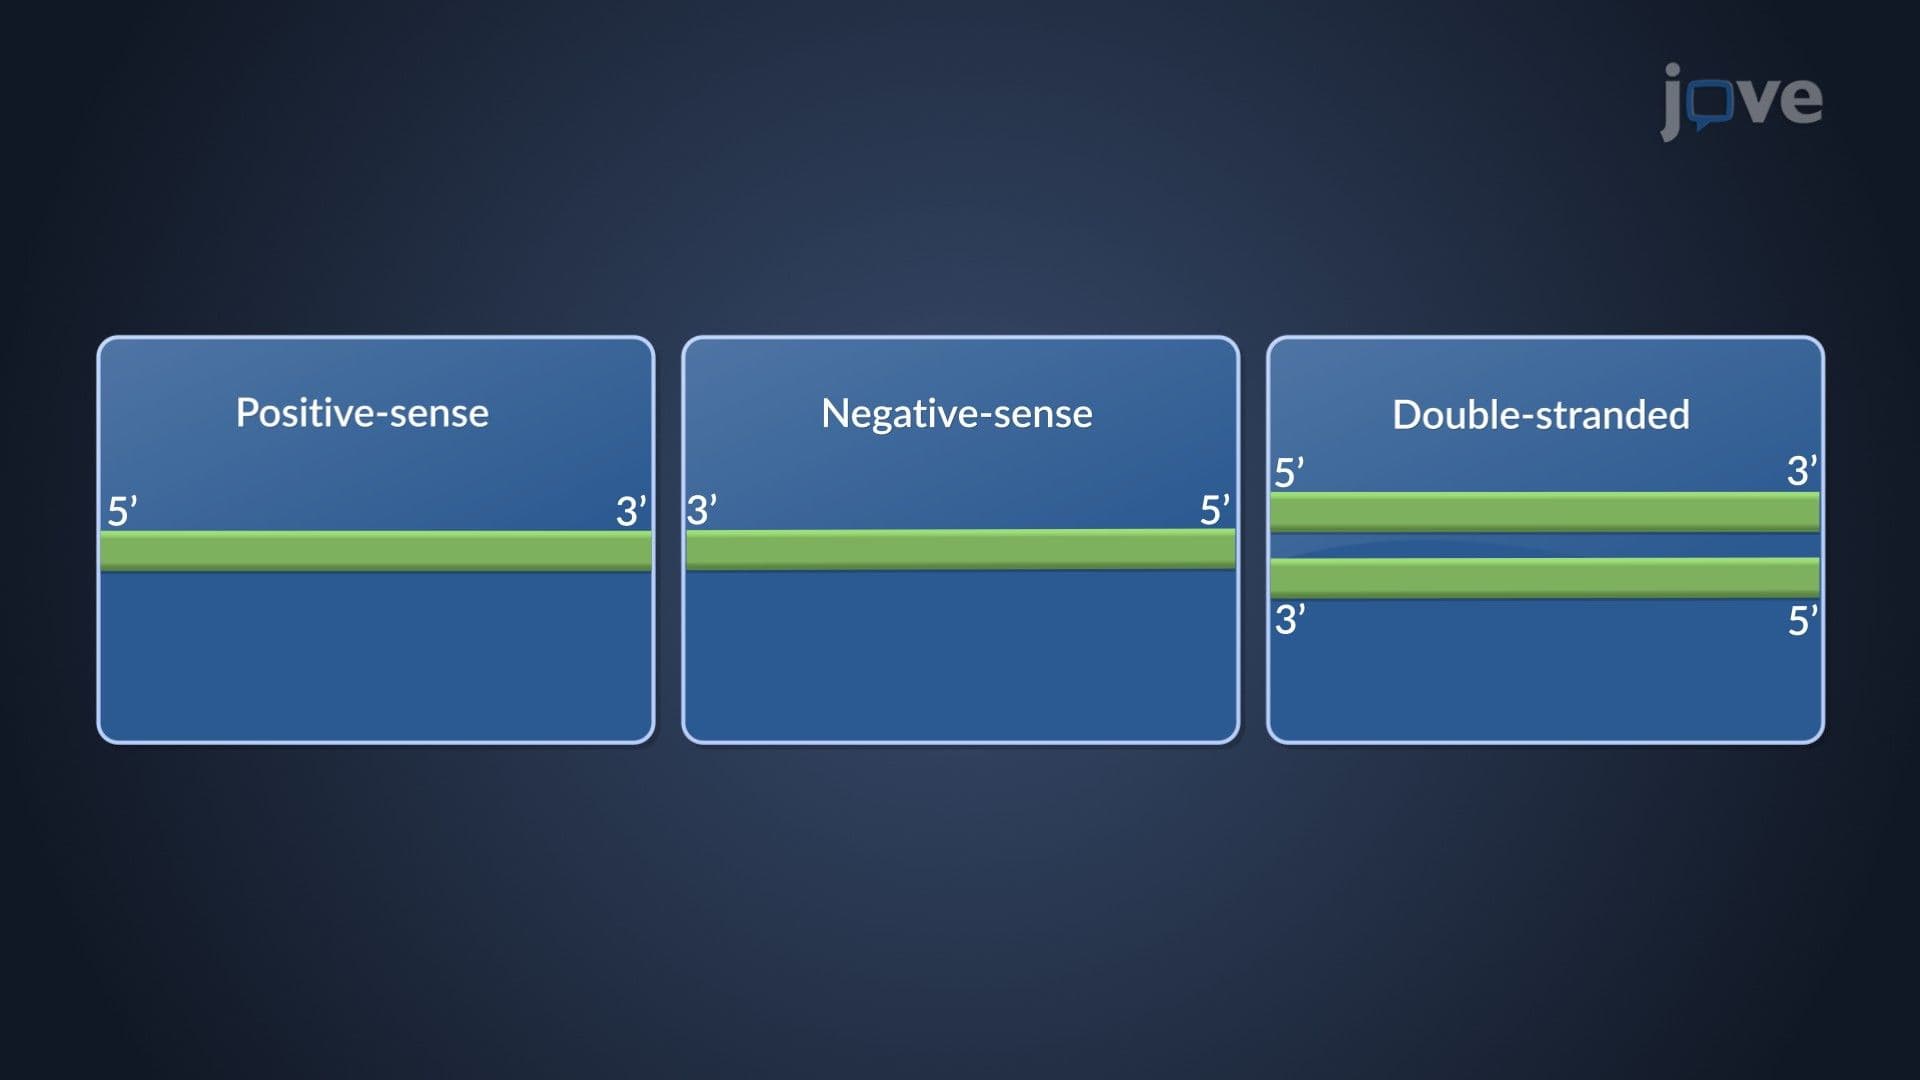 01:29
Viruses with RNA Genomes
 01:26
Human Virome
 01:25
Arboviral Encephalitis
 01:30
Inhibitors of Viral Protein Synthesis