Related Experiment Video
Updated: May 2, 2026
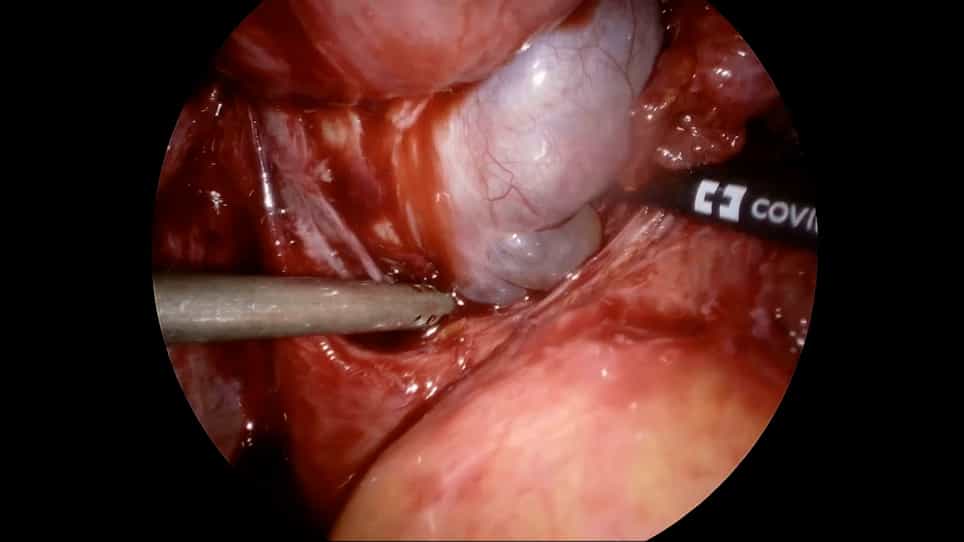

Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
Preoperative risk stratification of adnexal masses: can we predict the optimal surgical management?
Erin M Rogers1, Giovanny Casadiego Cubides2, Judith Lacy1
1Division of Pediatric Gynecology, Hospital for Sick Children, University of Toronto, Toronto, ON, Canada.

Insights
Preoperative ultrasonography identifying complex adnexal masses ≥8 cm accurately guides surgical approach in pediatric patients. This improves management, reducing unnecessary laparotomies for benign conditions while ensuring open surgery for malignancies.
Area of Science:
- Pediatric Surgery
- Gynecologic Oncology
- Diagnostic Imaging
Background:
- Adnexal masses are common in pediatric patients, requiring careful surgical management.
- Accurate preoperative risk stratification is crucial for selecting the appropriate surgical approach.
- Distinguishing benign from malignant adnexal masses preoperatively can be challenging.
Purpose of the Study:
- To characterize preoperative risk factors for adnexal masses in pediatric patients.
- To identify accurate surgical approaches for benign and malignant adnexal masses.
- To evaluate the utility of ultrasonographic findings in surgical planning.
Main Methods:
- Retrospective chart review of 129 pediatric and adolescent patients with surgically managed adnexal masses (2001-2006).
- Analysis of ultrasonographic characteristics (size, complexity), surgical approach (laparoscopy vs. laparotomy), and procedure (cystectomy vs. oophorectomy).
- Statistical assessment using Fisher Exact test to compare outcomes.
Main Results:
- Malignant masses were significantly more likely to be treated with laparotomy (98.6%) compared to benign masses (laparoscopy, 97%).
- Complex masses ≥8 cm on ultrasonography were highly indicative of malignancy (100%).
- Combining ultrasonographic complexity and size (≥8 cm) achieved 100% sensitivity for malignancy and 100% negative predictive value.
Conclusions:
- Preoperative ultrasonographic assessment of complexity and size (≥8 cm) is effective in risk stratification for pediatric adnexal masses.
- These criteria help minimize unnecessary laparotomies for benign masses while ensuring prompt open surgical management for malignancies.
- Findings support tailored surgical strategies based on imaging characteristics to optimize patient outcomes.
Study Objective:
To characterize preoperative risk stratification with aim of identifying the accurate surgical approach of benign and malignant adnexal masses in pediatric patients.
Design:
A retrospective chart review of all cases of adnexal masses surgically managed between January 2001 and December 2006.
Setting:
The Hospital for Sick Children, Toronto, Canada.
Participants:
129 cases of 126 pediatric and adolescent patients who underwent operative management of their adnexal masses.
Main Outcome Measures:
Ultrasonographic characteristics (cyst size and character), surgical approach (laparoscopy vs laparotomy) and method of cyst removal (cystectomy vs oophorectomy). Data was assessed with a Fisher Exact test where appropriate (P < .05).
Results:
Malignancies were more frequently treated by laparotomy (n = 14, 98.6%, P < .001), and benign cases by laparoscopy (n = 78, 97%, P < .001). On ultrasonography, malignant masses were more often complex (n = 16, 100%, P = .006) and ≥8 cm (n = 16, 100%, P < .001) than benign masses (≥8 cm n = 60, 53%, complex n = 76, 67%). Combining ultrasonographic measurements of ≥8 cm and complexity identified 100% of malignant masses (n = 16) and 36% of benign masses (n = 41, P < .001, PPV = 37.1, NPV = 100%). Additional imaging including CT/MRI was ordered by pediatric surgeons (n = 17, 77%) more often than pediatric gynecologists (n = 44, 41%, P = .002). Furthermore, pediatric surgeons managed adnexal masses by oophorectomy (n = 12, 55%) more often as compared to pediatric gynecologists (n = 19, 18%, P < .001).
Conclusion:
Using preoperative characteristics of complexity and ≥8 cm reduces the number of benign masses treated with laparotomy while ensuring malignant masses are managed with an open approach.

