Related Experiment Video
Updated: May 2, 2026
Isolation and Kv Channel Recordings in Murine Atrial and Ventricular Cardiomyocytes
Published on: March 12, 2013
KCNJ2 mutation causes an adrenergic-dependent rectification abnormality with calcium sensitivity and ventricular
Matthew M Kalscheur1, Ravi Vaidyanathan1, Kate M Orland2
1Cellular and Molecular Arrhythmia Research Program, University of Wisconsin-Madison, Wisonsin.

Background:
KCNJ2 mutations are associated with a variety of inherited arrhythmia syndromes including catecholaminergic polymorphic ventricular tachycardia 3.
Objective:
To characterize the detailed cellular mechanisms of the clinically recognized KCNJ2 mutation R67Q.
Methods:
Kir2.1 current density was measured from COS-1 cells transiently transfected with wild-type human Kir-2.1 (WT-Kir2.1) and/or a heterozygous missense mutation in KCNJ2 (R67Q-Kir2.1) by using the whole-cell voltage clamp technique. Catecholamine activity was simulated with protein kinase A-stimulating cocktail exposure. Phosphorylation-deficient mutants, S425N-Kir2.1 and S425N-Kir2.1/R67Q-S425N-Kir2.1, were used in a separate set of experiments. HA- or Myc-Tag-WT-Kir2.1 and HA-Tag-R67Q-Kir2.1 were used for confocal imaging.
Results:
A 33-year-old woman presented with a catecholaminergic polymorphic ventricular tachycardia-like clinical phenotype and was found to have KCNJ2 missense mutation R67Q. Treatment with nadolol and flecainide resulted in the complete suppression of arrhythmias and symptom resolution. Under baseline conditions, R67Q-Kir2.1 expressed alone did not produce inward rectifier current while cells coexpressing WT-Kir2.1 and R67Q-Kir2.1 demonstrated the rectification index (RI) similar to that of WT-Kir2.1. After PKA stimulation, R67Q-Kir2.1/WT-Kir2.1 failed to increase peak outward current density; WT-Kir2.1 increased by 46% (n = 5), while R67Q-Kir2.1/WT-Kir2.1 decreased by 6% (n = 6) (P = .002). Rectification properties in R67Q-Kir2.1/WT-Kir2.1 demonstrated sensitivity to calcium with a decreased RI in the high-calcium pipette solution (RI 20.3% ± 4.1%) than in the low-calcium pipette solution (RI 36.5% ± 5.7%) (P < .05). Immunostaining of WT-Kir2.1 and R67Q-Kir2.1 individually and together showed a normal membrane expression pattern and colocalization by using the Pearson correlation coefficient.
Conclusions:
R67Q-Kir2.1 is associated with an adrenergic-dependent clinical and cellular phenotype with rectification abnormality enhanced by increased calcium. These findings are a significant advancement of our knowledge and understanding of the phenotype-genotype relationship of arrhythmia syndromes related to KCNJ2 mutations.
Insights
The KCNJ2 R67Q mutation causes an adrenergic-dependent cardiac arrhythmia by disrupting Kir2.1 channel function, with abnormalities exacerbated by increased calcium levels. This research deepens understanding of KCNJ2 mutation-related arrhythmia syndromes.
Area of Science:
- Molecular Cardiology
- Ion Channel Physiology
- Genetic basis of Cardiac Arrhythmias
Background:
- KCNJ2 mutations are linked to inherited arrhythmia syndromes, including catecholaminergic polymorphic ventricular tachycardia 3.
- The specific R67Q mutation in KCNJ2 is clinically recognized but its cellular mechanisms require detailed characterization.
Observation:
- A patient with catecholaminergic polymorphic ventricular tachycardia-like symptoms presented with the KCNJ2 R67Q mutation.
- In vitro studies showed R67Q-Kir2.1 channels alone did not produce inward rectifier current.
- Co-expression with wild-type Kir2.1 revealed impaired current density increase upon PKA stimulation and calcium-dependent rectification abnormalities.
Findings:
- The R67Q-Kir2.1 mutation impairs Kir2.1 channel function, leading to an adrenergic-dependent cellular phenotype.
- Abnormal rectification properties of R67Q-Kir2.1 channels are exacerbated by elevated intracellular calcium.
- Despite functional deficits, R67Q-Kir2.1 exhibits normal membrane expression and colocalization patterns.
Implications:
- This study elucidates the cellular mechanisms underlying KCNJ2 R67Q-associated arrhythmias.
- Findings advance the understanding of genotype-phenotype relationships in KCNJ2 mutation-related cardiac disorders.
- The results highlight the role of calcium in modulating KCNJ2 channel dysfunction in arrhythmias.


Related Concept Videos
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:28
Mechanism of Cardiac Arrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:26
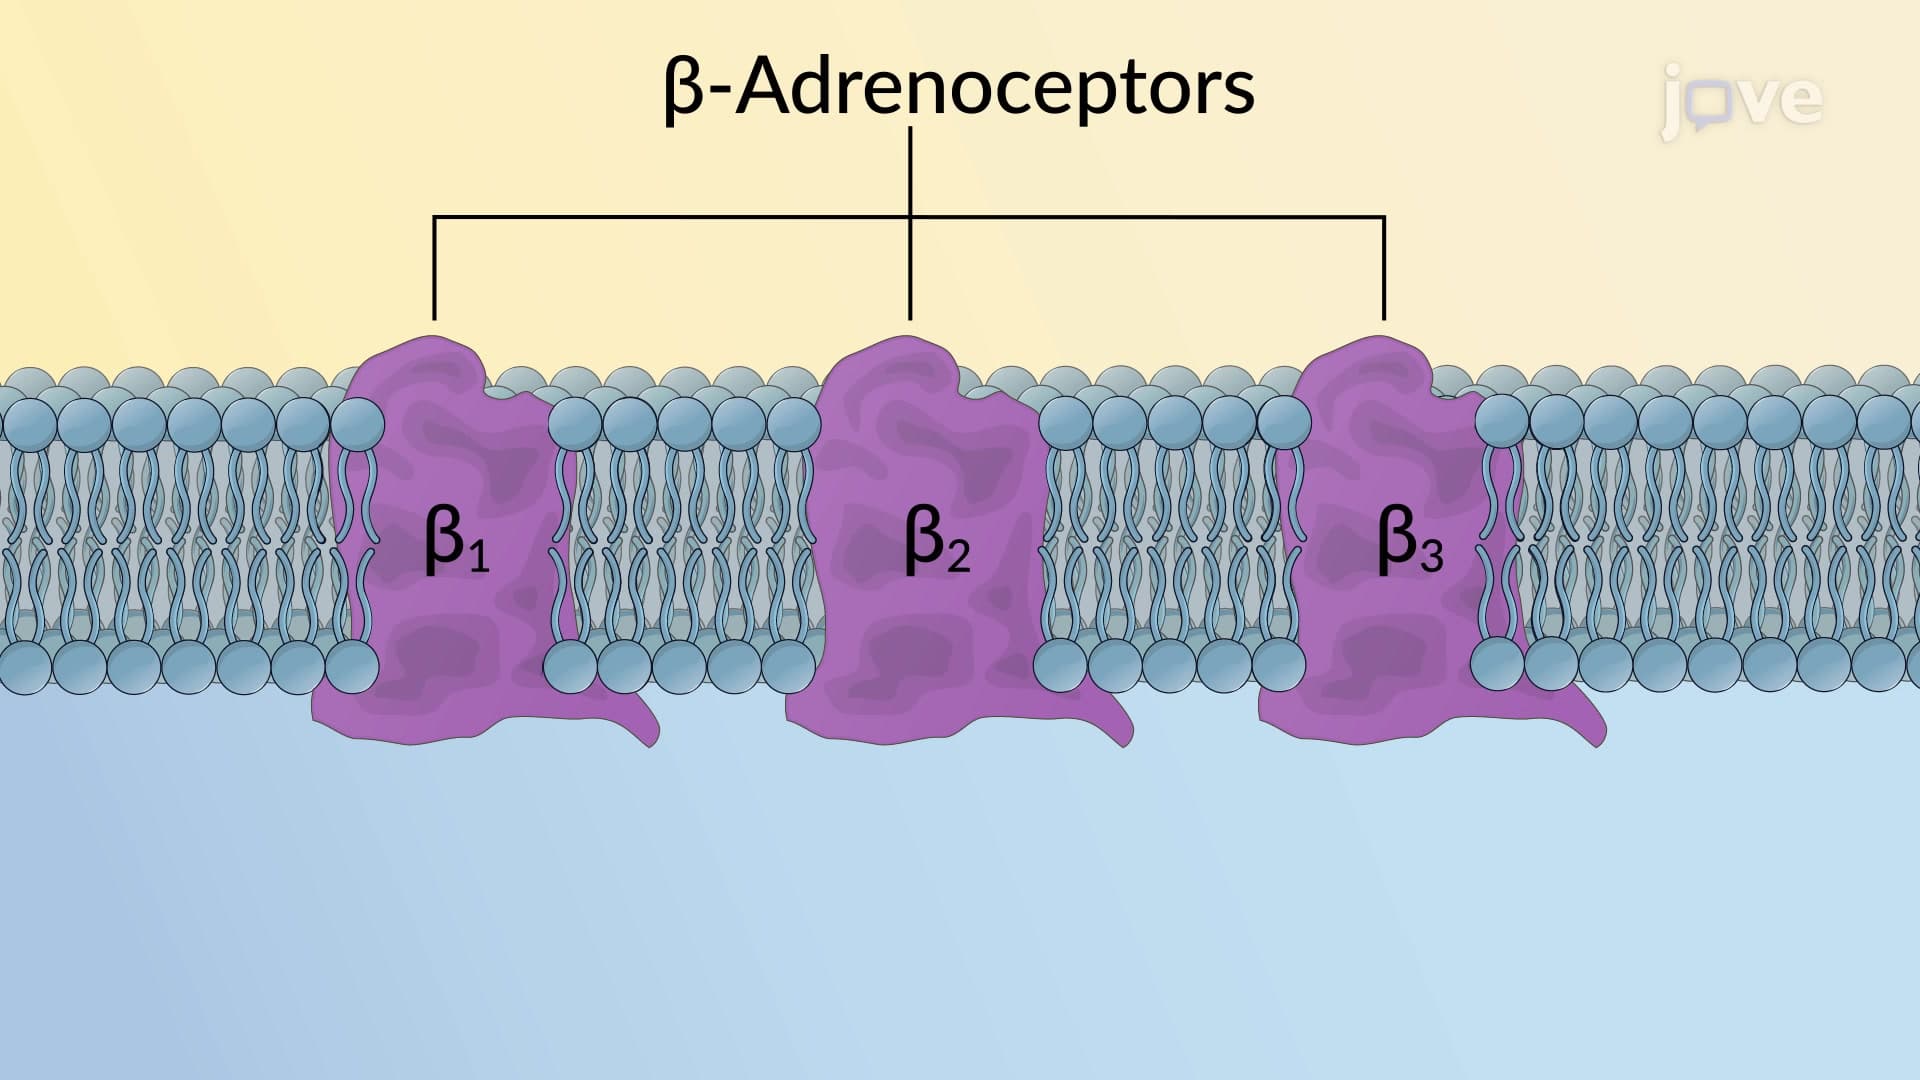
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...