Related Experiment Video
Updated: May 2, 2026
Murine Hind Limb Long Bone Dissection and Bone Marrow Isolation
Published on: April 14, 2016
Giant cell tumour of bone in the appendicular skeleton: an analysis of 276 cases
Rong Xing1, Jin Yang1, Qingquan Kong1
1Department of Orthopaedic Surgery, West China Hospital, West China Medical School, Sichuan University, Guoxue Road 37, Wuhou District, Chengdu 610041, China.

Abstract:
This retrospective study analyzed 276 cases of giant cell tumour of bone in the appendicular skeleton of patients first diagnosed and treated at the Orthopaedic Department of the West China Hospital in Sichuan University between 1988 and 2007. Fifty-eight percent of the tumours involved the knee region. The most common primary treatment was curettage (162 patients) combined with adjuvant local therapy. The effects of bone cement (PMMA), high-speed burring, electro- cauterization, liquid nitrogen, and phenol on the recurrence rate were also analyzed. The differences in local recurrence rates were analyzed between giant-cell tumours confined to bone (Campanacci grades I and II) and giant-cell tumours with extraosseous extension (Campanacci grade III) treated with intralesional curettage. The recurrence rate of patients who received the first treatment at our institution was 11.2%. Recurrence was observed in 31 cases and multiple recurrences were observed in 5 cases. Treatment included intralesional curettage (173%), marginal excision (143%), wide excision (1.9%), or radical resection (0%). Metastases, which mainly involved the lung, occurred in 6 cases (2.2%). There was a significantly lower recurrence rate (p = 0.004) following intralesional curettage combined with high-speed burring (n = 102) as compared with intralesional curettage without high-speed burring (n = 60). Although the efficacy of liquid nitrogen and electrocauterization did not reach significance, they seem to have a similar effect to high-speed burring. Therefore, we recommend high-speed burring as a necessary adjuvant therapy. The combination of all adjuvants (burring, liquid nitrogen, and electro-cauterization) is recommended as a standard treatment. Cement filling of the cavity after curettage was not widely used in this series, but its merits have been reported in several studies; we therefore recommend that cement filling should be added to the adjuvants to be used after burring, liquid nitrogen and/or electrocauterization.

Related Concept Videos
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:02
What is the Skeletal System?
 01:09
Overview of the Axial Skeleton
The axial skeleton of the...
 01:19
Appendicitis
 01:17
Gross Anatomy of Bone
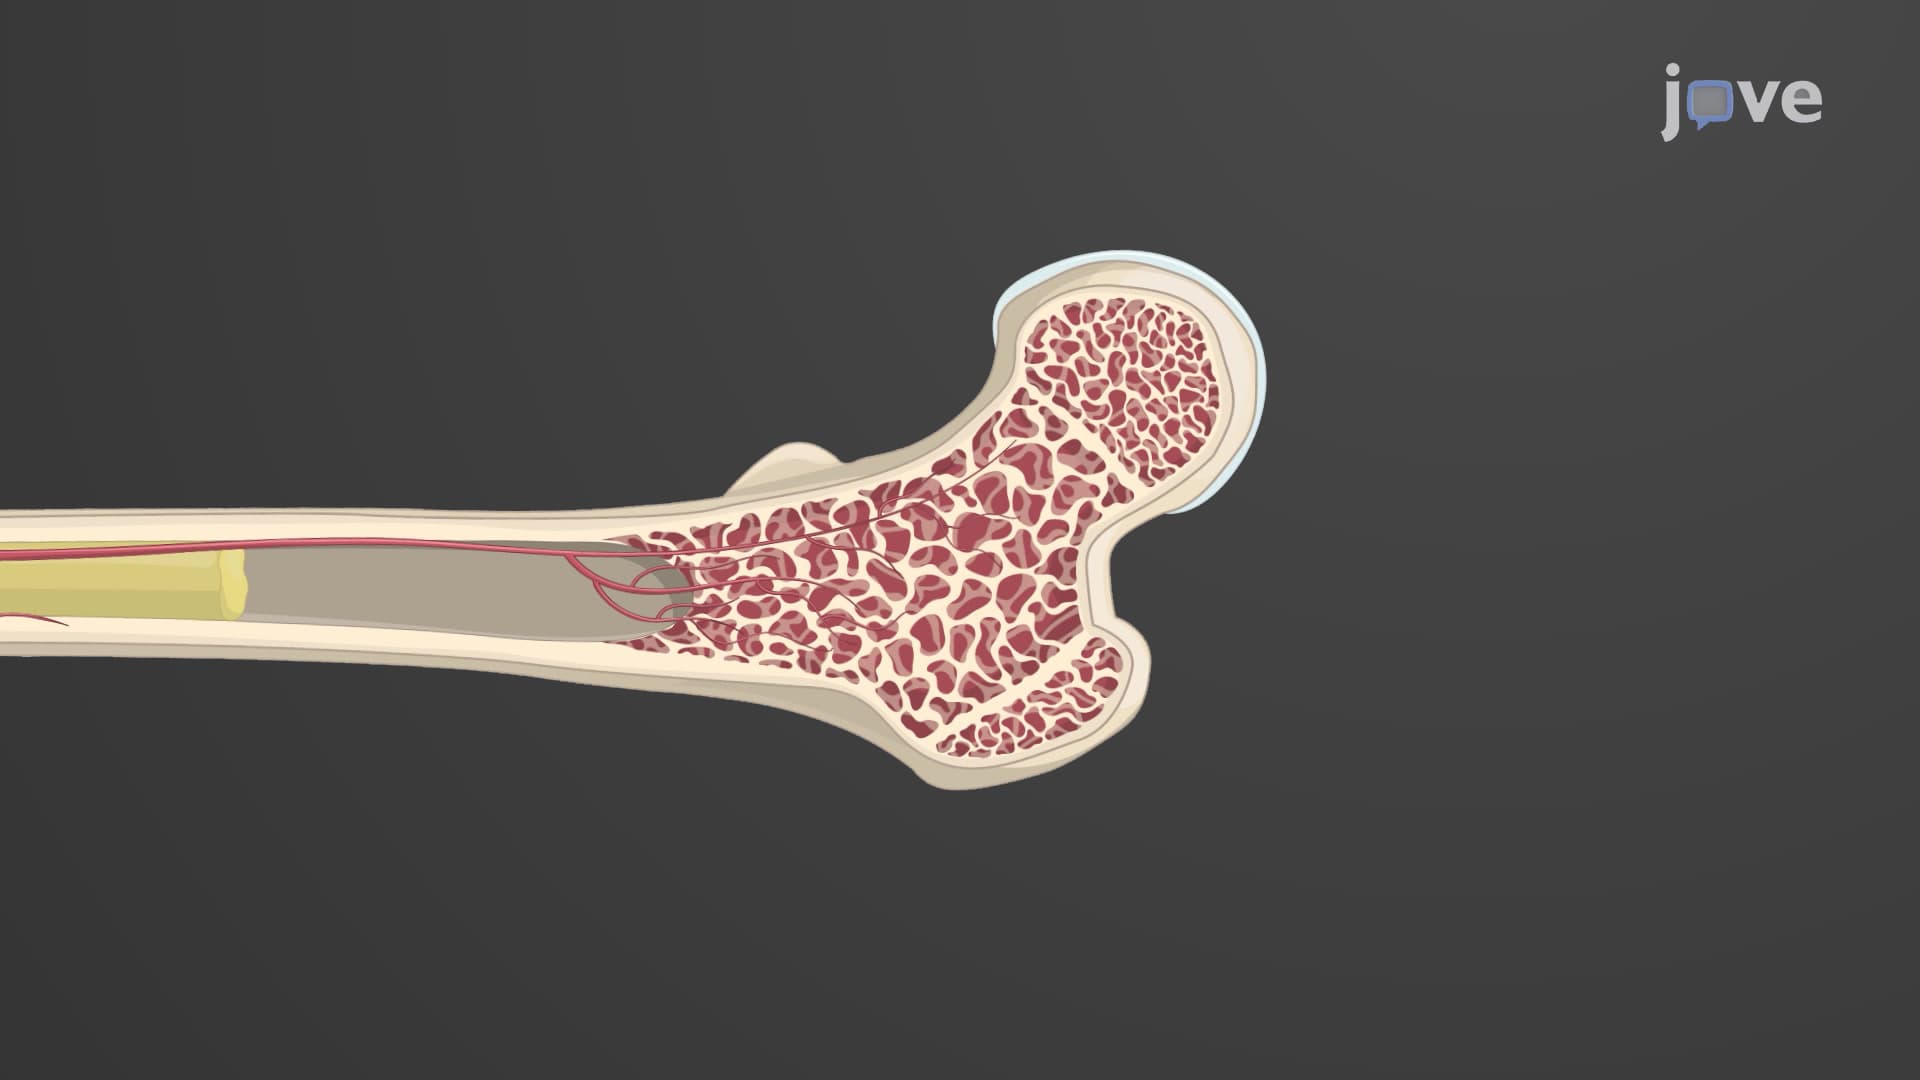
The diaphysis is the tubular shaft that runs between the proximal and distal ends of the bone. The walls of the diaphysis are composed of dense and hard compact bone made of numerous osteons — the functional unit of the compact bone. The hollow region in the diaphysis is called the medullary cavity, which harbors the bone marrow. In infants and children, this marrow cavity is filled with red marrow, whereas in...