Related Experiment Video
Updated: May 2, 2026


Antimicrobial Synergy Testing by the Inkjet Printer-assisted Automated Checkerboard Array and the Manual Time-kill Method
Published on: April 18, 2019
In vitro assessment and multicenter cohort study of comparative nephrotoxicity rates associated with colistimethate
Kady Phe1, Yuman Lee, Patrick M McDaneld
1Department of Pharmacy, St. Luke's Episcopal Hospital, Houston, Texas, USA.

Abstract:
Despite concerns of nephrotoxicity, polymyxin antibiotics often remain the only susceptible agents for multidrug-resistant (MDR) Gram-negative bacteria. Colistin has been more commonly used clinically due to a perceived safety benefit. We compared the nephrotoxicity of colistin to polymyxin B. The in vitro cytotoxicity of colistin was compared to polymyxin B in two mammalian renal cell lines. To validate the clinical relevance of the findings, we evaluated adult patients with normal renal function who received a minimum of 72 h of polymyxin therapy in a multicenter study. The primary outcome was the prevalence of nephrotoxicity, as defined by the RIFLE (risk, injury, failure, loss, end-stage kidney disease) criteria. Colistin exhibited an in vitro cytotoxicity profile similar to polymyxin B. A total of 225 patients (121 receiving colistimethate, 104 receiving polymyxin B) were evaluated. Independent risk factors for colistimethate-associated nephrotoxicity included age (odds ratio [OR], 1.04; 95% confidence interval [CI], 1.00 to 1.07; P = 0.03), duration of therapy (OR 1.08; 95% CI, 1.02 to 1.15; P = 0.02), and daily dose by ideal body weight (OR 1.40; 95% CI, 1.05 to 1.88; P = 0.02). In contrast, cystic fibrosis was found to be a protective factor in patients who received colistimethate (OR, 0.03; 95% CI, 0.001 to 0.79; P = 0.04). In a matched analysis based on the risk factors identified (n = 76), the prevalence of nephrotoxicity was higher with colistimethate than with polymyxin B (55.3% versus 21.1%; P = 0.004). Polymyxin B was not found to be more nephrotoxic than colistin and may be the preferred polymyxin for MDR infections. A prospective study comparing the two polymyxins directly is warranted.
Insights
Polymyxin B may be a safer choice than colistin for treating multidrug-resistant infections, as it showed lower nephrotoxicity in a comparative study. Further research is needed to confirm these findings.
Area of Science:
- Nephrology
- Infectious Diseases
- Pharmacology
Background:
- Polymyxins are crucial for treating multidrug-resistant Gram-negative bacterial infections.
- Colistin is frequently used due to a perceived lower risk of kidney toxicity compared to polymyxin B.
- Nephrotoxicity remains a significant concern with polymyxin antibiotic use.
Purpose of the Study:
- To compare the in vitro cytotoxicity and in vivo nephrotoxicity of colistin and polymyxin B.
- To identify risk factors associated with colistin-induced nephrotoxicity.
- To determine the preferred polymyxin agent for multidrug-resistant infections.
Main Methods:
- In vitro cytotoxicity assays were performed on two mammalian renal cell lines.
- A multicenter study evaluated adult patients receiving at least 72 hours of polymyxin therapy.
- Nephrotoxicity was assessed using the RIFLE criteria, with risk factors analyzed via logistic regression.
Main Results:
- In vitro, colistin and polymyxin B demonstrated similar cytotoxicity profiles.
- Independent risk factors for colistin nephrotoxicity included older age, longer duration of therapy, and higher daily dose.
- In a matched analysis, colistin treatment resulted in a significantly higher prevalence of nephrotoxicity (55.3%) compared to polymyxin B (21.1%).
Conclusions:
- Polymyxin B demonstrated a lower prevalence of nephrotoxicity compared to colistin in this study.
- Colistin-associated nephrotoxicity is linked to specific patient and treatment factors.
- Polymyxin B may be a preferred agent for multidrug-resistant infections, warranting direct comparative prospective trials.


Related Concept Videos
 01:24
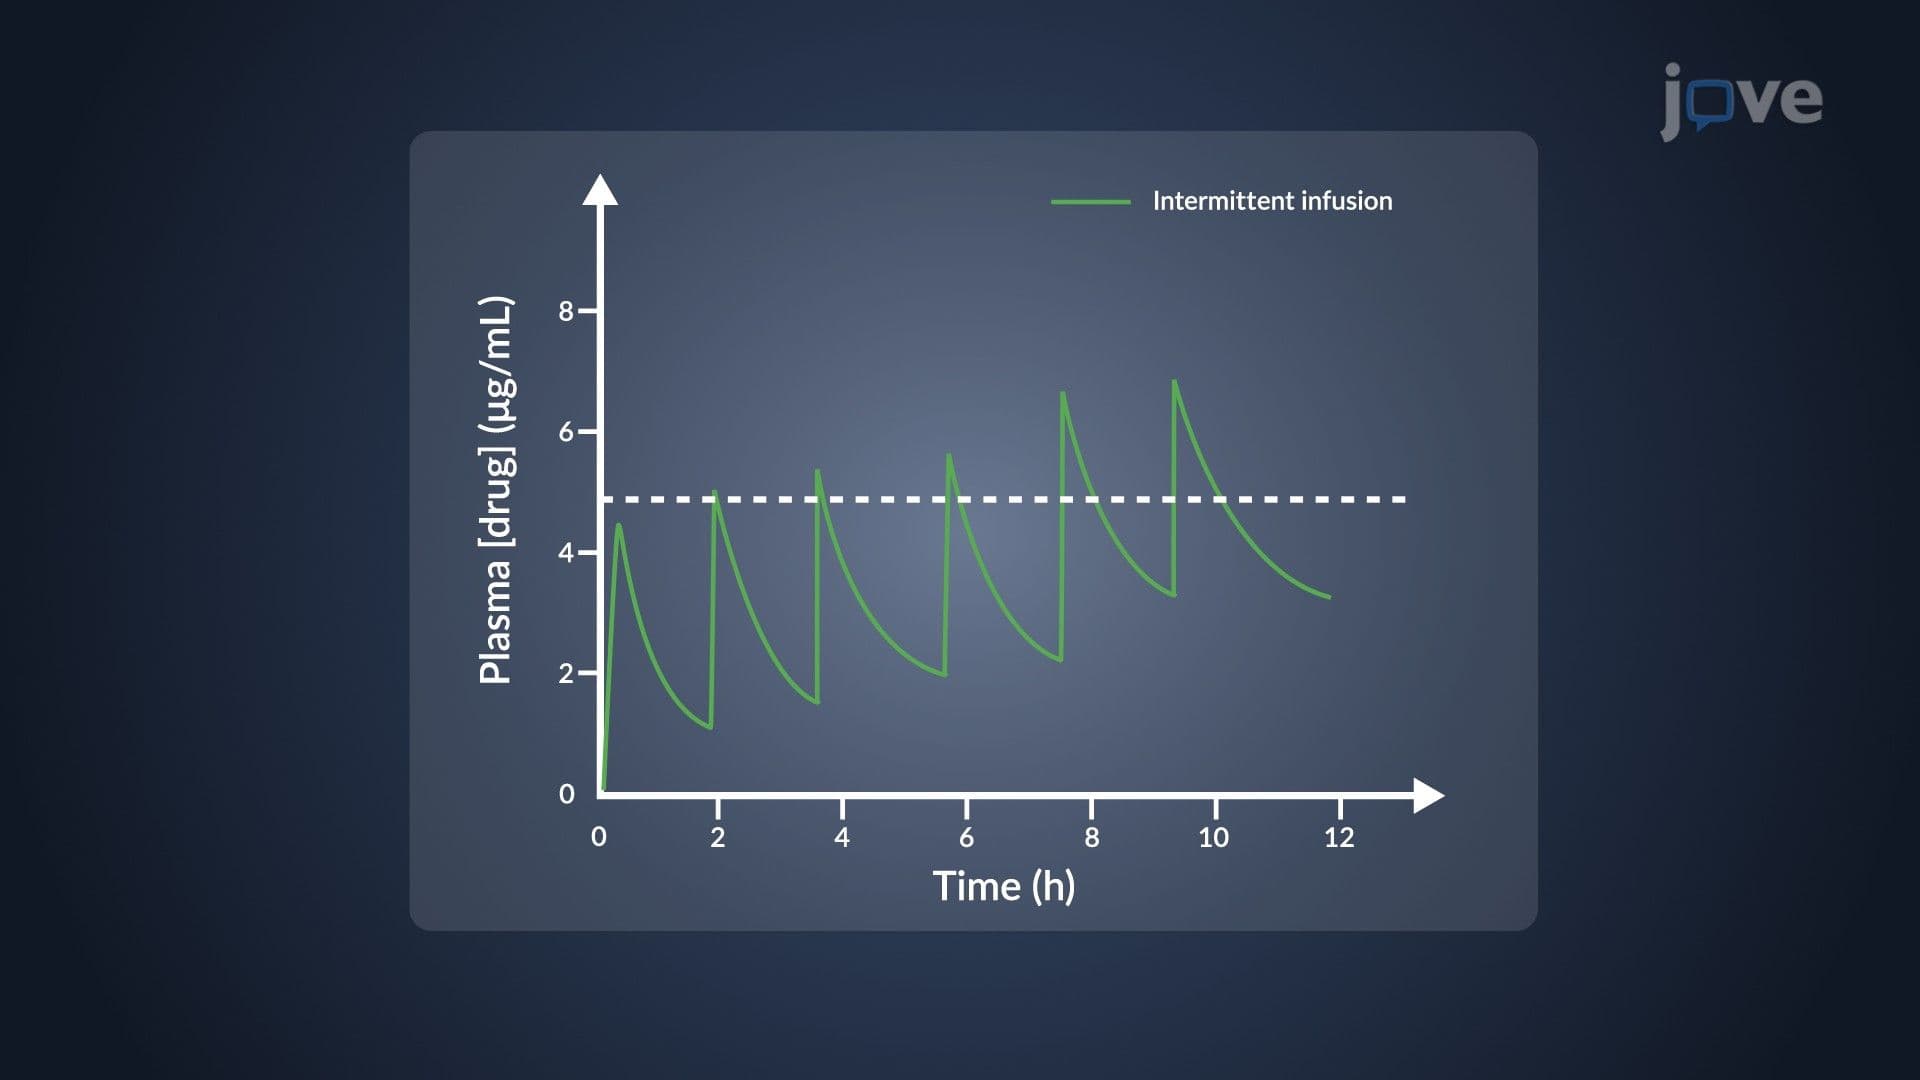
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:15
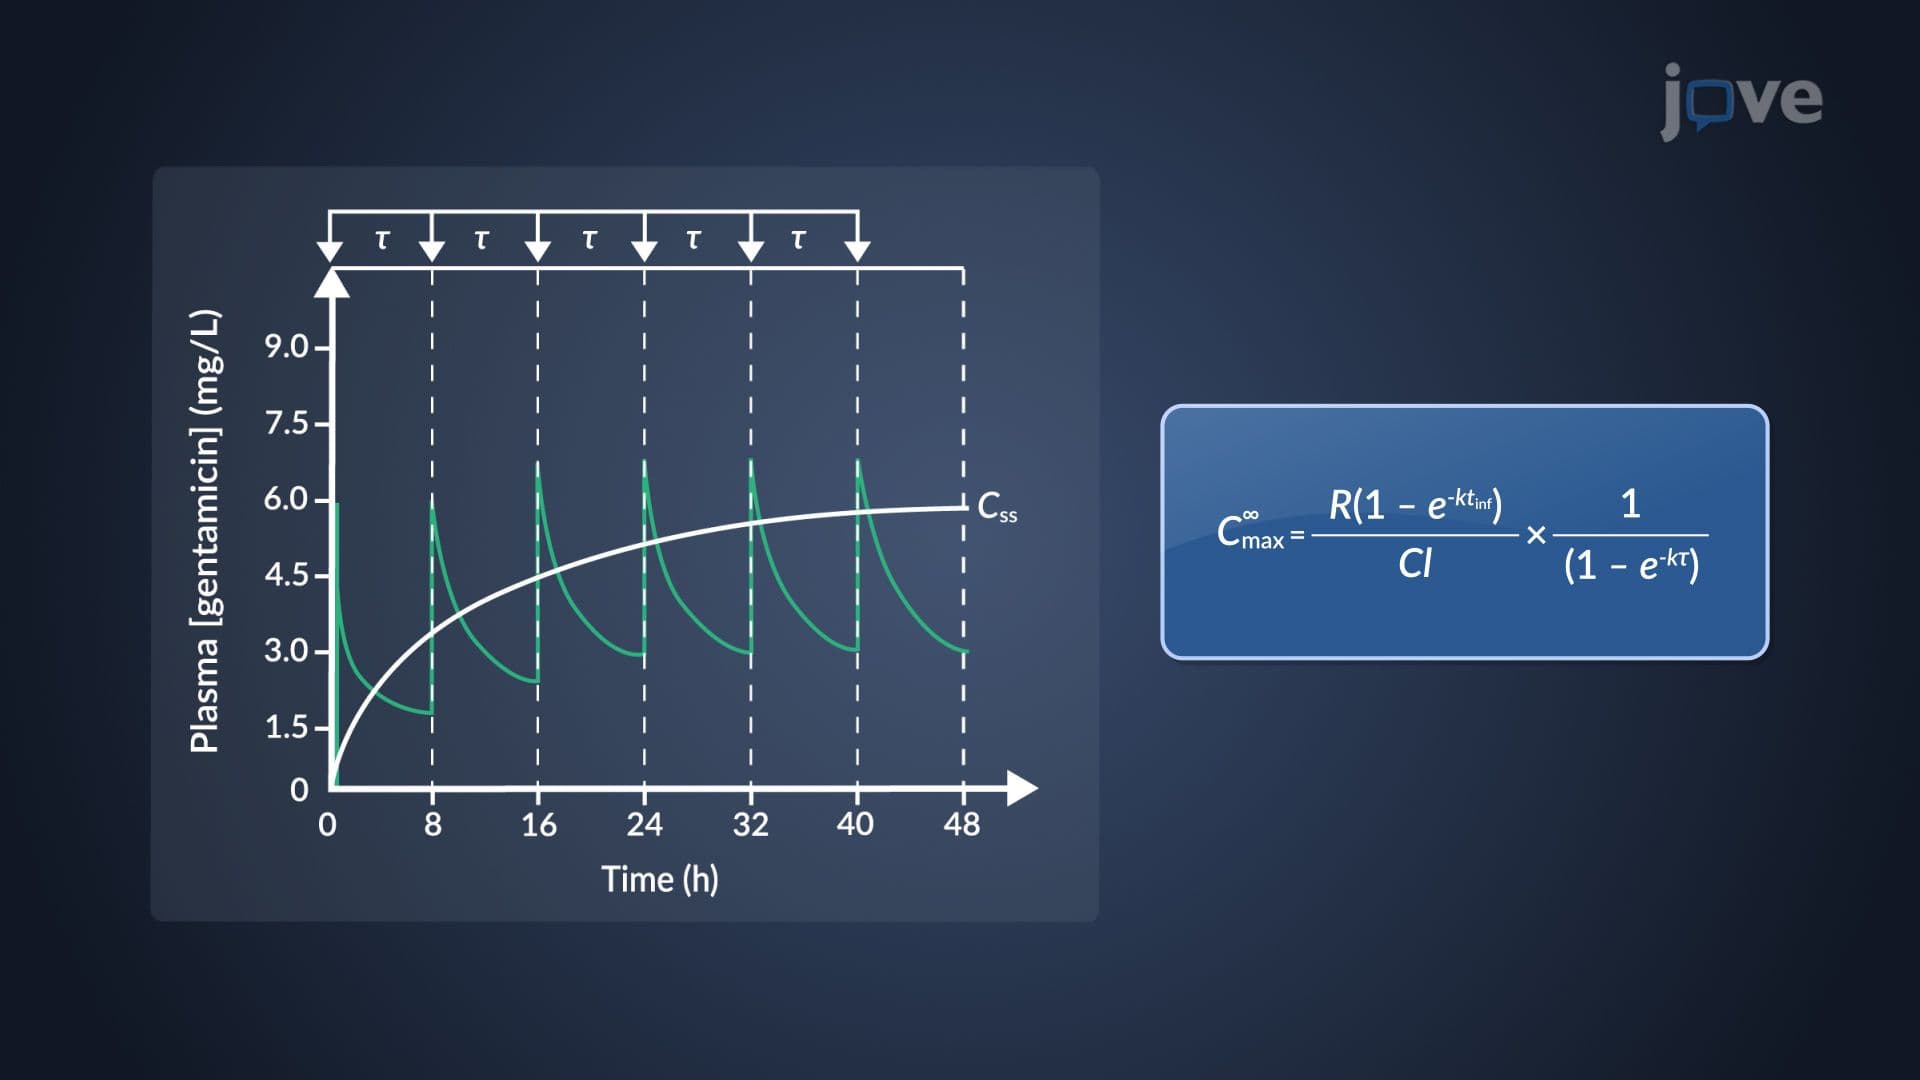
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:08
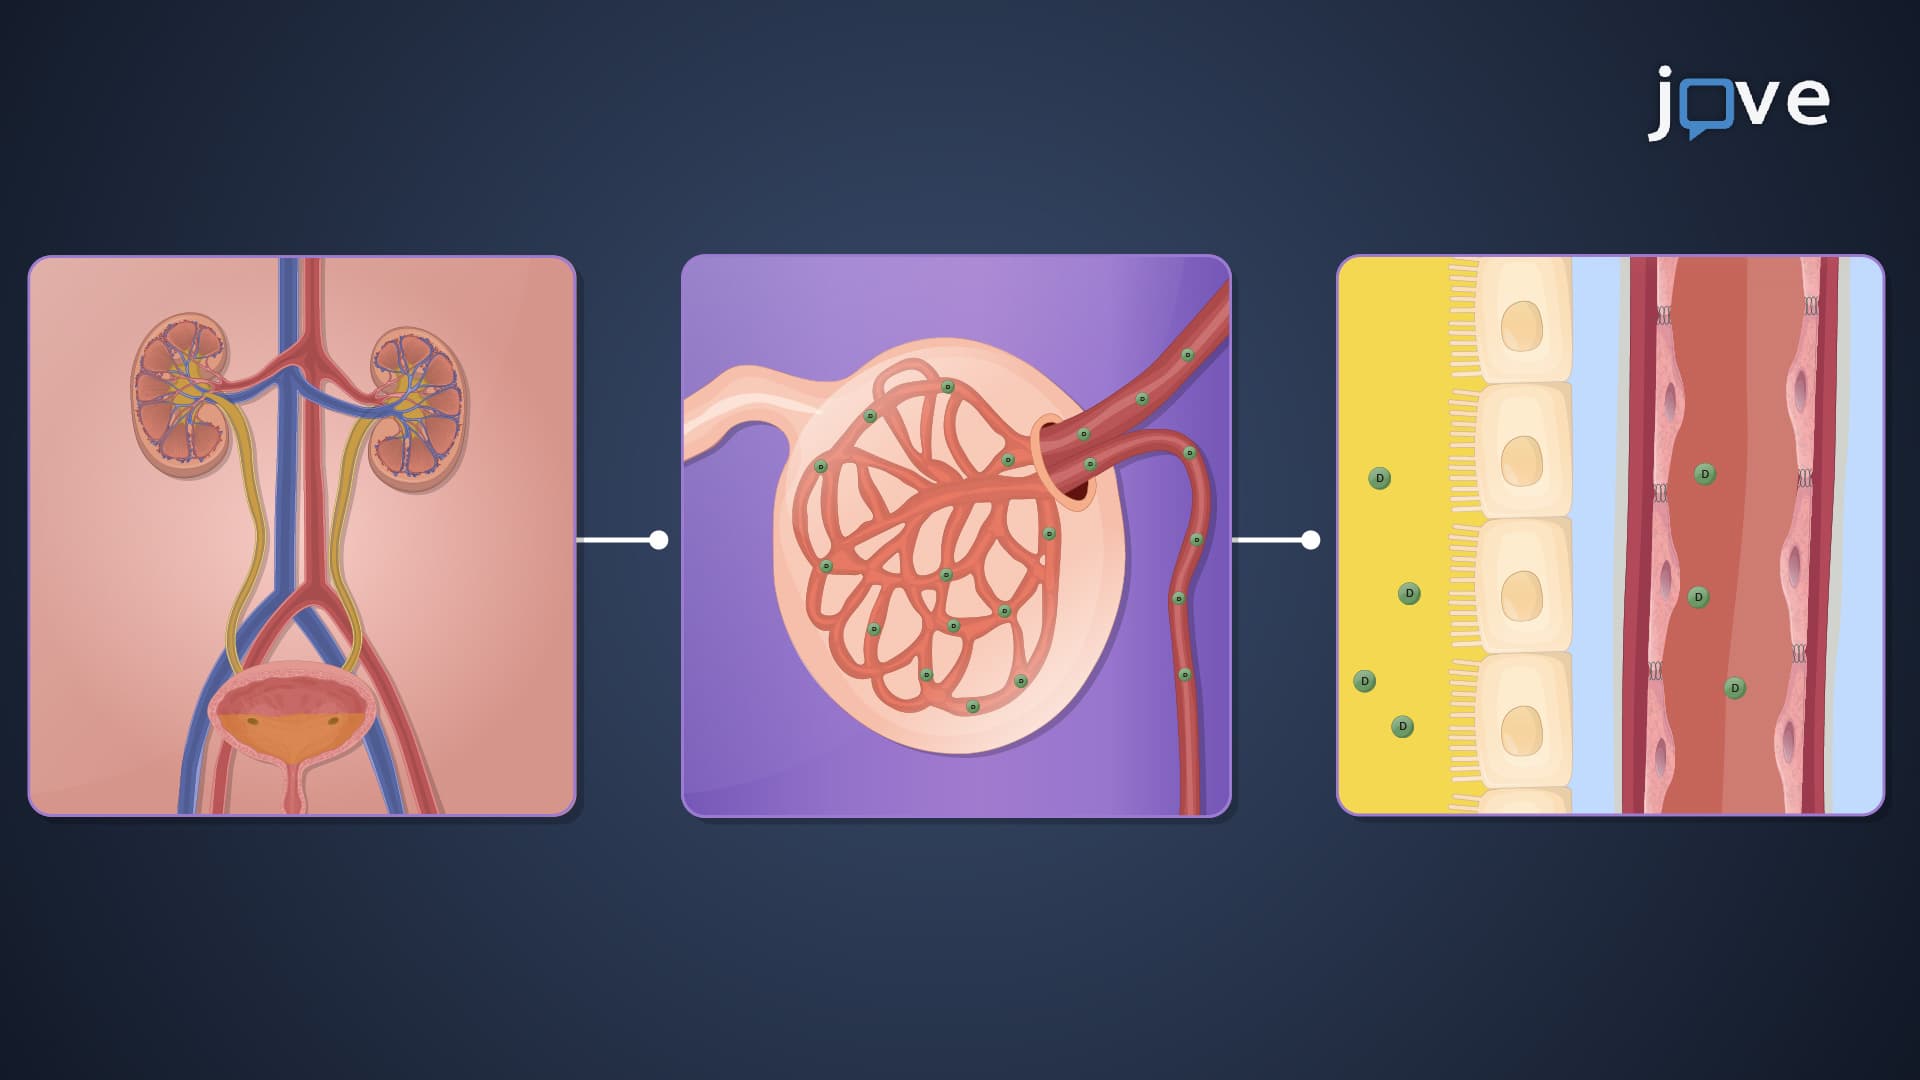
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...