Related Experiment Video
Updated: May 2, 2026
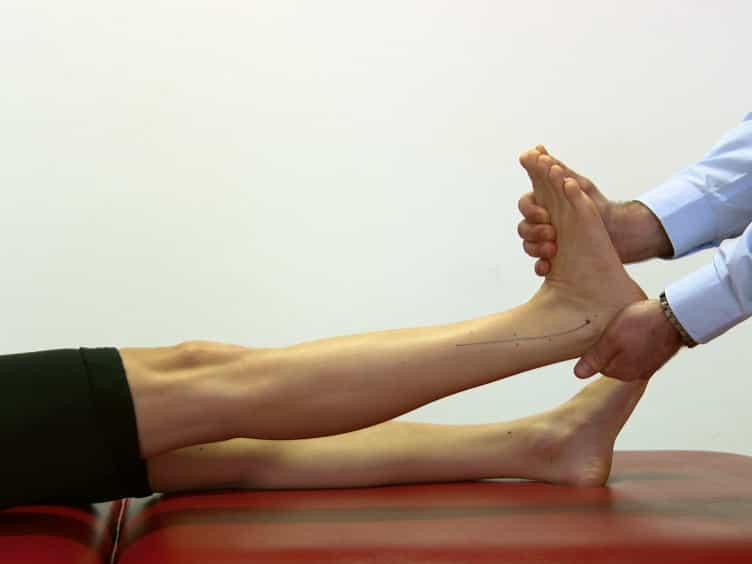

Diagnosis of Musculus Gastrocnemius Tightness - Key Factors for the Clinical Examination
Published on: July 7, 2016
What risk factors predict usage of gastrocsoleus recession during tibial lengthening?
S Robert Rozbruch1, Samuel Zonshayn, Saravanaraja Muthusamy
1Limb Lengthening and Complex Reconstruction Service, Department of Orthopaedic Surgery, Hospital for Special Surgery, Weill Cornell Medical College, Cornell University, 535 East 70th Street, New York, NY, 10021, USA, RozbruchSR@hss.edu.

Background:
Tibial lengthening is frequently associated with gastrocsoleus contracture and some patients are treated surgically. However, the risk factors associated with gastrocsoleus contracture severe enough to warrant surgery during tibial lengthening and the consistency with which gastrocsoleus recession (GSR) results in a plantigrade foot in this setting have not been well defined.
Questions/Purposes:
We compared patients treated with or without GSR during tibial lengthening with respect to (1) clinical risk factors triggering GSR use, (2) ROM gains and patient-reported outcomes, and (3) complications after GSR.
Methods:
Between 2002 and 2011, 95 patients underwent tibial lengthenings excluding those associated with bone loss; 82 (83%) were available for a minimum followup of 1 year. According to our clinical algorithm, we performed GSR when patients had equinus contractures of greater than 10° while lengthening or greater than 0° before or after lengthening. Forty-one patients underwent GSR and 41 did not. Univariate analysis was performed to assess independent associations between surgical characteristics and likelihood of undergoing GSR. A multivariate regression model and receiver operating characteristic curves were generated to adjust for confounders and to establish risk factors and any threshold for undergoing GSR. Chart review determined ROM, patient-reported outcomes, and complications.
Results:
Amount and percentage of lengthening, age, and etiology were risk factors for GSR. Patients with lengthening of greater than 42 mm (odds ratio [OR]: 4.13; 95% CI: 1.82, 9.40; p = 0.001), lengthening of greater than 13% of lengthening (OR: 3.88; 95% CI: 1.66, 9.11; p = 0.001), and congenital etiology (OR: 1.90; 95% CI: 0.86, 4.15; p = 0.109) were more likely to undergo GSR. Adjusting for all other variables, increased amount lengthened (adjusted OR: 1.05; 95% CI: 1.02, 1.07; p < 0.001) and age (adjusted OR: 1.02; 95% CI: 0.99, 1.05; p = 0.131) were associated with undergoing GSR. Patients gained 24° of ankle dorsiflexion after GSR. Self-reported functional outcomes were similar between patients with or without GSR. Complications included stretch injury to the posterior tibial nerve leading to temporary and partial loss of plantar sensation in two patients.
Conclusions:
Dorsiflexion was maintained and/or restored similarly among patients with or without GSR when treated under our algorithm. Functional compromise was not seen after GSR. Identification of patients at risk will help surgeons indicate patients for surgery. Acute dorsiflexion should be avoided to minimize risk of injury to the posterior tibial nerve.
Level Of Evidence:
Level IV, therapeutic study. See Instructions for Authors for a complete description of levels of evidence.
More Related Videos
 06:35
Using Gold-standard Gait Analysis Methods to Assess Experience Effects on Lower-limb Mechanics During Moderate High-heeled Jogging and Running
Published on: September 14, 2017
 09:01
Treatment of Ankle Osteoarthritis with Total Ankle Replacement Through a Lateral Transfibular Approach
Published on: January 24, 2018