Related Experiment Video
Updated: May 2, 2026


Treating Low Back Pain in Failed Back Surgery Patients with Multicolumn-lead Spinal Cord Stimulation
Published on: June 26, 2018

Abstract:
Why do so many patients opt for a surgical solution to lumbosacral (L-S) radicular pain? A rhetoric as well as specific question.Recently a Big Ten coach underwent the scalpel for the third time in two years. "Pain" not masochism was his response when questioned by the press, "Why the knife?"Most physicians and patients equate the severity of L-S radicular pain with the seriousness of the disc derangement.This is not so!Most physicians are aware that radicular pain is inversely proportional to the weakness associated with L-S disc herniation or extrusion. The natural history is a general remission of pain with a little exercise, perhaps some medication, and mostly Mother Nature.A sudden cessation of pain suggests a "dead" root and significant weakness. Unfortunate? Not necessarily.Electrodiagnostic studies can demonstrate a L-S radiculopathy within two weeks of onset and after one week can differentiate neurapraxic (reversible) weakness from permanent weakness.In both instances surgery is not the treatment of choice. In the first instance a conduction block at this inflamed nerve root is the problem and in the second scenario the weakness is generally not reversible with surgery (in fact the operation could be blamed).Nonradicular back pain needs a physiatric evaluation and management program.Patients should be reassured in all situations that most people "get over" acute back pain (including radicular) with minimal residuals if they are patient and educable!After all, rehabilitation is essentially teaching and patient learning. All patients with low back pain need thorough grounding in anatomy and physiology of the low back and biomechanics of lifting, in order to fend off advice of well-meaning friends, relatives, or even other "health" professionals.A recent study announced 10 times more lumbar laminectomies are done in the United States than in Europe. To reduce this number, I suggest all second opinions for this major (e.g., Discectomy) lumbar assault be given by a nonsurgeon who understands back problems (i.e., a physiatrist).Isn't this essentially the same as a gastroenterologist presenting a second opinion for management of a gastric ulcer-medical versus surgical?A physiatrist would provide a second opinion instead of a seconding opinion.
More Related Videos
 06:28
Biomechanical Changes Related to Low Back Pain: An Innovative Tool for Movement Pattern Assessment and Treatment Evaluation in Rehabilitation
Published on: December 13, 2024
 05:10
Back Mechanical Sensitivity Assessment in the Rat for Mechanistic Investigation of Chronic Back Pain
Published on: August 30, 2022
Related Concept Videos
 01:29
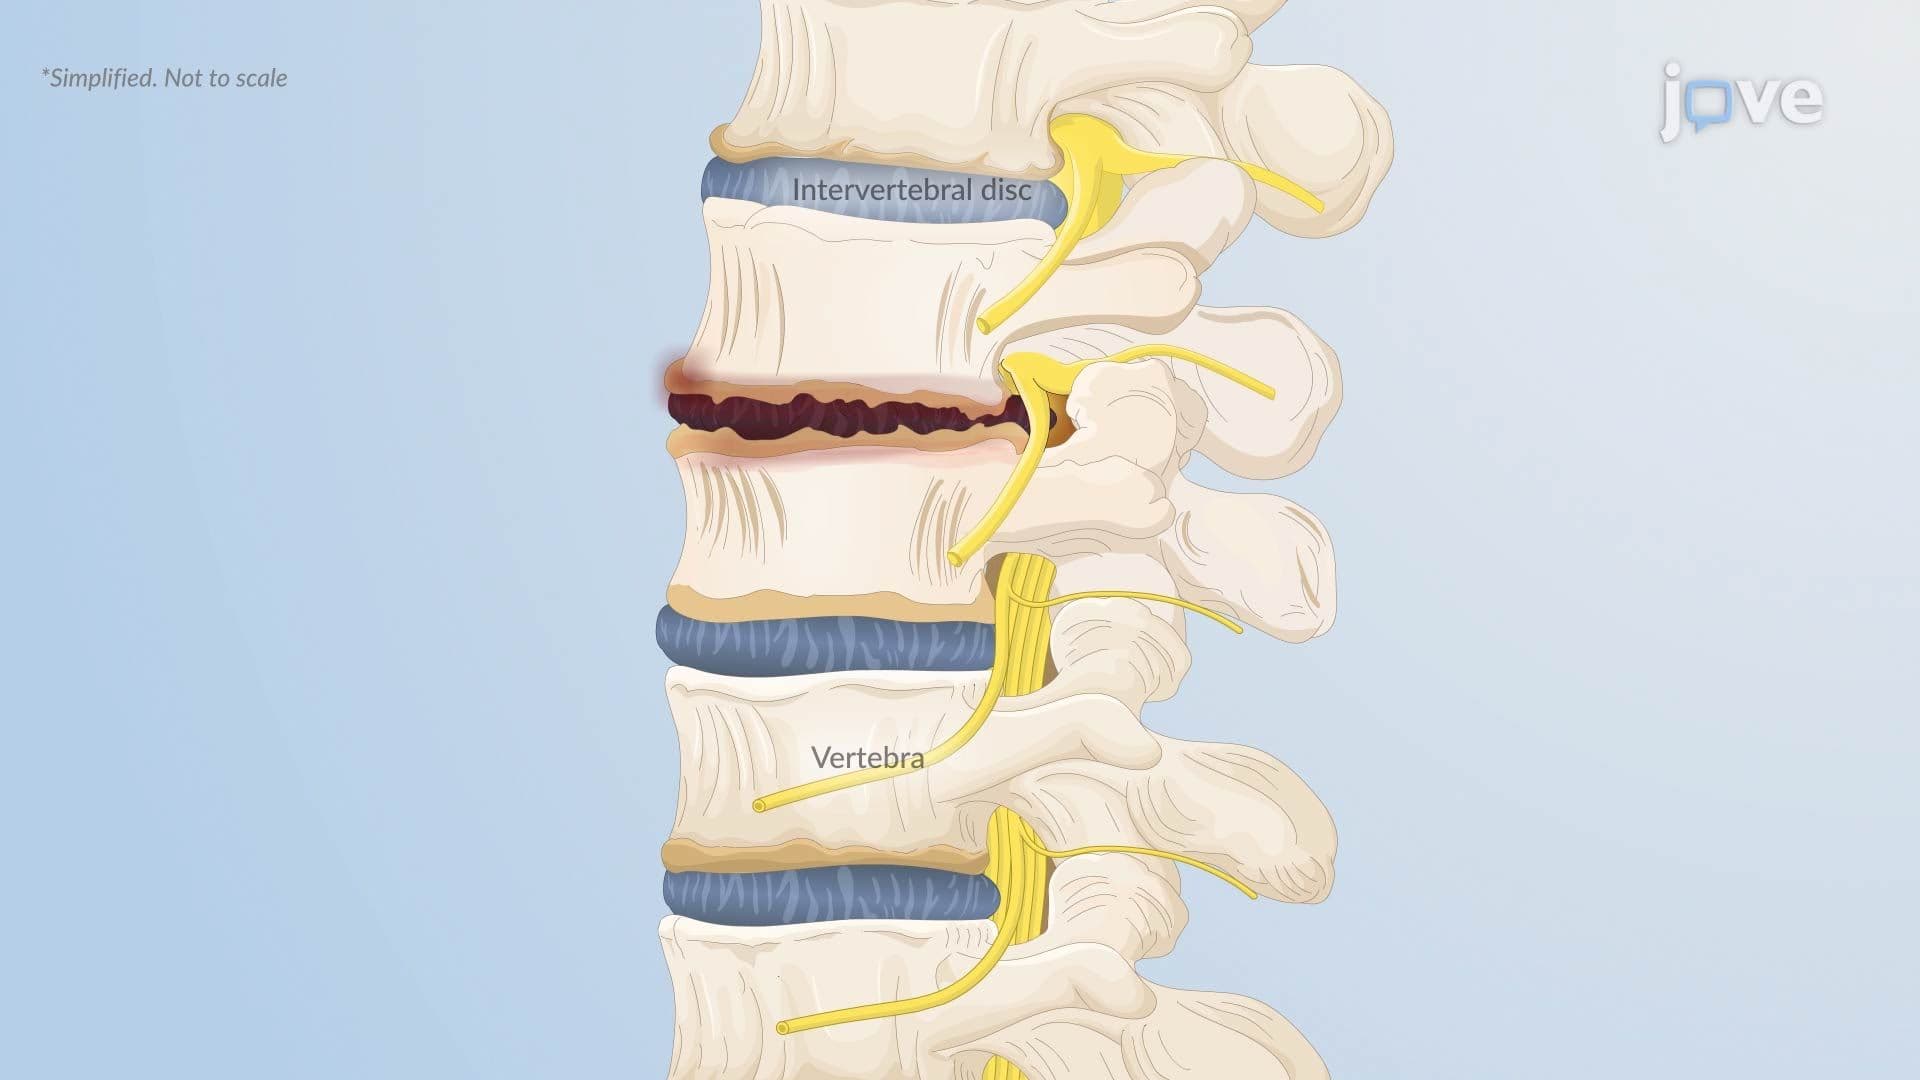
Herniated Intervertebral Disc l: Introduction
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...
 01:27
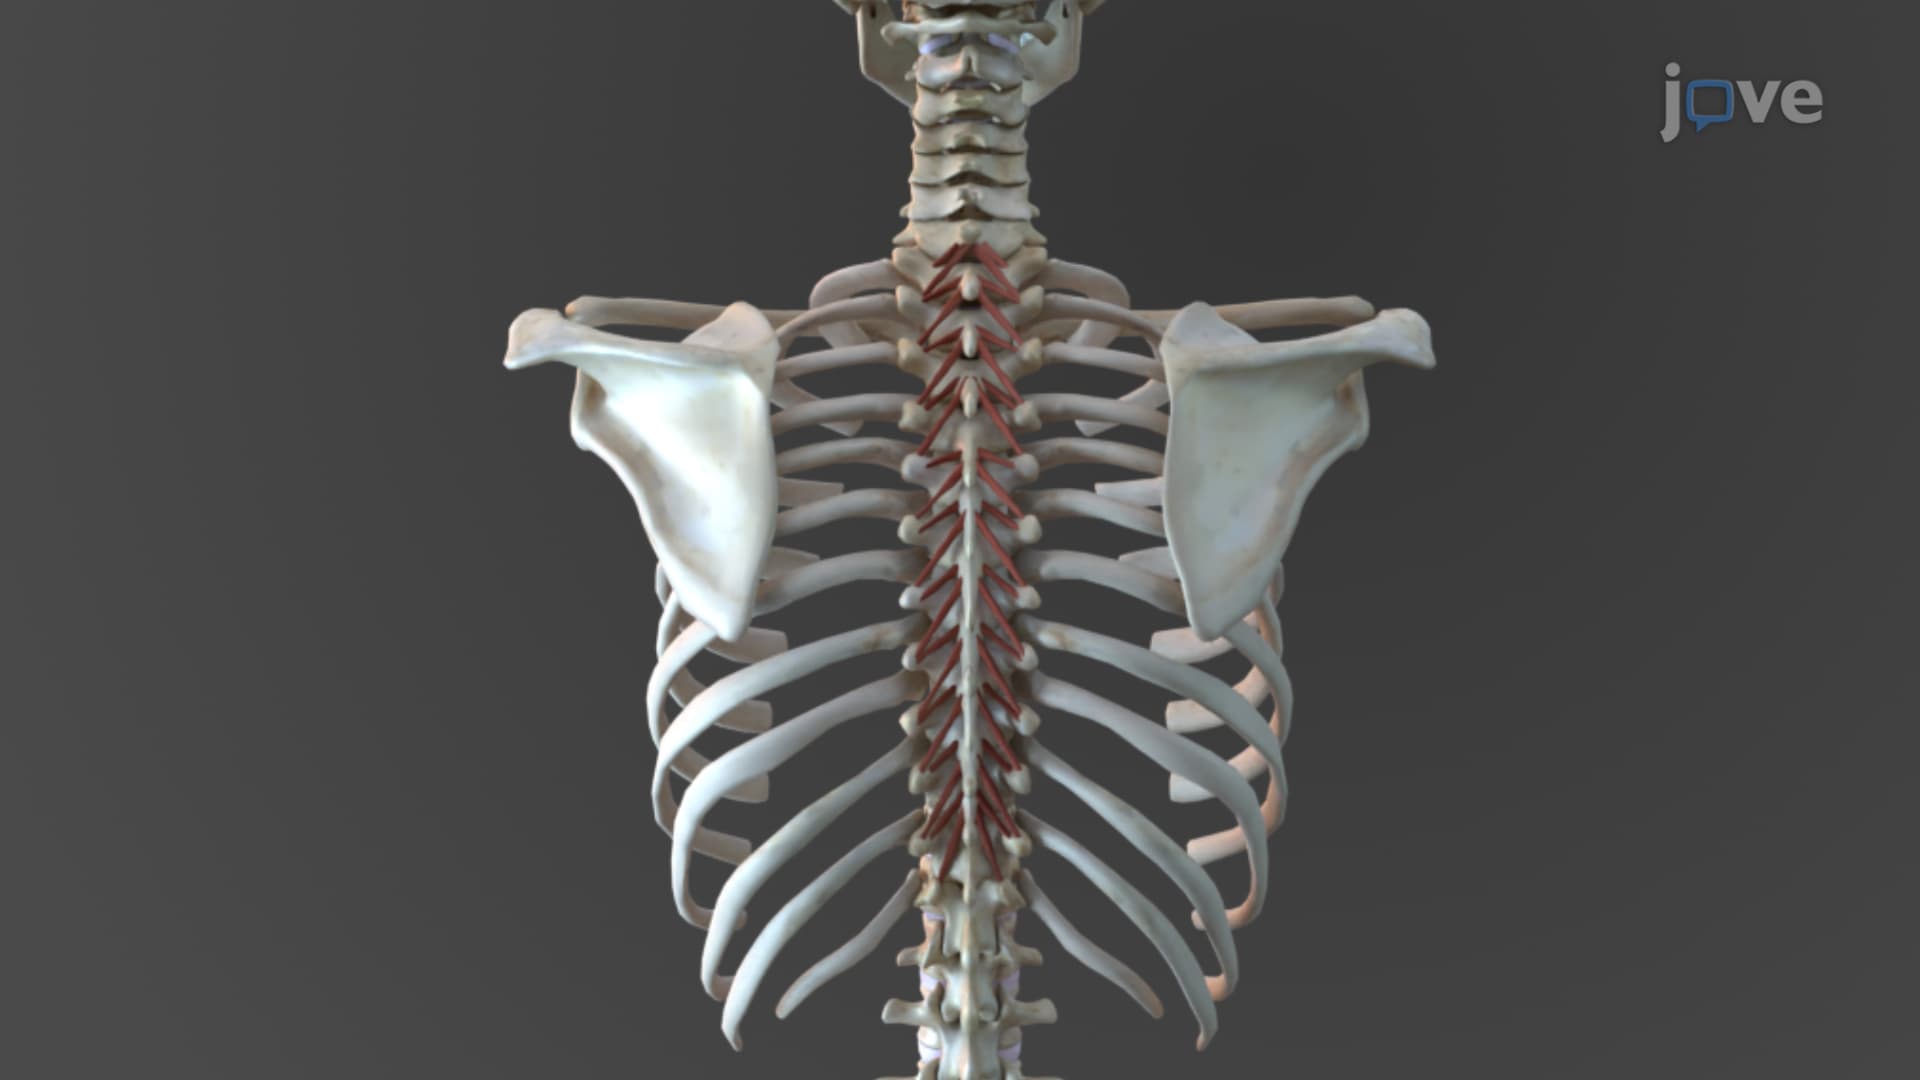
Muscles of the Vertebral Column
Superficial Layer:
The superficial layer consists primarily of the splenius muscles, which include the splenius capitis and splenius cervicis. These muscles are mainly responsible for the head and cervical spine movements, including extension, rotation, and lateral bending. The splenius capitis...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:26
Nursing Assessment of the Genitourinary System II: Inspection and Palpation