Related Experiment Video
Updated: May 2, 2026

Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Potential causes of loss of reduction in supracondylar humerus fractures
Andrew T Pennock1, Michael Charles, Molly Moor
1*Rady Children's Hospital †Department of Orthopedic Surgery, University of California, San Diego, CA.

Background:
Recent biomechanical studies have evaluated the stability of various pin constructs for supracondylar humerus fractures, but limited data exist evaluating these constructs with clinical outcomes. The goal of this study was to review the surgical management of Gartland type II and III supracondylar fractures to see whether certain pin configurations increase the likelihood of loss of reduction (LOR).
Methods:
A total of 192 patients treated with a displaced supracondylar fracture were evaluated. LOR was defined as a change >10 degrees in either plane from its intraoperative reduction. Fracture classification, comminution, and location were documented. Intraoperative films were assessed for number of pins, location of pins both medial and lateral, bicortical purchase, pin spread at the fracture site, and pin divergence.
Results:
Ninety-four patients had type II fractures, and 98 had type III fractures. The average patient age was 5.7±2.3 years. Extension-type injuries represented 98% of fractures. LOR was noted in 4.2% of patients. Age (P=0.48) and sex (P=0.61) were not associated with LOR. Fracture characteristics including type (P=0.85), comminution (P=0.99), and location (P=0.88) were not associated with LOR. Fractures treated with lateral-entry pins only or with 2 pins were no more likely to lose reduction (P=0.88 and 0.91). Pin spread at the fracture site was associated with LOR with less spread increasing the likelihood of failure (P=0.02). Fractures that lost reduction had an average pin spread of 9.7 mm [95% confidence interval (CI), 6.3-13.2) or 28% (95% CI, 26-31) of the humerus width compared with 13.7 mm (95% CI, 13-14.4) or 36% (95% CI, 13-60) of the humerus width for those that remained aligned.
Conclusions:
LOR after percutaneous fixation of supracondylar fractures occurs relatively infrequently at a rate of 4.2%. This study suggests that pin spread is an important factor associated with preventing LOR with a goal of pin spacing at least 13 mm or 1/3 the width of the humerus at the level of the fracture.
Level Of Evidence:
Retrospective study; level II.
More Related Videos
 11:21
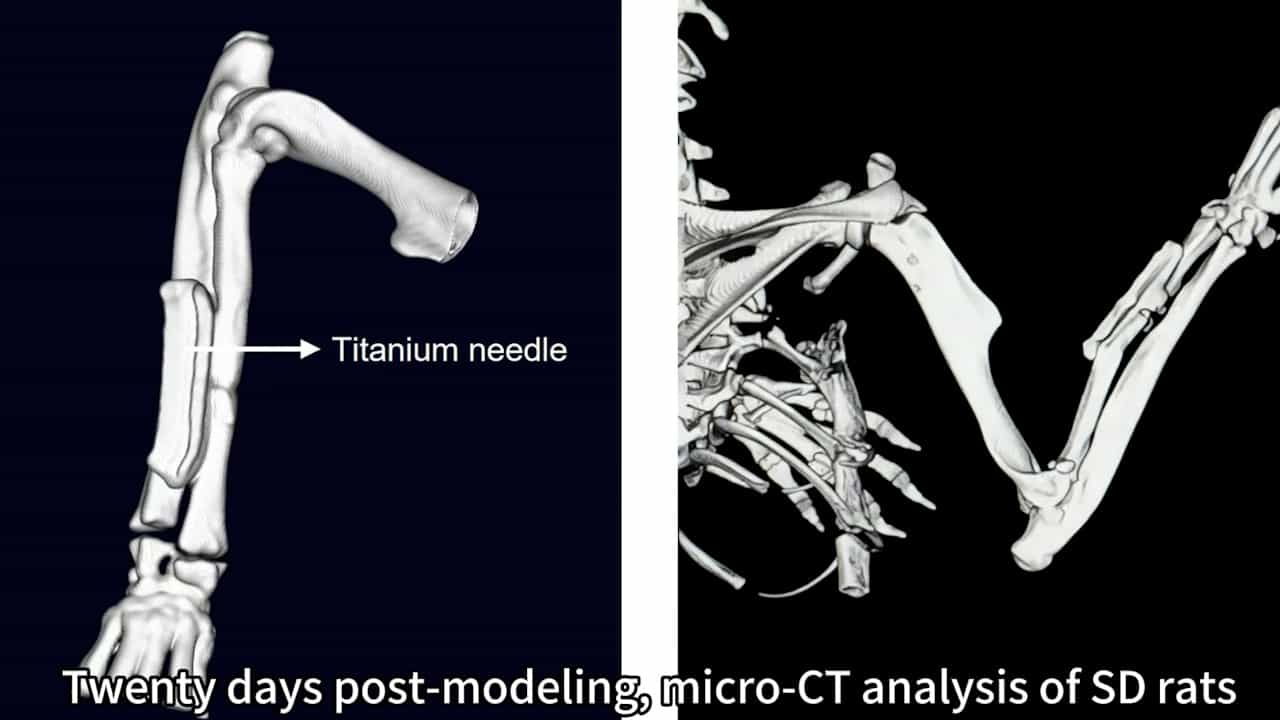
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
 04:41
Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:19
Bones of the Upper Limb: Humerus
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:16
Bones of the Lower Limb: Femur and Patella
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...