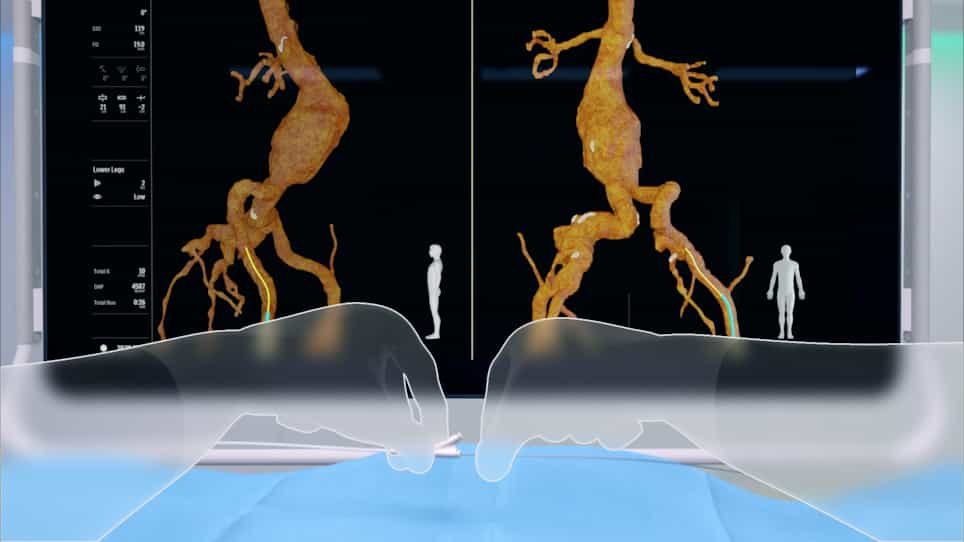
In endovascular aneurysm repair cases, when should you consider internal iliac artery embolization when extending a
George N Kouvelos1, Andreas Koutsoumpelis1, Michalis Peroulis1
1Department of Surgery, Vascular Surgery Unit, Medical School, University of Ioannina, Ioannina, Greece.

Insights
Internal iliac artery (IIA) embolization is not routinely necessary during endovascular aneurysm repair (EVAR) when stent graft extension to the external iliac artery is needed. Evidence suggests it may increase risks like buttock claudication without clear benefit for most patients.
Area of Science:
- Vascular Surgery
- Interventional Radiology
- Medical Device Technology
Background:
- Endovascular aneurysm repair (EVAR) is a common treatment for abdominal aortic aneurysms.
- Extension of stent grafts to the external iliac artery is sometimes required.
- The role of internal iliac artery (IIA) embolization in these cases is debated.
Purpose of the Study:
- To determine if internal iliac artery (IIA) embolization is necessary for optimal outcomes in EVAR patients requiring external iliac artery stent graft extension.
- To identify specific patient subsets that might benefit from IIA embolization.
Main Methods:
- A best evidence topic was constructed.
- A systematic literature search identified over 400 papers.
- Five papers representing the best evidence were selected and analyzed.
Main Results:
- Current literature shows a gap in clearly defined indications for IIA embolization during EVAR.
- For most patients needing external iliac artery extension, IIA embolization is associated with worse clinical outcomes, including buttock claudication.
- IIA coverage by the stent graft alone did not significantly increase type II endoleak rates.
Conclusions:
- Routine IIA embolization is not indicated for all EVAR patients requiring external iliac artery extension.
- IIA embolization may benefit a small subset of patients by preventing endoleaks.
- Further research is needed, but current evidence suggests avoiding routine embolization to minimize risks and procedural burden.
Abstract:
A best evidence topic was constructed according to a structured protocol. The question addressed was whether internal iliac artery (IIA) embolization is necessary for achieving the best clinical outcome in all patients when extension of the stent graft to the external iliac artery is required. Altogether more than 400 papers were found using the reported search, of which 5 represented the best evidence to answer the clinical question. The authors, journal, date and country of publication, patient group studied, study type, relevant outcomes and results of these papers are tabulated. There is a significant gap in the current literature regarding the subset of patients that may benefit from an IIA embolization during endovascular aneurysm repair (EVAR) as indications have not been clearly defined. There are several situations concerning a small number of patients, that IIA embolization might be beneficial in preventing endoleak not only to the common iliac artery but also to the aortic aneurysmal sac. For the majority of patients requiring extension of the stent graft to the external iliac artery, the current evidence, even retrospective in nature and reporting on small numbers of patients, shows that IIA embolization seems to be associated with worse clinical outcome, mostly raising the risk for new-onset buttock claudication. It seems that not all patients require embolization, as IIA coverage solely by the stent graft was not associated with a significant higher rate of type II endoleak in either study. Furthermore, coil embolization in the largest study so far was associated with higher procedure and fluoroscopy time and amount of contrast media, facts that should not be neglected. However the above-mentioned results should be taken into account with caution, as all studies were retrospective and reported on small number of patients.


Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management
 01:25
Abdominal Aorta
The celiac trunk, a singular artery, divides into the left gastric artery, which...