Related Experiment Video
Updated: May 2, 2026

A Magnetic Resonance Imaging Protocol for Stroke Onset Time Estimation in Permanent Cerebral Ischemia
Published on: September 16, 2017
Diffusion-weighted imaging volume as the best predictor of the diffusion-perfusion mismatch in acute stroke patients
Junya Aoki1, Yohei Tateishi1, Christopher L Cummings1
1Cerebrovascular Center, Neurological Institute, Cleveland Clinic, Ohio.

Background:
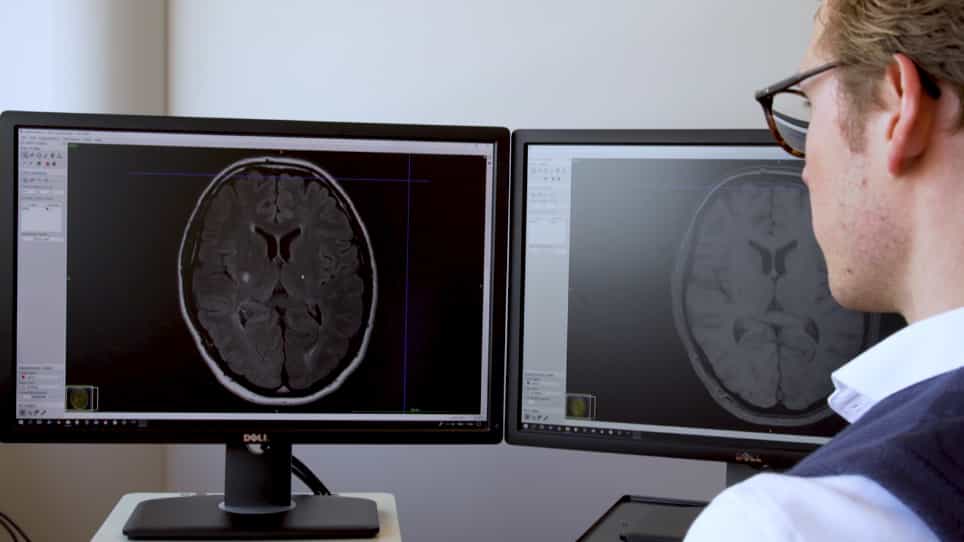
Diagnostic accuracies of standard NCCT, CTA, CTA-SI, FLAIR, and DWI to detect the diffusion-perfusion mismatch (DPM) were compared.
Methods:
Stroke patients considered for endovascular therapy within 8 hours of onset were enrolled. DPM was defined as at least 160% mismatch between DWI and PWI volume.
Results:
DPM was seen in 35 (71%) of 49 patients. ASPECTS on NCCT, CTA-SI, and DWI was 9 (8-9), 8 (6-9), and 7 (5-9) in mismatch group, and 6 (4-9), 6 (2-7), 5 (2-6) in nonmismatch group, respectively (P = .027, .006, and .001). Ischemic volume on CTA-SI and DWI was 4.6 (.2-13.0) cm(3) and 21.5 (9.7-44.0) cm(3) in mismatch group, and 61.5 (6.6-101.1) cm(3) and 94.9 (45.7-139.8) cm(3) in nonmismatch group (P = .003 and <.001). Significant collateralization on CTA-SI and FLAIR was seen in 80% and 88% in mismatch group, and 42% and 58% in nonmismatch group (P = .026 and .039). Odds ratios (95% CI) of DWI volume of ≤ 70 cm(3) to predict the mismatch was 30.17 (2.06-442.41) after adjusting for ASPECTSs on NCCT, CTA-SI, and DWI, 44.90 (2.75-732.73) for ischemic volume on CTA-SI, and 42.80 (3.05-601.41) for significant collateralization on CTA-SI and FLAIR (P = .013, .008, and .005).
Conclusions:
DWI volume was the best predictor of DPM.
Insights
Diffusion-weighted imaging (DWI) volume is the best predictor of diffusion-perfusion mismatch (DPM) in stroke patients. This finding aids in identifying candidates for endovascular therapy.
Area of Science:
- Neuroimaging
- Stroke Imaging
- Cerebrovascular Diseases
Background:
- Standard non-contrast computed tomography (NCCT), computed tomography angiography (CTA), CTA-Sl, fluid-attenuated inversion recovery (FLAIR), and diffusion-weighted imaging (DWI) were evaluated for their accuracy in detecting diffusion-perfusion mismatch (DPM).
- DPM is a critical indicator for identifying stroke patients who may benefit from endovascular therapy.
Purpose of the Study:
- To compare the diagnostic accuracies of various neuroimaging techniques in detecting DPM.
- To identify the most effective imaging parameter for predicting DPM in acute stroke patients.
Main Methods:
- Stroke patients eligible for endovascular therapy within 8 hours of symptom onset were enrolled.
- Diffusion-perfusion mismatch (DPM) was defined as a mismatch of at least 160% between DWI and perfusion-weighted imaging (PWI) volumes.
- Analysis included ASPECTS scores, ischemic volumes, and collateral status on NCCT, CTA, CTA-SI, FLAIR, and DWI.
Main Results:
- DPM was identified in 71% of the 49 patients studied.
- ASPECTS scores and ischemic volumes were significantly lower in the mismatch group compared to the non-mismatch group across multiple imaging modalities (P < .05).
- Significant collateralization was more prevalent in the mismatch group (80% CTA-SI, 88% FLAIR) compared to the non-mismatch group (42% CTA-SI, 58% FLAIR) (P < .05).
- Diffusion-weighted imaging (DWI) volume of ≤ 70 cm³ was a strong independent predictor of DPM (Odds Ratios ranging from 30.17 to 44.90, P < .05).
Conclusions:
- Diffusion-weighted imaging (DWI) volume emerged as the most significant predictor of diffusion-perfusion mismatch (DPM).
- These findings underscore the importance of DWI in assessing DPM and guiding treatment decisions for acute ischemic stroke.