Related Experiment Video
Updated: May 2, 2026


Generation of a Mouse Spontaneous Autoimmune Thyroiditis Model
Published on: March 17, 2023
Idiopathic and mild subclinical hypothyroidism in childhood: clinical management
F De Luca1, D Corica, E Pitrolo
1Department of Pediatrics, University of Messina, Messina, Italy - filippo.deluca@unime.it.

Insights
Subclinical hypothyroidism (SH) in children without underlying conditions typically does not impact growth or development. Levothyroxine (L-T4) treatment is generally not recommended for mild SH (TSH 5-10 mIU/L) in pediatric patients.
Area of Science:
- Pediatric Endocrinology
- Thyroid Disorders
- Clinical Management
Background:
- Subclinical hypothyroidism (SH) is a frequent clinical issue in pediatric populations.
- Management and natural progression of SH present numerous controversies.
- Idiopathic SH in children requires careful evaluation due to these uncertainties.
Purpose of the Study:
- To review the current understanding of idiopathic subclinical hypothyroidism in pediatric patients.
- To address controversial aspects of SH natural history and treatment in children.
- To synthesize evidence on the effects of mild TSH elevation in the pediatric population.
Main Methods:
- Systematic review of full-length articles focusing on natural history and treatment of SH in children.
- Inclusion criteria specified no associated diseases or genetic syndromes.
- Analysis of 13 selected papers providing retrospective or longitudinal data.
Main Results:
- Mild TSH elevation (5-10 mIU/L) in SH children without underlying disease did not affect growth, bone maturation, BMI, or cognitive function.
- The risk of thyroid function deterioration in untreated mild idiopathic SH is approximately 12%.
- Progression is more likely with higher baseline TSH, goiter, or positive anti-thyroid antibodies.
Conclusions:
- Levothyroxine (L-T4) treatment is not indicated for SH with TSH levels consistently between 5-10 mIU/L after excluding underlying conditions.
- Treatment is advised for SH cases with TSH >10 mIU/L or when an underlying disease is present.
- Current evidence suggests a conservative approach for mild, idiopathic SH in children, reserving L-T4 for more severe or complicated cases.
Abstract:
Subclinical hypothyroidism (SH) is a common clinical problem in children and adolescents, for which there are many controversial issues regarding natural course and management. Aim of this review is to report on the state of the art regarding these controversial points of idiopathic SH in pediatric age. We included in our search only full-length articles on natural history and treatment of SH in children with no associated diseases or genetic syndromes, thus identifying only 13 papers that were suitable for our analysis. According to the results of these retrospective or longitudinal studies a persistently mild TSH elevation (between 5 and 10 mIU/L) in SH children with no underlying disease is unable to affect growth and bone maturation or body mass index (two studies) or cognitive function (one study). Moreover, the risk of a deterioration over time of thyroid function in the untreated cases with mild and idiophatic SH is only 12% (one study). Progression odds increase with increasing baseline TSH, with goiter presence and with positive anti-thyroid antibodies (two studies in children). Although no broad consensus exists on whether children with mild SH require L-T4 therapy, nevertheless, on the basis of the results of the majority of included studies, it can be concluded that L-T4 treatment is not indicated when TSH is repeatedly between 5 and 10 mIU/L and an underlying disease has been excluded. By contrast, treatment is suitable in the cases with TSH>10 mIU/L and/or an underlying disease.

Related Concept Videos
 01:23
Hypothyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:28
Graves' Disease I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology
 01:20
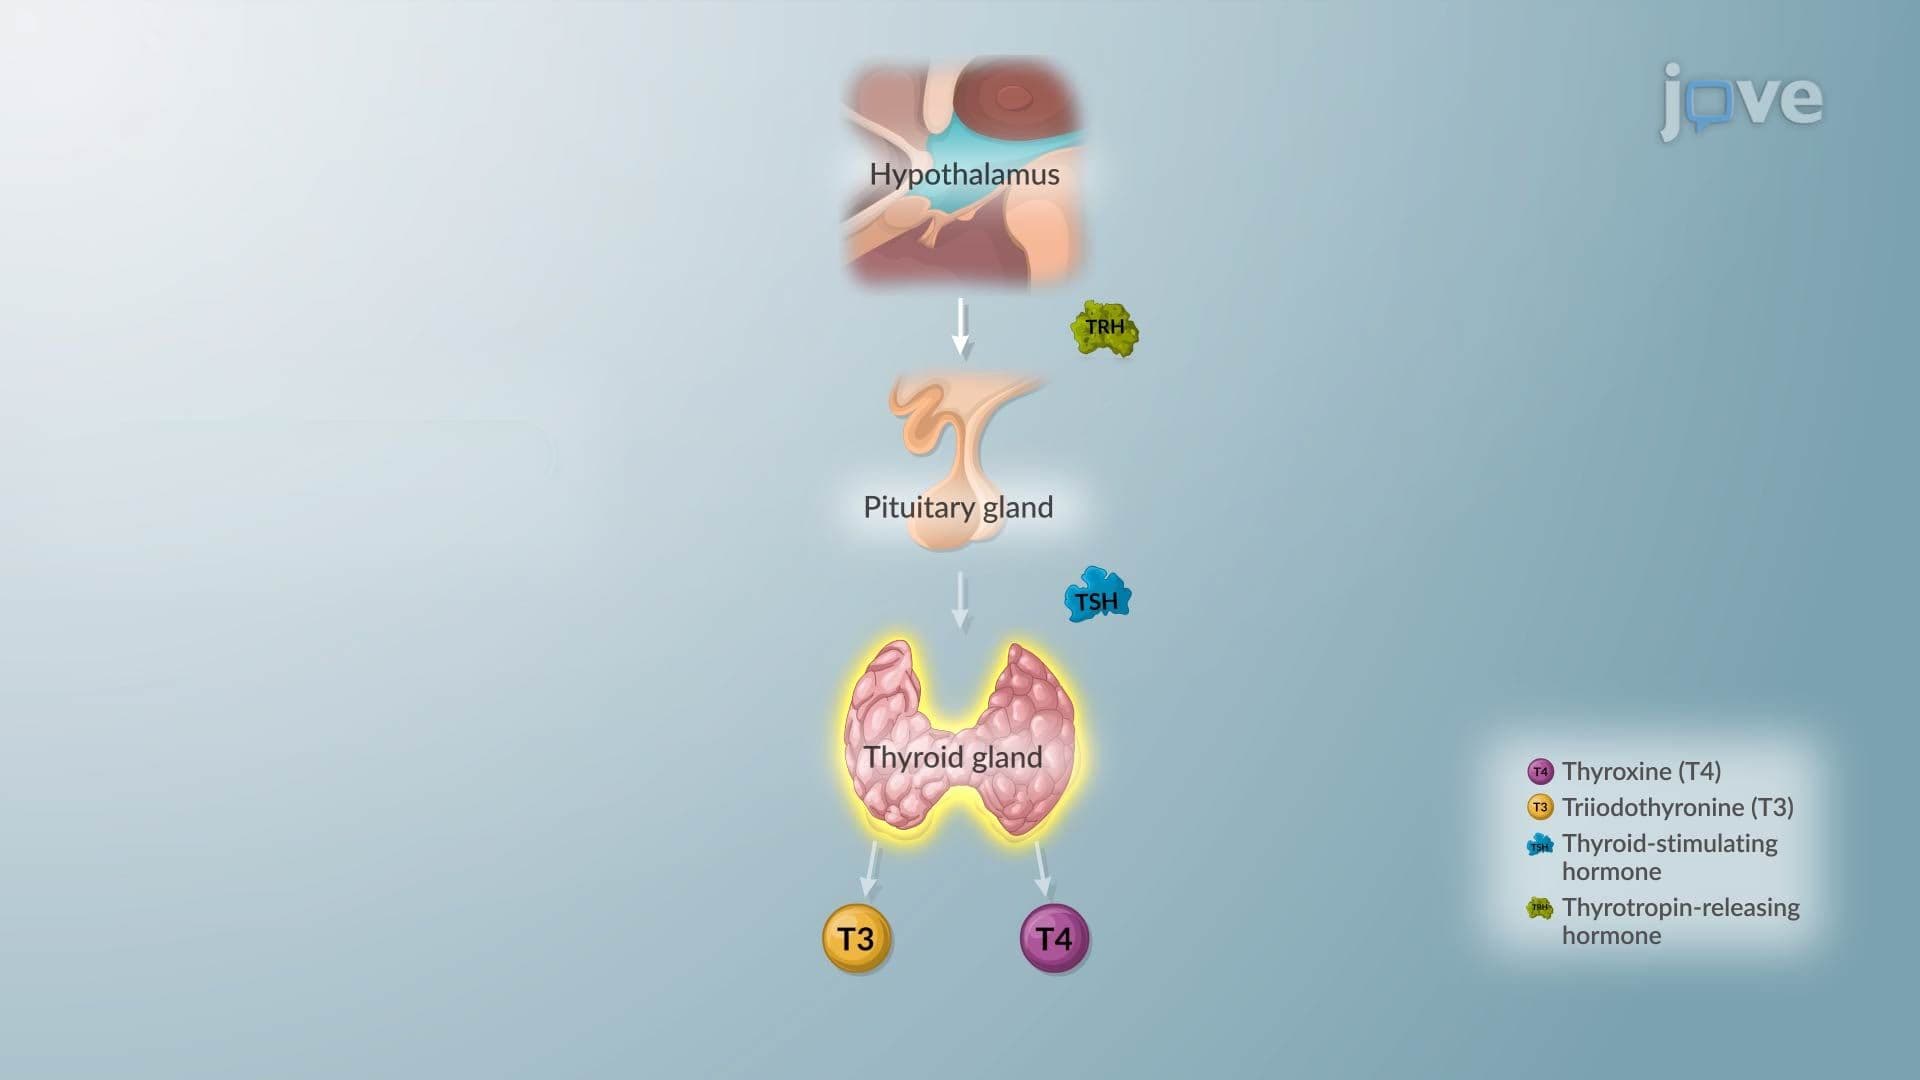
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The...