Related Experiment Video
Updated: May 2, 2026
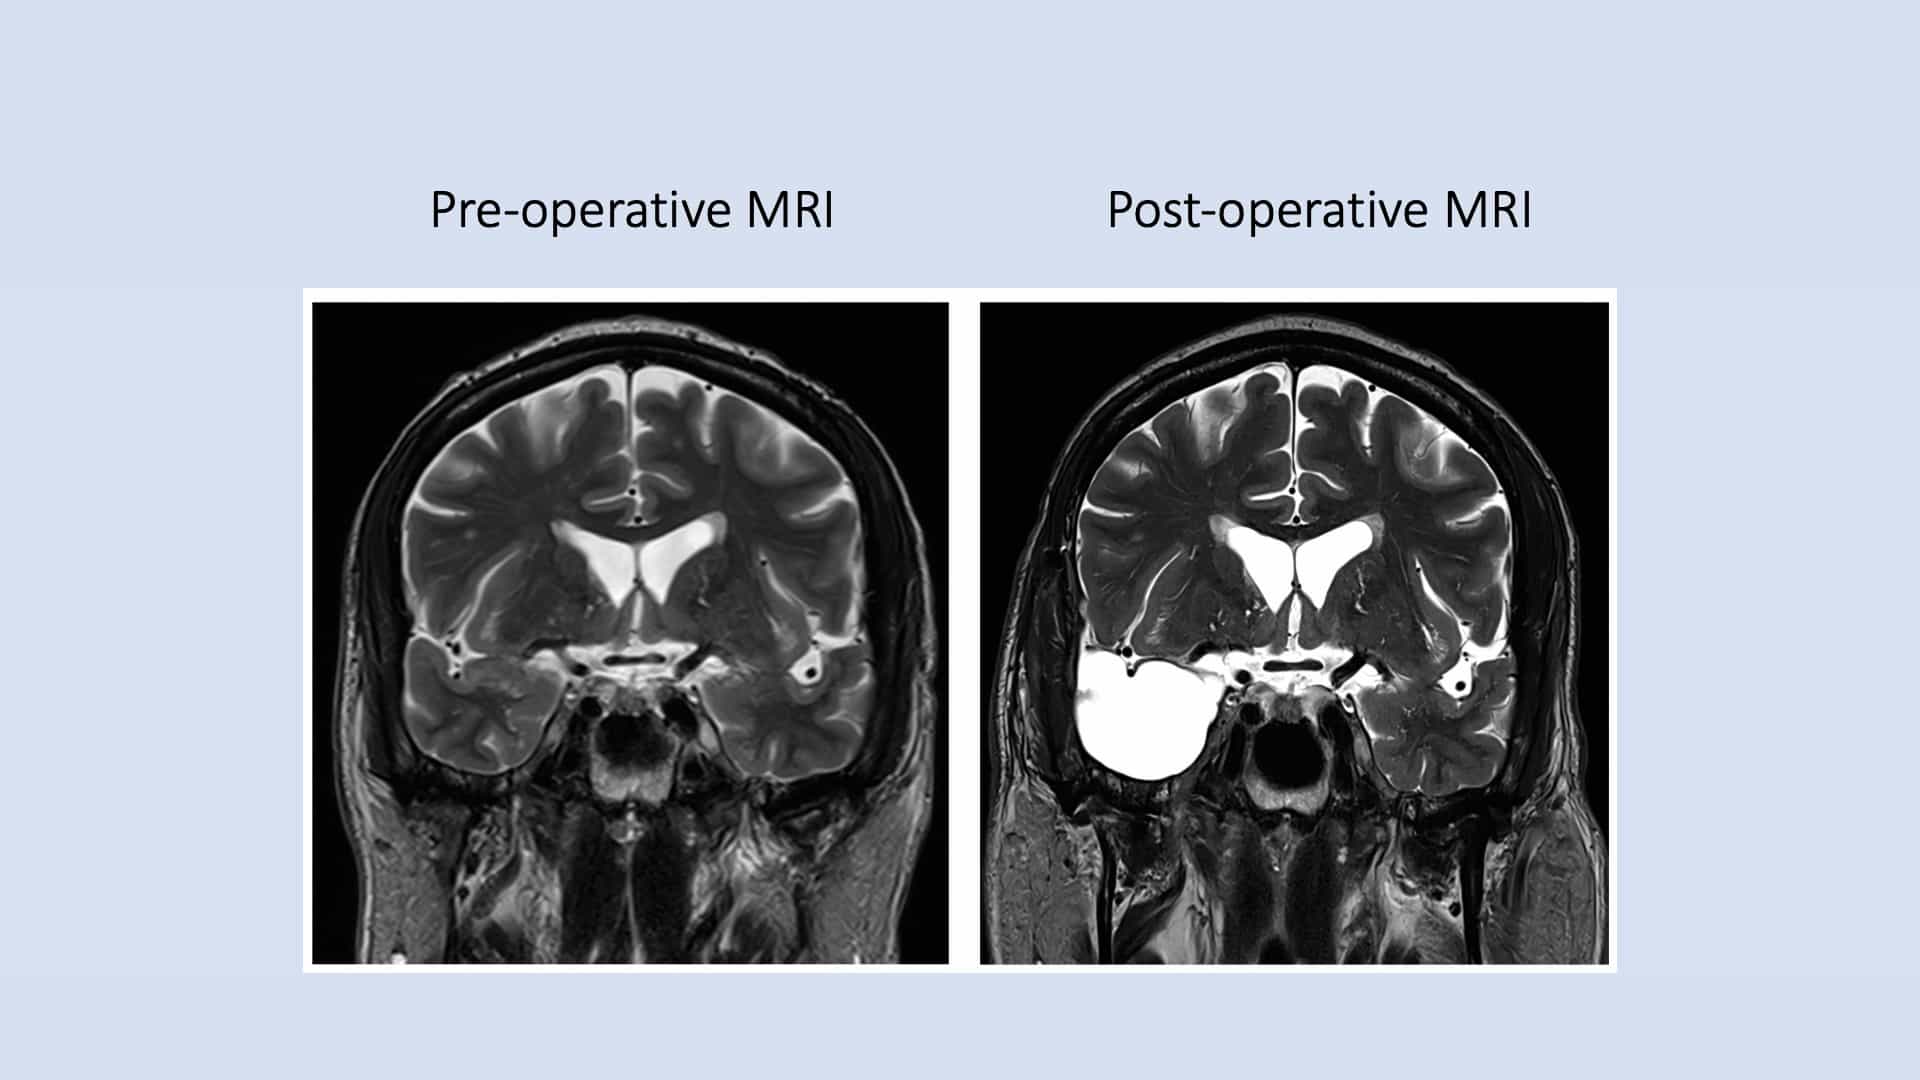
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Real-time magnetic resonance-guided stereotactic laser amygdalohippocampotomy for mesial temporal lobe epilepsy
Jon T Willie1, Nealen G Laxpati, Daniel L Drane
1Departments of *Neurosurgery, ‡Neurology, §Pathology, and ¶Radiology and Imaging Sciences, Emory University School of Medicine, Atlanta, Georgia; ‖Interventional MRI Program, Emory University Hospital, Atlanta, Georgia; #Coulter Department of Biomedical Engineering, Georgia Institute of Technology, Atlanta, Georgia; **Department of Neurology, University of Washington School of Medicine, Seattle, Washington; ††Visualase, Inc., Houston, Texas.

Background:
Open surgery effectively treats mesial temporal lobe epilepsy, but carries the risk of neurocognitive deficits, which may be reduced with minimally invasive alternatives.
Objective:
To describe technical and clinical outcomes of stereotactic laser amygdalohippocampotomy with real-time magnetic resonance thermal imaging guidance.
Methods:
With patients under general anesthesia and using standard stereotactic methods, 13 adult patients with intractable mesial temporal lobe epilepsy (with and without mesial temporal sclerosis [MTS]) prospectively underwent insertion of a saline-cooled fiberoptic laser applicator in amygdalohippocampal structures from an occipital trajectory. Computer-controlled laser ablation was performed during continuous magnetic resonance thermal imaging followed by confirmatory contrast-enhanced anatomic imaging and volumetric reconstruction. Clinical outcomes were determined from seizure diaries.
Results:
A mean 60% volume of the amygdalohippocampal complex was ablated in 13 patients (9 with MTS) undergoing 15 procedures. Median hospitalization was 1 day. With follow-up ranging from 5 to 26 months (median, 14 months), 77% (10/13) of patients achieved meaningful seizure reduction, of whom 54% (7/13) were free of disabling seizures. Of patients with preoperative MTS, 67% (6/9) achieved seizure freedom. All recurrences were observed before 6 months. Variances in ablation volume and length did not account for individual clinical outcomes. Although no complications of laser therapy itself were observed, 1 significant complication, a visual field defect, resulted from deviated insertion of a stereotactic aligning rod, which was corrected before ablation.
Conclusion:
Real-time magnetic resonance-guided stereotactic laser amygdalohippocampotomy is a technically novel, safe, and effective alternative to open surgery. Further evaluation with larger cohorts over time is warranted.
More Related Videos
 09:49
Using a Bipolar Electrode to Create a Temporal Lobe Epilepsy Mouse Model by Electrical Kindling of the Amygdala
Published on: June 29, 2022
 04:50
Operative Technique and Nuances for the Stereoelectroencephalographic SEEG Methodology Utilizing a Robotic Stereotactic Guidance System
Published on: June 9, 2023