Related Experiment Video
Updated: May 2, 2026
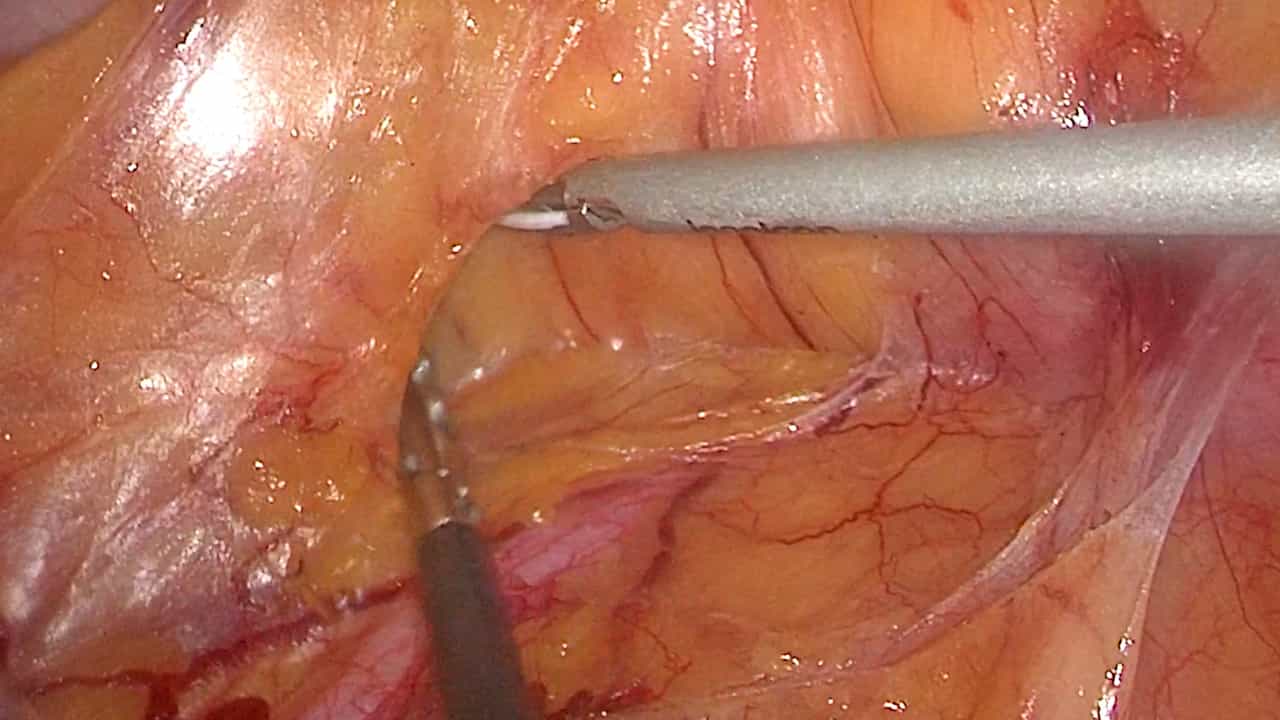
Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Complete mesocolic excision with D3 lymph node dissection in laparoscopic colectomy for stages II and III colon
J W Shin1, A H Y Amar, S H Kim
1Colorectal Division, Department of Surgery, Korea University Anam Hospital, Korea University College of Medicine, 126-1, 5 ga, Anam-dong, Seongbuk-gu, Seoul, 136-705, South Korea.

Background:
There is emerging evidence that complete mesocolic excision (CME) for colon cancer produces favorable oncologic outcomes. The applicability of CME technique in laparoscopic colectomy has not been fully explored. The aim of our retrospective study was to evaluate the feasibility of the CME technique with D3 lymphadenectomy in laparoscopic colectomy and its short- and long-term outcomes.
Methods:
Between September 2006 and December 2009, 168 laparoscopic colectomies were performed for stages II and III colon cancer. Prospectively, collected data on demographics, tumor characteristics, complications, and outcomes were analyzed retrospectively.
Results:
Eighty-seven patients (51.8 %) had stage II colon cancer, and 81 patients had stage III cancer. The mean operative time was 196.0 ± 61.2 min. The overall morbidity rate was 17.8 %, which included anastomotic leak in 10 patients (5.9 %). There was no operative mortality. The number of lymph nodes harvested was 27.8 ± 13.6. With a median follow-up of 57.3 months, locoregional recurrence and systemic metastasis developed in 6 (3.6 %) and 14 patients (8.3 %), respectively. Seven patients died of causes related to cancer, and all had stage III cancer. Disease-free survival at 5-years was 95.2 % for patients with stage II and 80.9 % for patients with stage III.
Conclusions:
Standardization of laparoscopic CME and D3 lymphadenectomy is expedient. The technique is associated with acceptable morbidity and provides excellent oncologic outcomes for stage II and stage III colon cancer. A longer follow-up is needed to validate the enhancement of oncological outcome related to this surgical concept.
More Related Videos
 05:43
The Role of Anatomical Dissection in Defining Colic and Small Bowel Artery Lymphovascular Bundles in the D3 Volume of Small and Large Bowel Mesentery
Published on: August 1, 2025
 12:45
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022