Related Experiment Video
Updated: May 2, 2026

Normothermic Negative Pressure Ventilation Ex Situ Lung Perfusion: Evaluation of Lung Function and Metabolism
Published on: February 14, 2022
Mechanical ventilation after lung transplantation. An international survey of practices and preferences
Alison Beer1, Robert M Reed, Servet Bölükbas
11 University of Iowa Hospitals and Clinics, Iowa City, Iowa.

Rationale:
Between 10% and 57% of lung transplant (LTx) recipients develop primary graft dysfunction (PGD) within 72 hours of LTx. PGD is clinically and histologically analogous to the acute respiratory distress syndrome. In patients at risk for or with acute respiratory distress syndrome, lung-protective ventilation strategies (low tidal volume and positive end-expiratory pressure) improve outcomes. There is, however, little information available on mechanical ventilation strategies after LTx.
Objectives:
Our aim in this international survey was to describe the current practices of mechanical ventilation immediately after LTx.
Methods:
An electronic survey was sent to the medical and surgical directors of U.S. LTx programs (n = 111) and to members of the Pulmonary Council of the International Society for Heart and Lung Transplantation (n = 470).
Results:
A total of 149 individuals from 18 countries responded to the questionnaire. The most common modes of ventilation were pressure assist/control (37%) and volume assist/control (35%). Tidal volumes were most often determined by recipient characteristics. Donor characteristics were rarely considered (35%) and were infrequently known by the team managing the ventilator (42%). When presented with a choice of ideal tidal volumes, a majority of respondents selected 6 ml/kg recipient predicted body weight (58%), fewer selected 10 ml/kg (21%), and none selected 15 ml/kg. A majority preferred limiting the fraction of inspired oxygen rather than positive end-expiratory pressure (PEEP) (69% versus 31%, P = 0.006). The median minimum PEEP was 5 cm H2O, and the median maximum PEEP was 11.5 cm H2O. The presence of PGD increased the perceived importance of monitoring plateau pressure to adjust tidal volumes. The median plateau pressure limit perceived as a threshold triggering reduction in tidal volume was 30 cm H2O.
Conclusions:
Most respondents reported using lung-protective approaches to mechanical ventilation after lung transplantation. Low tidal volumes based on recipient characteristics were frequently chosen. Donor characteristics often were not considered and frequently were not known by the team managing mechanical ventilation after LTx.

Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:14
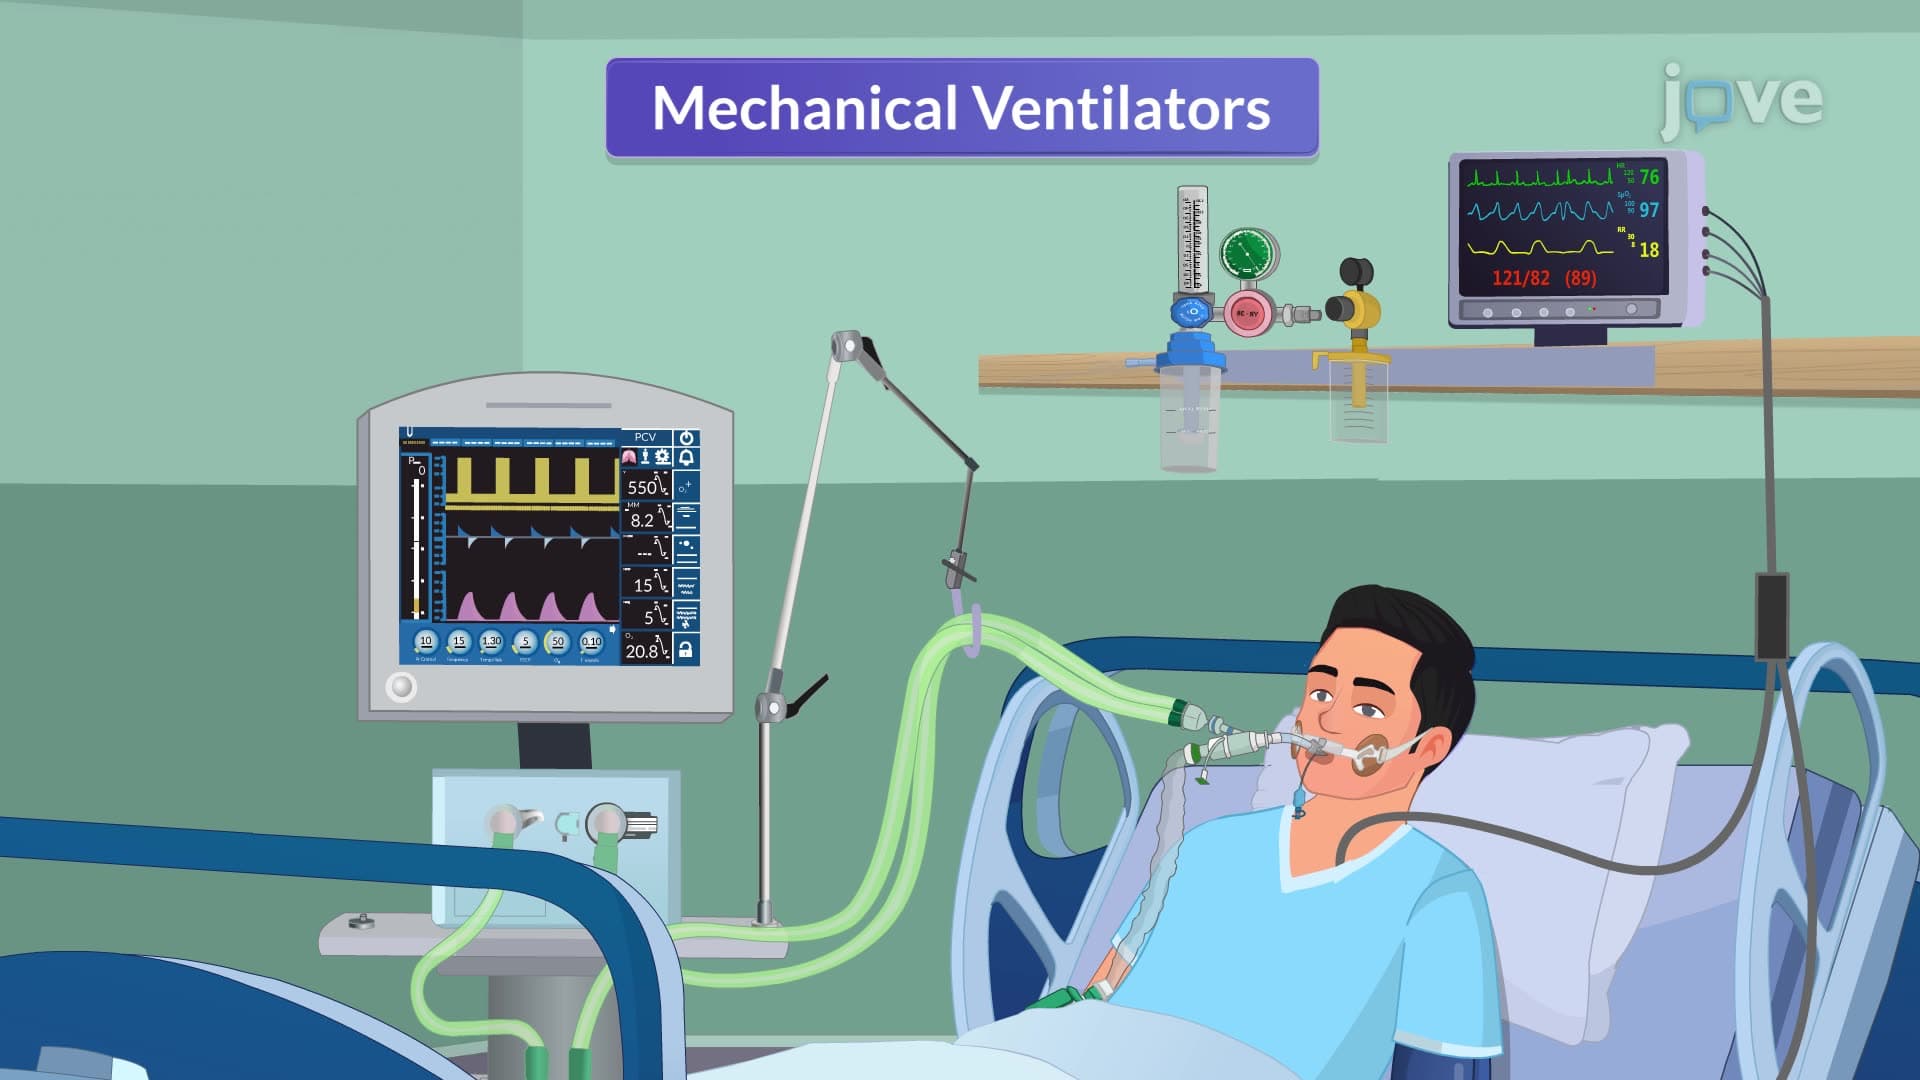
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...