Related Experiment Video
Updated: May 1, 2026
Intravital Microscopy of the Inguinal Lymph Node
Published on: April 4, 2011
Lymph node count at inguinofemoral lymphadenectomy and groin recurrences in vulvar cancer
Heleen J van Beekhuizen1, Maria Auzin, Loes C G van den Einden
1*Erasmus MC Cancer Centre, Rotterdam, the Netherlands; †ZNA Middelheim, Antwerp, Belgium; ‡Radboud University Medical Center, Nijmegen; §Center for Gynaecologic Oncology Amsterdam, Academic Medical Center, Amsterdam; and ∥Erasmus Medical Center, Rotterdam, the Netherlands.

Objective:
The objective of the study is to determine the risk factors for groin recurrence (GR) in patients with primary vulvar squamous cell carcinoma (SCC) after inguinofemoral lymphadenectomy (IFL) without lymph node metastases and/or adjuvant chemoradiotherapy.
Methods:
The study is a multicenter retrospective review of clinical and histopathological data of patients with lymph node-negative vulvar SCC who underwent an IFL. Patients with and without GRs were compared to identify risk factors.
Results:
In 134 patients, 252 groins were eligible for the analyses--16 patients underwent ipsilateral IFL and 118 patients underwent bilateral IFL. Groin recurrences occurred in 4 (1.6%) of the 252 dissected groins. Besides, 1 patient who underwent ipsilateral IFL had a recurrence in the nonoperated contralateral groin; this groin was left out of analysis. The median number of dissected nodes per groin was 9.8 (range, 1-38) in all patients and 6.5 (range, 5-8) in patients with GR. Multivariate analyses showed that GR was related to poor differentiation (P = 0.04), and node count less than 9 (P = 0.04), no association with age, tumor localization, tumor diameter, focality, invasion depth, or stage was found. Nineteen patients with both low node count and poor differentiation had 19% GRs. Survival analyses showed less favorable survival in patients with poor differentiation.
Conclusions:
The overall risk of developing GR after negative IFL in patients with vulvar SCC is low (1.6% per groin) but significantly higher in patients with tumors with a poor differentiation and lymph node count less than 9 at IFL. A large well-designed prospective study is needed to evaluate closer surveillance in patients at risk.

Related Concept Videos
 01:23
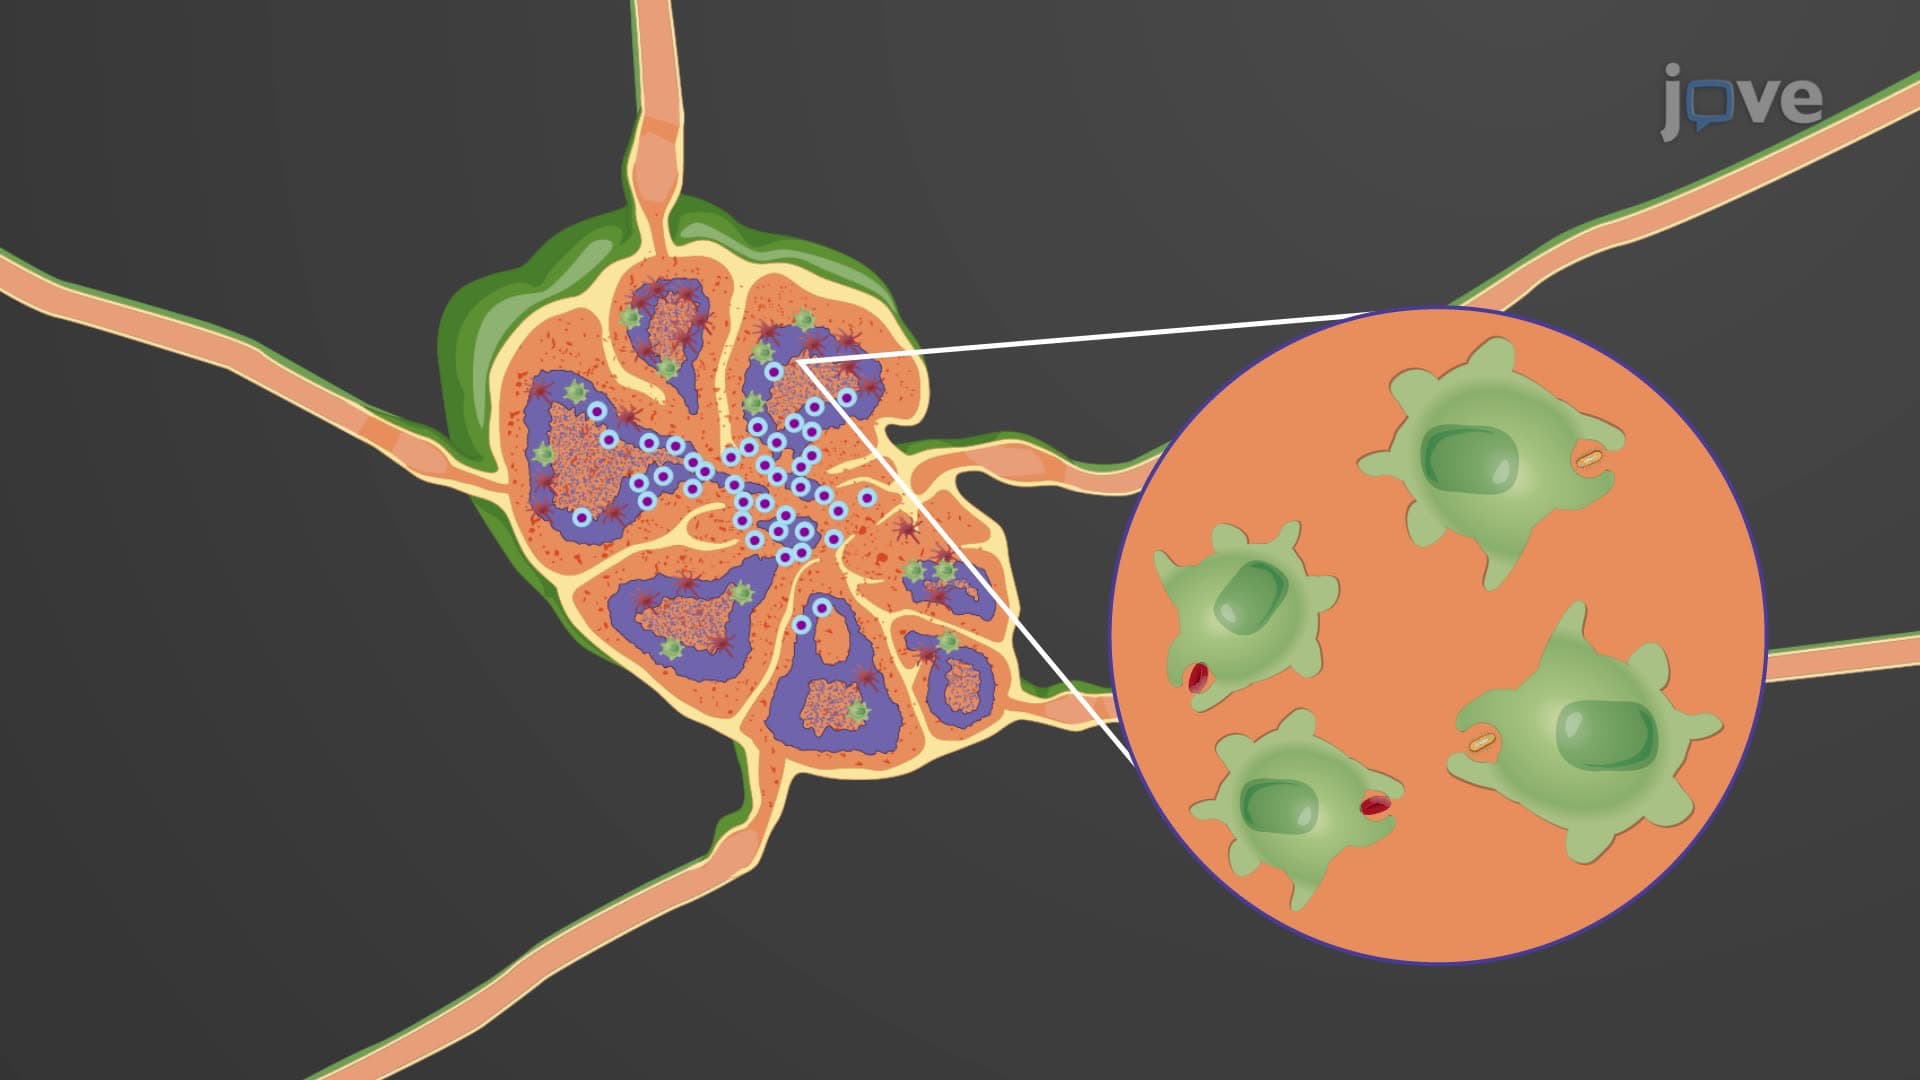
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...
 01:15
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...