Related Experiment Video
Updated: May 1, 2026


Laparoscopic Choledochal Cyst Excision and Roux-en-Y Choledochojejunostomy in Adults
Published on: February 28, 2025
Cholecystectomy, gallstones, tonsillectomy, and pancreatic cancer risk: a population-based case-control study in
J Zhang1, A E Prizment2, I B Dhakal3
11] Department of Epidemiology, Indiana University, Richard M. Fairbanks School of Public Health at IUPUI, Indianapolis, IN 46202, USA [2] Melvin and Bren Simon Cancer Center, Indiana University, Indianapolis, IN 46202, USA.

Background:
Associations between medical conditions and pancreatic cancer risk are controversial and are thus evaluated in a study conducted during 1994-1998 in Minnesota.
Methods:
Cases (n=215) were ascertained from hospitals in the metropolitan area of the Twin Cities and the Mayo Clinic. Controls (n=676) were randomly selected from the general population and frequency matched to cases by age and sex. The history of medical conditions was gathered with a questionnaire during in-person interviews. Odds ratios (OR) and 95% confidence intervals (95% CI) were estimated using unconditional logistic regression.
Results:
After adjustment for confounders, subjects who had cholecystectomy or gallstones experienced a significantly higher risk of pancreatic cancer than those who did not (OR (95% CI): 2.11 (1.32-3.35) for cholecystectomy and 1.97 (1.23-3.12) for gallstones), whereas opposite results were observed for tonsillectomy (0.67 (0.48-0.94)). Increased risk associated with cholecystectomy was the greatest when it occurred ≤ 2 years before the cancer diagnosis (5.93 (2.36-15.7)) but remained statistically significant when that interval was ≥ 20 years (2.27 (1.16-4.32)).
Conclusions:
Cholecystectomy, gallstones, and tonsillectomy were associated with an altered risk of pancreatic cancer. Our study suggests that cholecystectomy increased risk but reverse causality may partially account for high risk associated with recent cholecystectomy.
Insights
Gallstones and cholecystectomy (gallbladder removal) were linked to a higher risk of pancreatic cancer. Tonsillectomy showed a reduced risk. Recent gallbladder removal showed the highest risk increase.
Area of Science:
- Epidemiology
- Gastroenterology
- Oncology
Background:
- Associations between medical conditions and pancreatic cancer risk remain controversial.
- This study evaluated these associations in a Minnesota population between 1994-1998.
Purpose of the Study:
- To investigate the relationship between specific medical conditions and the risk of developing pancreatic cancer.
Main Methods:
- A case-control study involving 215 pancreatic cancer cases and 676 controls from the Twin Cities and Mayo Clinic.
- Medical history was collected via questionnaires during in-person interviews.
- Unconditional logistic regression was used to estimate odds ratios (OR) and 95% confidence intervals (95% CI).
Main Results:
- Cholecystectomy (OR: 2.11) and gallstones (OR: 1.97) were significantly associated with increased pancreatic cancer risk.
- Tonsillectomy showed a reduced risk (OR: 0.67).
- The risk increase from cholecystectomy was highest within 2 years of diagnosis (OR: 5.93) but remained significant even after 20 years (OR: 2.27).
Conclusions:
- Cholecystectomy, gallstones, and tonsillectomy are associated with altered pancreatic cancer risk.
- The study suggests cholecystectomy increases risk, with potential for reverse causality explaining recent associations.
Related Concept Videos
 01:20
Cholecystitis
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:21
Chronic Pancreatitis II: Pathophysiology
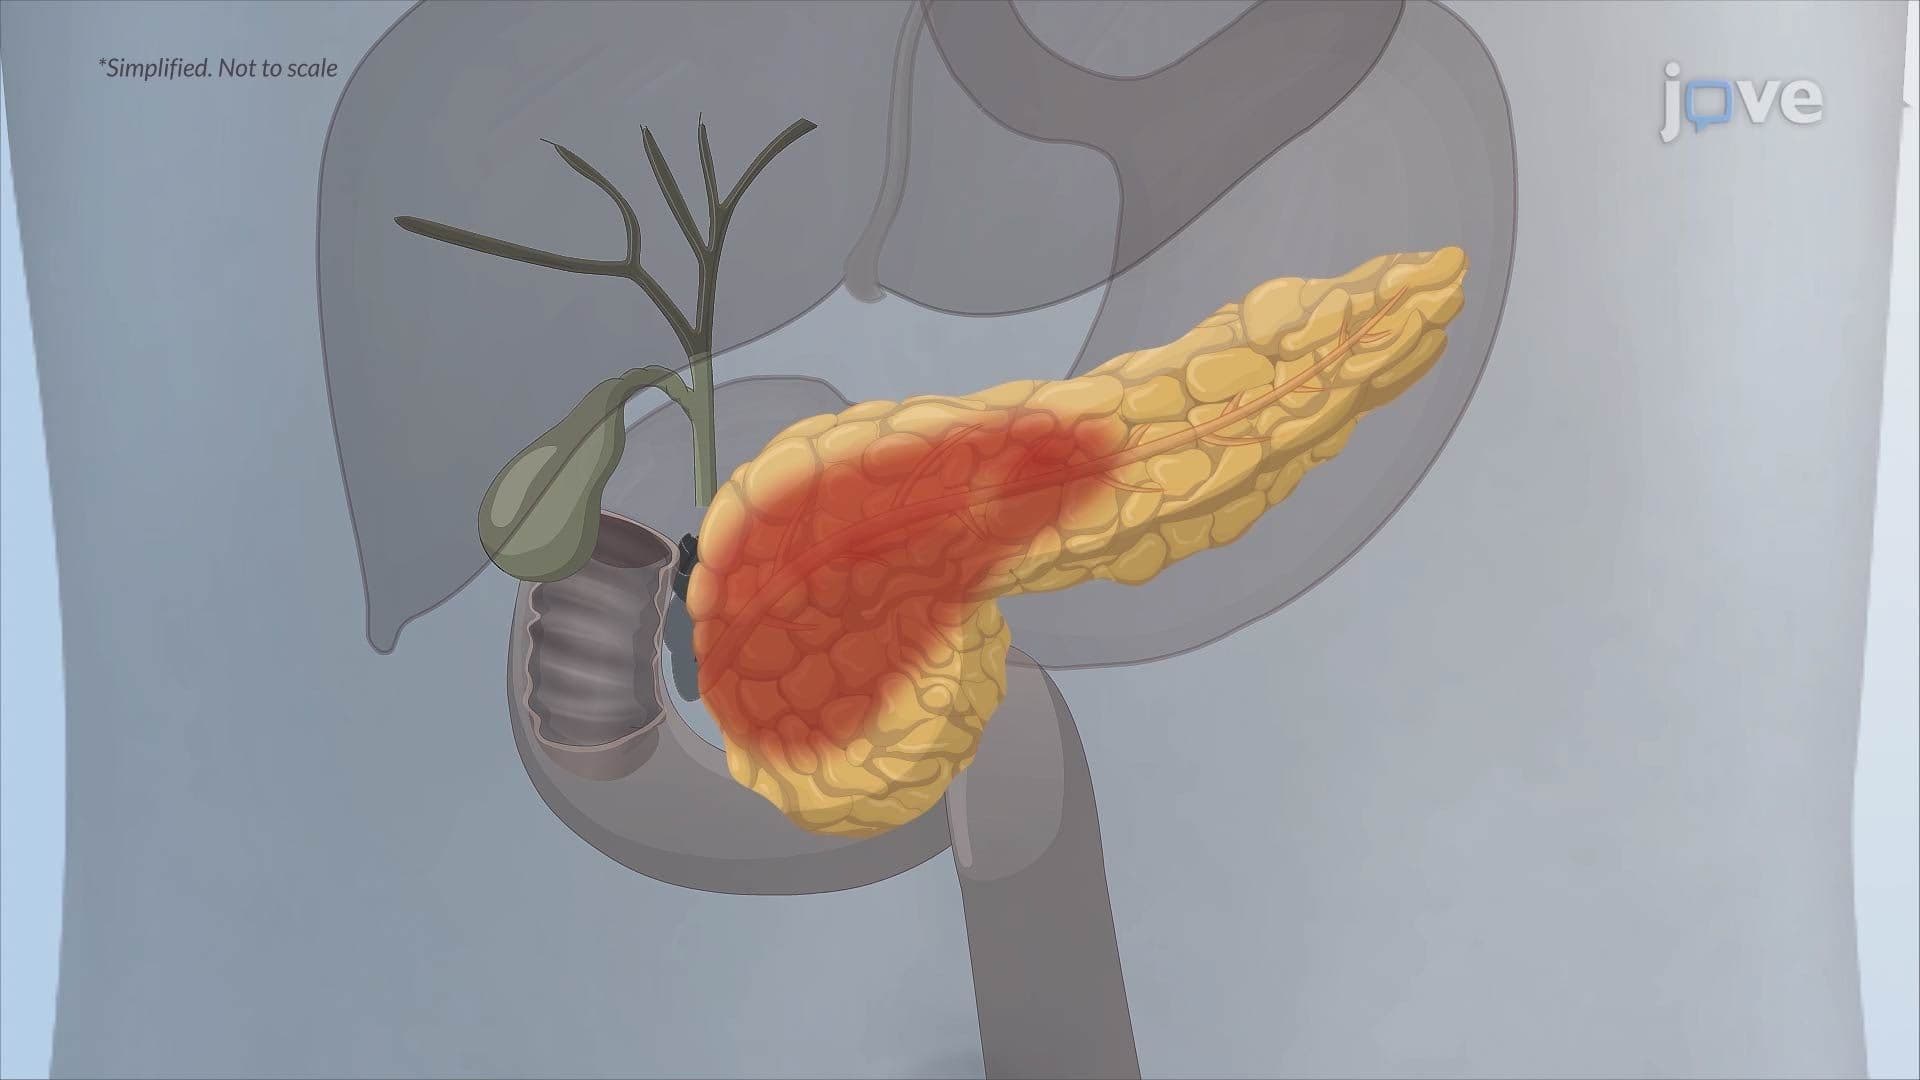 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...