Related Experiment Video
Updated: May 1, 2026
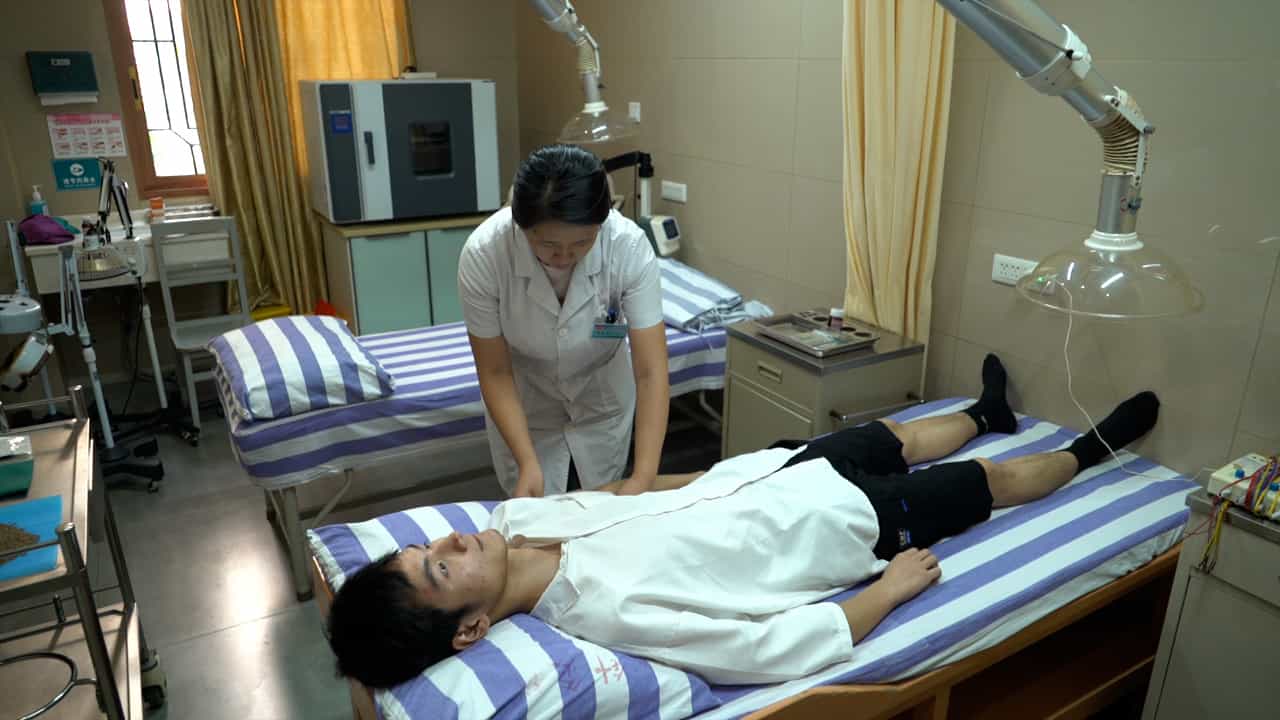

Electroacupuncture Combined with Chinese Medicine Ironing Therapy for Functional Constipation
Published on: July 5, 2024
Biofeedback for treatment of chronic idiopathic constipation in adults
Sue Woodward1, Christine Norton, Pauline Chiarelli
1King's College London, 57 Waterloo Road, London, UK, SE1 8WA.

Background:
Biofeedback therapy has been used to treat the symptoms of people with chronic constipation referred to specialist services within secondary and tertiary care settings. However, different methods of biofeedback are used within different centres and the magnitude of suggested benefits and comparable effectiveness of different methods of biofeedback has yet to be established.
Objectives:
To determine the efficacy and safety of biofeedback for the treatment of chronic idiopathic (functional) constipation in adults.
Search Methods:
We searched the following databases from inception to 16 December 2013: CENTRAL, the Cochrane Complementary Medicine Field, the Cochrane IBD/FBD Review Group Specialized Register, MEDLINE, EMBASE, CINAHL, British Nursing Index, and PsychINFO. Hand searching of conference proceedings and the reference lists of relevant articles was also undertaken.
Selection Criteria:
All randomised trials evaluating biofeedback in adults with chronic idiopathic constipation were considered for inclusion.
Data Collection And Analysis:
The primary outcome was global or clinical improvement as defined by the included studies. Secondary outcomes included quality of life, and adverse events as defined by the included studies. Where possible, we calculated the risk ratio (RR) and corresponding 95% confidence interval (CI) for dichotomous outcomes and the mean difference (MD) and 95% CI for continuous outcomes. We assessed the methodological quality of included studies using the Cochrane risk of bias tool. The overall quality of the evidence supporting each outcome was assessed using the GRADE criteria.
Main Results:
Seventeen eligible studies were identified with a total of 931 participants. Most participants had chronic constipation and dyssynergic defecation. Sixteen of the trials were at high risk of bias for blinding. Attrition bias (4 trials) and other potential bias (5 trials) was also noted. Due to differences between study populations, the heterogeneity of the different samples and large range of different outcome measures, meta-analysis was not possible. Different effect sizes were reported ranging from 40 to 100% of patients who received biofeedback improving following the intervention. While electromyograph (EMG) biofeedback was the most commonly used, there is a lack of evidence as to whether any one method of biofeedback is more effective than any other method of biofeedback. We found low or very low quality evidence that biofeedback is superior to oral diazepam, sham biofeedback and laxatives. One study (n = 60) found EMG biofeedback to be superior to oral diazepam. Seventy per cent (21/30) of biofeedback patients had improved constipation at three month follow-up compared to 23% (7/30) of diazepam patients (RR 3.00, 95% CI 1.51 to 5.98). One study compared manometry biofeedback to sham biofeedback or standard therapy consisting of diet, exercise and laxatives. The mean number of complete spontaneous bowel movements (CSBM) per week at three months was 4.6 in the biofeedback group compared to 2.8 in the sham biofeedback group (MD 1.80, 95% CI 1.25 to 2.35; 52 patients). The mean number of CSBM per week at three months was 4.6 in the biofeedback group compared to 1.9 in the standard care group (MD 2.70, 95% CI 1.99 to 3.41; 49 patients). Another study (n = 109) compared EMG biofeedback to conventional treatment with laxatives and dietary and lifestyle advice. This study found that at both 6 and 12 months 80% (43/54) of biofeedback patients reported clinical improvement compared to 22% (12/55) laxative-treated patients (RR 3.65, 95% CI 2.17 to 6.13). Some surgical procedures (partial division of puborectalis and stapled transanal rectal resection (STARR)) were reported to be superior to biofeedback, although with a high risk of adverse events in the surgical groups (wound infection, faecal incontinence, pain, and bleeding that required further surgical intervention). Successful treatment, defined as a decrease in the obstructed defecation score of > 50% at one year was reported in 33% (3/39) of EMG biofeedback patients compared to 82% (44/54) of STARR patients (RR 0.41, 95% CI 0.26 to 0.65). For the other study the mean constipation score at one year was 16.1 in the balloon sensory biofeedback group compared to 10.5 in the partial division of puborectalis surgery group (MD 5.60, 95% CI 4.67 to 6.53; 40 patients). Another study (n = 60) found no significant difference in efficacy did not demonstrate the superiority of a surgical intervention (posterior myomectomy of internal anal sphincter and puborectalis) over biofeedback. Conflicting results were found regarding the comparative effectiveness of biofeedback and botulinum toxin-A. One small study (48 participants) suggested that botulinum toxin-A injection may have short term benefits over biofeedback, but the relative effects of treatments were uncertain at one year follow-up. No adverse events were reported for biofeedback, although this was not specifically reported in the majority of studies. The results of all of these studies need to be interpreted with caution as GRADE analyses rated the overall quality of the evidence for the primary outcomes (i.e. clinical or global improvement as defined by the studies) as low or very low due to high risk of bias (i.e. open label studies, self-selection bias, incomplete outcome data, and baseline imbalance) and imprecision (i.e. sparse data).
Authors' Conclusions:
Currently there is insufficient evidence to allow any firm conclusions regarding the efficacy and safety of biofeedback for the management of people with chronic constipation. We found low or very low quality evidence from single studies to support the effectiveness of biofeedback for the management of people with chronic constipation and dyssynergic defecation. However, the majority of trials are of poor methodological quality and subject to bias. Further well-designed randomised controlled trials with adequate sample sizes, validated outcome measures (especially patient reported outcome measures) and long-term follow-up are required to allow definitive conclusions to be drawn.

Related Concept Videos
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:30
Irritable Bowel Syndrome III: Medical and Nursing Management
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...
 01:23
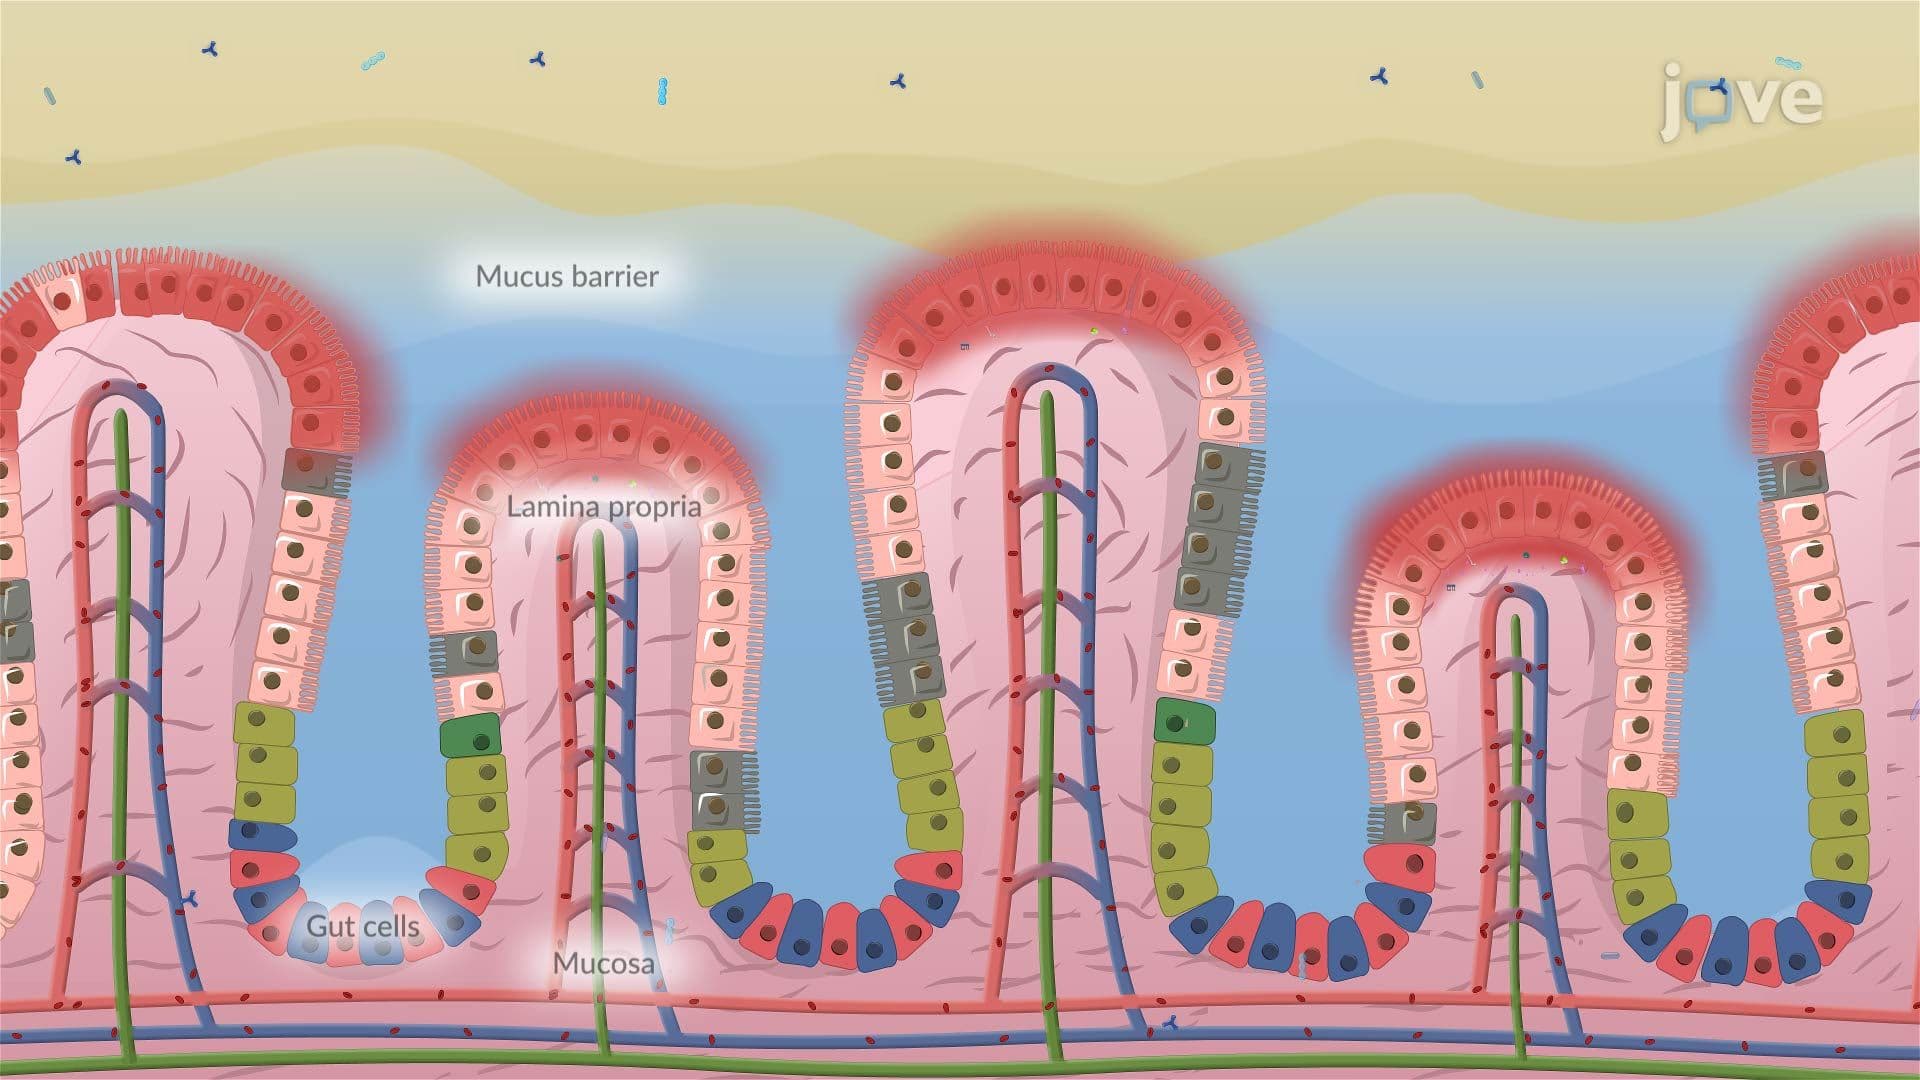
Irritable Bowel Syndrome