Related Experiment Video
Updated: May 1, 2026
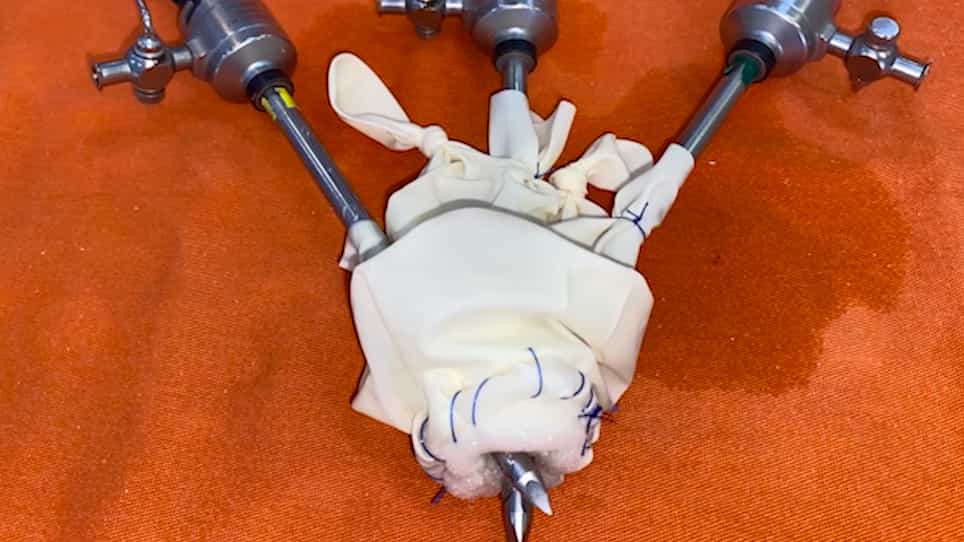

Low-Cost Single-Port LoCoSP Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
[Surgical management of cervical esophageal carcinoma in 16 cases]

Objective:
To investigate the method of surgical management for cervical esophageal carcinoma and the feasibility of the operation with preservation of laryngeal function.
Method:
Sixteen patients with cervical esophageal carcinoma who received surgical treatment were reviewed in our retrospective study. Removal of total hypopharynx and larynx and the inversion stripping esophagectomy were conducted in thirteen patients, of which one underwent the reconstraction with residual larynx and tracheal flap and the other twelve patients underwent the reconstraction with gastric-pharyngeal anastomosis. One patient received the cervical esophagectomy and partial hypopharyngectomy with laryngotracheal flap. The inversion stripping esophagectomy with laryngeal function preservation were conducted in two patients, who received the reconstraction with gastric-pharyngeal anastomosis and preserved total larynx. All the patients were carried out the bilateral neck dissections.
Result:
The surgical resection rate was 100% and no operative death occurred. The postoperative complications included pulmonary infection in two cases, anastomotic fistula in two cases, anastomotic stenosis in two cases and congestive heart failure in one case. The retained rate of the laryngeal function is 12.5%. The 3-year survival rate is 30.7%, and the 5-year survival rate is 23.1%.
Conclusion:
The surgical treatment of cervical esophageal carcinoma is possible. The inversion stripping esophagectomy without thoracotomy is performed to resect the tumor. The esophageal defect could be reconstructed by laryngotracheal flap or gastric-pharyngeal anastomosis. The laryngeal function should be remained as far as possible according to the location and extension of the tumor.

Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...