Related Experiment Video
Updated: May 1, 2026

Laparoscopic Pancreatoduodenectomy With Modified Blumgart Pancreaticojejunostomy
Published on: June 17, 2018
Laparoscopic transgastric endolumenal cystogastrostomy and pancreatic debridement
Kerri A Simo1, David J Niemeyer, Ryan Z Swan
1Section of Hepatobiliary and Pancreas Surgery, Department of General Surgery, Carolinas Medical Center, Charlotte, NC, USA.

Background:
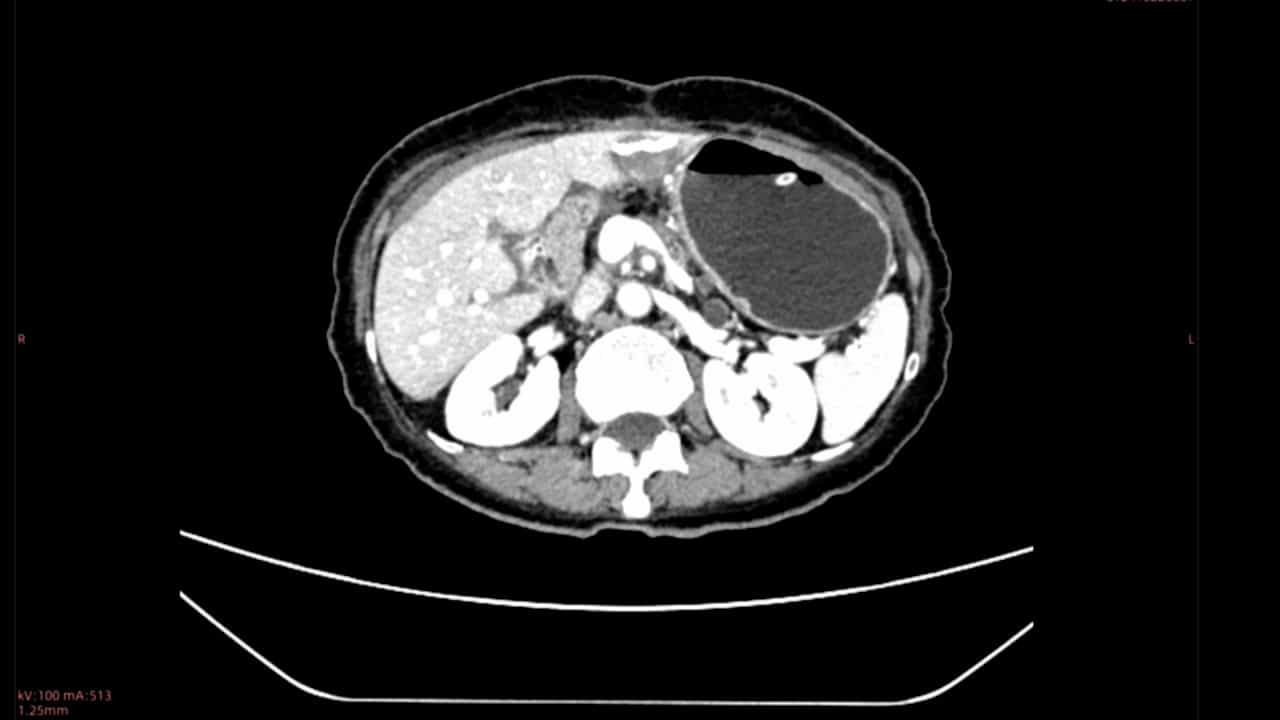
Cystogastrostomy is commonly performed for internal drainage of pancreatic pseudocysts (PP) and concomitant debridement of walled-off pancreatic necrosis (WOPN). While an open approach to cystogastrostomy is well established, an optimal minimally invasive technique continues to evolve. This laparoscopic transgastric endolumenal cystogastrostomy presented here allows for a large cystogastrostomy with complete debridement of necrosis and internal drainage through a minimally invasive approach.
Methods:
We performed a retrospective review of 22 patients with symptomatic PP/WOPN treated with attempted laparoscopic transgastric endolumenal cystogastrostomy (Lap-TEC) and pancreatic debridement. Short- and long-term outcomes were assessed.
Results:
From November 2006 to March 2013, a total of 22 Lap-TEC/pancreatic debridement procedures were attempted; 15 were completed laparoscopically. The median age of the cohort was 49.5 ± 12 years (range = 18-71), average body mass index = 29.1 kg/m(2), 77 % had an ASA score ≥ 3, and 10 were female. Gallstones were the most common etiology (50 %), and median time between initial presentation and surgery was 86 days (range = 0-360). Median operative time and estimated blood loss were 213 min and 100 cc, respectively. Forty-one percent of the patients were admitted to the ICU postoperatively and the average length of stay was 14 days (range = 4-50). Median follow-up was 2 months (range = 0-62.5), with one patient having a procedure-related complication. No other reoperations, late complications, or mortalities occurred. All patients had resolution of their symptoms and fluid collections.
Conclusion:
This technique of internal drainage via Lap-TEC and pancreatic debridement has been successful in achieving primary drainage and relieving symptoms of PP/WOPN with no mortality and minimal morbidity.