Related Experiment Video
Updated: May 1, 2026

Author Spotlight: Assessing Ischemic Stroke Damage Through Middle Cerebral Artery Occlusion Model
Published on: August 11, 2023
Blunt traumatic occlusion of the internal carotid and vertebral arteries
Ryan P Morton1, Brian W Hanak, Michael R Levitt
1Departments of Neurological Surgery and.

Insights
Blunt cerebrovascular occlusion (Biffl Grade IV injury) in the internal carotid artery (ICA) carries a high stroke risk, but vertebral artery (VA) injury is less severe. Embolic monitoring and antiplatelet therapy are recommended for ICA injuries.
Area of Science:
- Neurology
- Vascular Surgery
- Trauma Surgery
Background:
- Blunt cerebrovascular occlusion (Biffl Grade IV injury) is rare, with poorly defined stroke rates, management, and outcomes.
- Both hemodynamic failure and embolic mechanisms contribute to stroke after blunt cerebrovascular occlusion.
Purpose of the Study:
- To evaluate a single institution's experience with Biffl Grade IV injuries.
- To elucidate stroke mechanisms and determine optimal management for these injuries.
Main Methods:
- Retrospective review of internal carotid artery (ICA) or vertebral artery (VA) Biffl Grade IV injuries over 7 years.
- Analysis of stroke rates, mechanisms, and treatment effects.
Main Results:
- Internal carotid artery (ICA) Biffl Grade IV injuries had a 64% stroke rate, while unilateral vertebral artery (VA) injuries had a 9% stroke rate.
- Posterior communicating artery diameter >1mm on CT angiography was protective against hemodynamic stroke in ICA injuries (p = 0.015).
- Embolic monitoring via TCD (≥8 emboli/hr) predicted embolic stroke in ICA injuries (p = 0.006); VA strokes were embolic and asymptomatic.
Conclusions:
- Traumatic ICA occlusion is rare but has a high stroke rate; collateral circulation may reduce severity.
- Embolic monitoring with TCD and prophylactic antiplatelet therapy are recommended for ICA Biffl Grade IV injuries.
- Unilateral VA Biffl Grade IV injury is common, less morbid, and does not benefit from embolic monitoring or prophylactic antiplatelet therapy.
Object:
The stroke rate, management, and outcome after blunt cerebrovascular occlusion (Biffl Grade IV injury) is not well defined, given the rarity of the disease. Both hemodynamic failure and embolic mechanisms have been implicated in the pathophysiology of subsequent stroke after blunt cerebrovascular occlusion. In this study, the authors evaluated their center's experience with Biffl Grade IV injuries, focusing on elucidating the mechanisms of stroke and their optimal management.
Methods:
A retrospective review identified all internal carotid artery (ICA) or vertebral artery (VA) Biffl Grade IV injuries over a 7-year period at a single institution.
Results:
Fifty-nine Biffl Grade IV injuries were diagnosed affecting 11 ICAs, 44 unilateral VAs, and 2 bilateral VAs. The stroke rates were 64%, 9%, and 50%, respectively. Of the 11 Biffl Grade IV ICA injuries, 5 presented with stroke while 2 developed delayed stroke. An ipsilateral posterior communicating artery greater than 1 mm on CT angiography was protective against stroke due to hemodynamic failure (p = 0.015). All patients with Biffl Grade IV injuries affecting the ICA who had at least 8 emboli per hour on transcranial Doppler (TCD) ultrasonography developed an embolic pattern of stroke (p = 0.006). Treatment with aspirin versus dual antiplatelet therapy had a similar effect on stroke rate in the ICA group (p = 0.5) and all patients who suffered stroke either died (n = 3) or required a decompressive hemicraniectomy with subsequent poor outcome (n = 4). All 10 strokes associated with Biffl Grade IV VA injuries were embolic and clinically asymptomatic. In VA Biffl Grade IV injury, neither the presence of emboli nor treatment with antiplatelet agents affected stroke rates.
Conclusions:
At the authors' institution, traumatic ICA occlusion is rare but associated with a high stroke rate. Robust collateral circulation may mitigate its severity. Embolic monitoring with TCD ultrasonography and prophylactic antiplatelet therapy should be used in all ICA Biffl Grade IV injuries. Unilateral VA Biffl Grade IV injury is the most common type of traumatic occlusion and is associated with significantly less morbidity. Embolic monitoring using TCD and prophylactic antiplatelet therapy do not appear to be beneficial in patients with traumatic VA occlusion.
More Related Videos

Related Concept Videos
 01:26
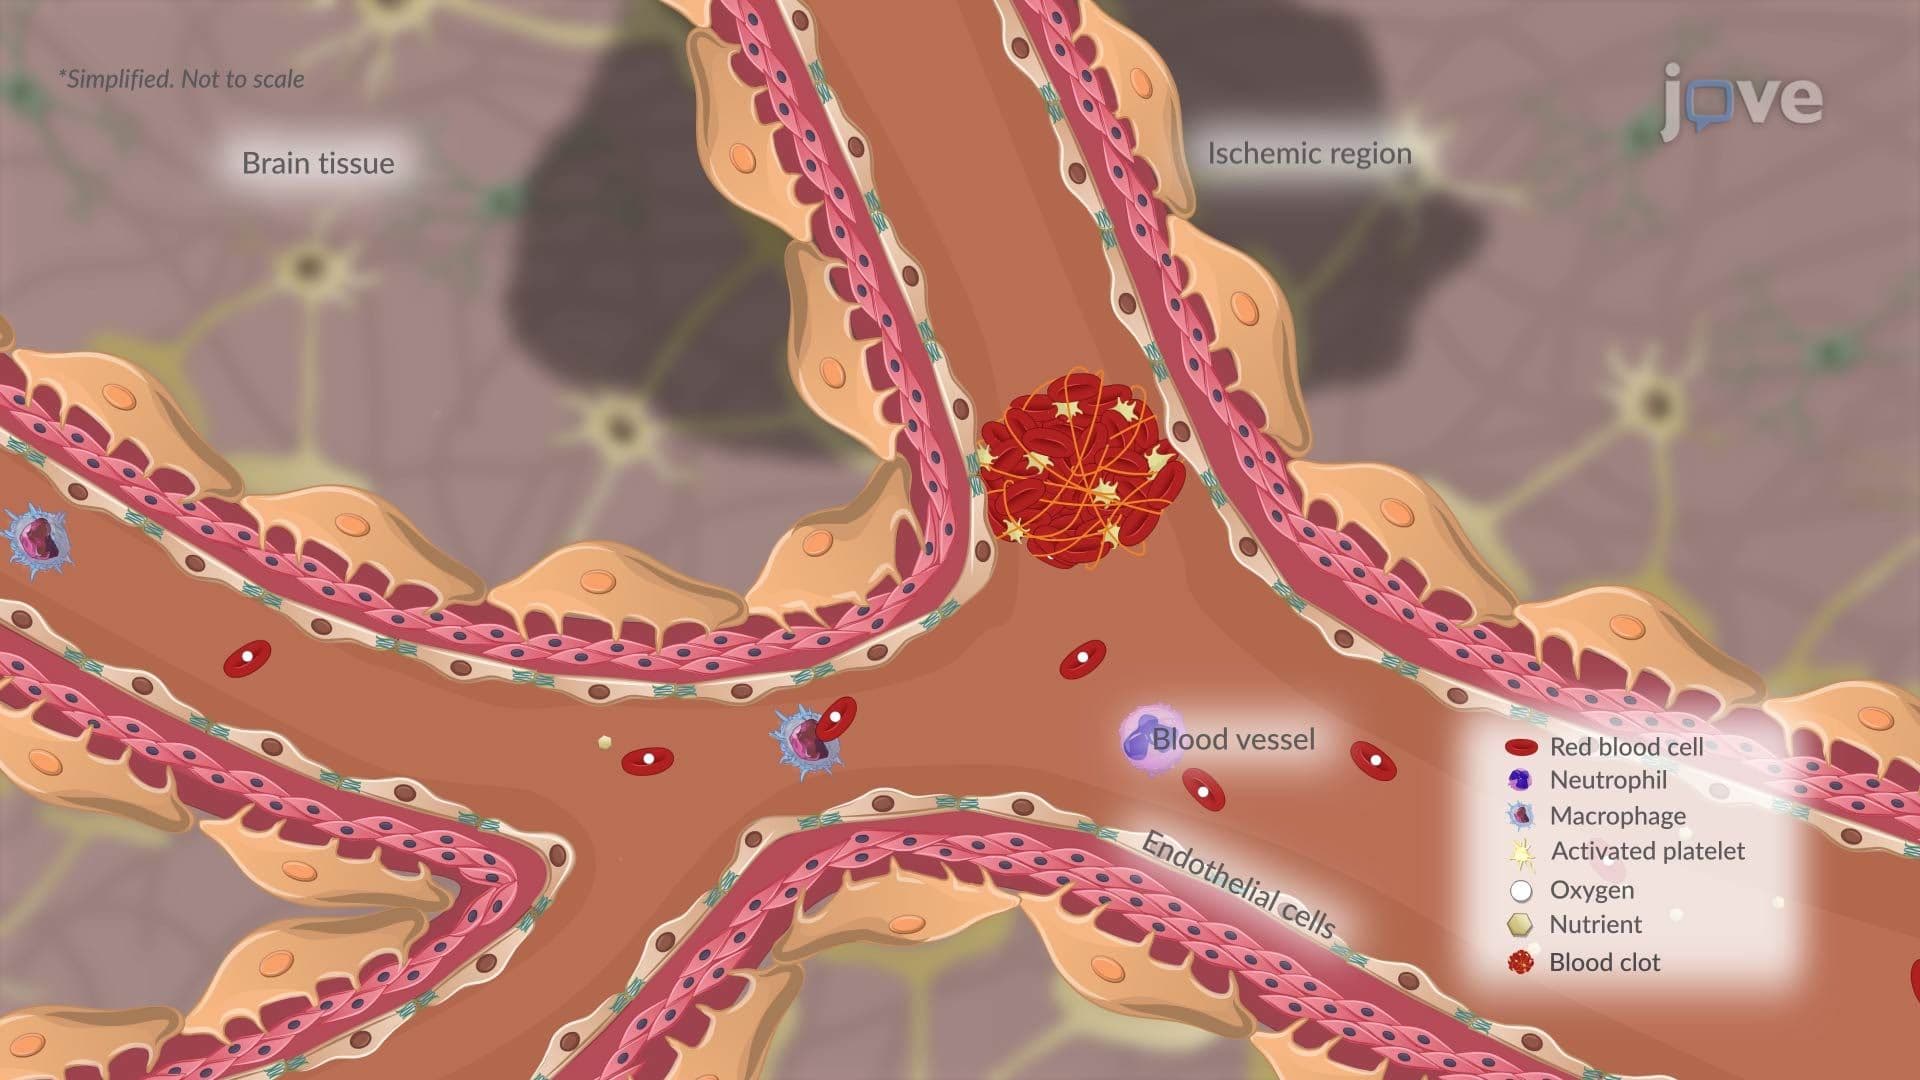
Transient Ischemic Attack l: Introduction
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...
 01:26
Arteries of the Head and Neck
The internal carotid arteries supply blood to the anterior portion of the cerebrum. They enter the...
 01:29
Stroke: Introduction and Types
 01:15
Ischemic Stroke l: Introduction
 01:17
Hemorrhagic Stroke l: Introduction