Related Experiment Video
Updated: May 1, 2026

Characterization of Sickling During Controlled Automated Deoxygenation with Oxygen Gradient Ektacytometry
Published on: November 5, 2019
Progression and prognostic indicators of bronchial disease in children with sickle cell disease
Sophia N Williams1, Eliezer Nussbaum, Leila Yoonessi
1Pediatric Pulmonology/Allergy/Immunology, Miller Children's Hospital, 2801 Atlantic Avenue, Long Beach, CA, 90806, USA.

Purpose:
The pulmonary complications of sickle cell disease (SCD) are a leading cause of morbidity and mortality (MacLean et al. Am J Respir Crit Care Med 178:1055-1059, 2008; Klings et al. Am J Respir Crit Care Med 173:1264-1269, 2006; National Heart, Lung, and Blood Institute, 2009). Despite this recognition, predictive markers of lung dysfunction progression remain elusive (Klings et al. Am J Respir Crit Care Med 173:1264-1269, 2006; Platt et al. N Engl J Med 330:1639-1644, 1994; Caboot et al. Curr Opin Pediatr 20:279-287, 2008; Field et al. Am J Hematol 83:574-576, 2008; Shirlo et al. Peadiatr Respir Review 12:78-82, 2011). This study was designed describe the longitudinal progression and identify specific markers that influence bronchial disease in SCD.
Methods:
A retrospective, chart review of 89 patients with SCD was conducted. All patients underwent spirometry in conjunction with body plethysmography as part of routine care. Eleven lung function variables were assessed, five of which were selected to establish patterns of normal, obstructive, restrictive, or mixed obstructive-restrictive physiology (Klings et al. Am J Respir Crit Care Med 173:1264-1269, 2006; Field et al. Am J Hematol 83:574-576, 2008).
Results:
In the unadjusted model, forced expiratory volume in one second (FEV1)% of predicted trended downward with age, while total lung capacity (TLC)% of predicted showed a bimodal distribution and carbon monoxide diffusion capacity corrected for hemoglobin (DLCOcor)% of predicted remained stable. Adjusting for acute chest syndrome (ACS) episodes, medication status, and growth velocity (GV), the final model demonstrated that the downward trend between FEV1% of predicted with age was further influenced by the latter two factors.
Conclusions:
Initial decline in FEV1% of predicted is associated with worsening pulmonary dysfunction over time. Independent of ACS episodes, the factors most influential on the progression of FEV1% predicted include the introduction of medications as well as the promotion of adequate prepubertal growth. Efforts to ensure normal prepubertal GV and treatment with bronchodilators, such as short-acting beta(2) agonists and inhaled corticosteroids (ICS), should be considered at an early age to delay progression of pulmonary dysfunction.


Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
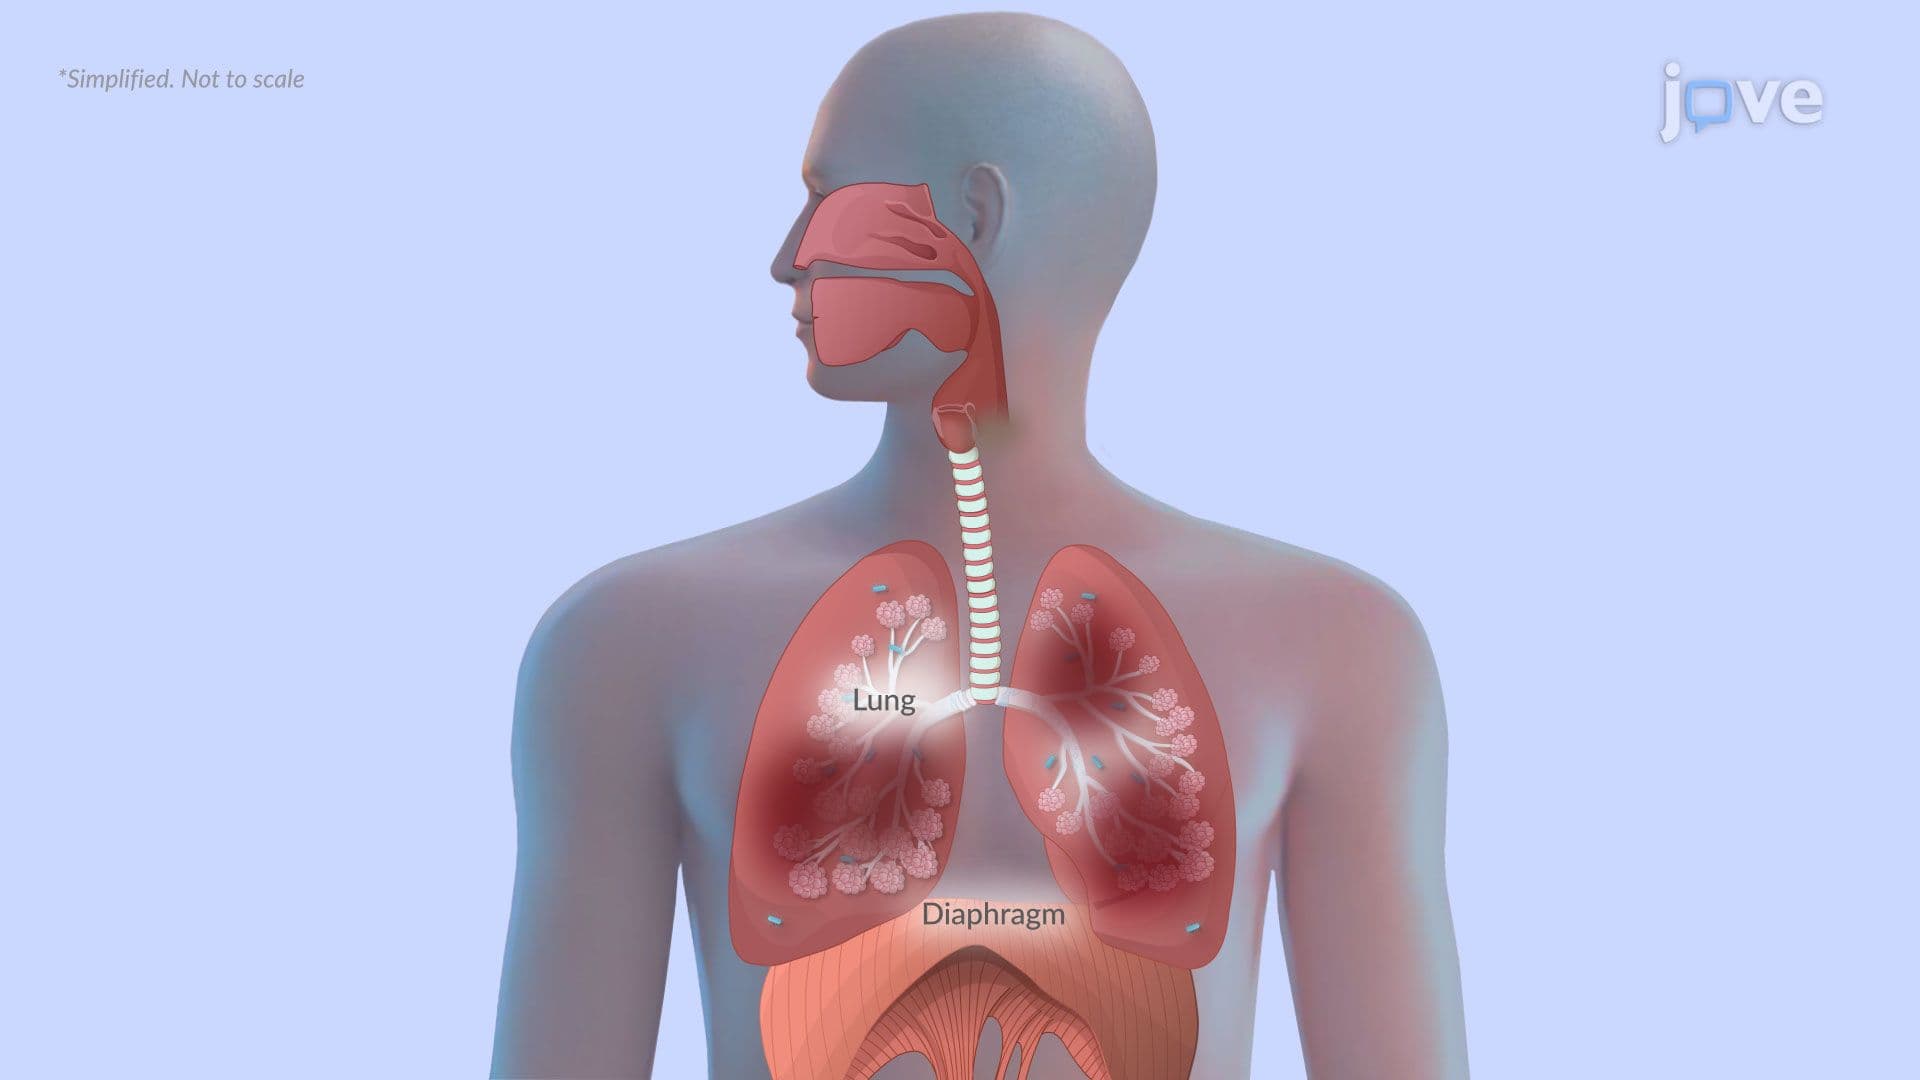 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:26
COPD: Management Using Bronchodilators and Corticosteroids