Related Experiment Video
Updated: May 1, 2026

A Method of Trigonometric Modelling of Seasonal Variation Demonstrated with Multiple Sclerosis Relapse Data
Published on: December 9, 2015
Estimated GFR and circulating 24,25-dihydroxyvitamin D3 concentration: a participant-level analysis of 5 cohort
Ian H de Boer1, Michael C Sachs2, Michel Chonchol3
1Division of Nephrology, Department of Medicine, Seattle, WA; Kidney Research Institute, Department of Medicine, Seattle, WA; Department of Epidemiology, University of Washington, Seattle, WA.

Background:
Decreased glomerular filtration rate (GFR) leads to reduced production of 1,25-dihydroxyvitamin D3 from 25-hydroxyvitamin D3 (25[OH]D3). Effects of low GFR on vitamin D catabolism are less well understood. We tested associations of estimated GFR (eGFR) with the circulating concentration of 24,25-dihydroxyvitamin D3 (24,25[OH]2D3), the most abundant product of 25(OH)D3 catabolism, across populations with a wide range of GFRs.
Study Design:
Cross-sectional study.
Setting & Participants:
9,596 participants in 5 cohort studies and clinical trials: the Diabetes Control and Complications Trial (N=1,193), Multi-Ethnic Study of Atherosclerosis (N=6,470), Cardiovascular Health Study (N=932), Seattle Kidney Study (N=289), and Hemodialysis Study (N=712).
Predictor:
eGFR.
Outcome:
Circulating 24,25(OH)2D3 concentration.
Measurements:
GFR was estimated from serum creatinine using the Chronic Kidney Disease Epidemiology Collaboration equation. Vitamin D metabolites were measured by mass spectrometry.
Results:
Circulating 24,25(OH)2D3 concentration was correlated with circulating 25(OH)D3 concentration (Pearson r range, 0.64-0.88). This correlation was weaker with lower eGFRs. Moreover, the increment in 24,25(OH)2D3 concentration associated with higher 25(OH)D3 concentration (slope) was lower with lower eGFRs: 2.06 (95% CI, 2.01-2.10), 1.77 (95% CI, 1.74-1.81), 1.55 (95% CI, 1.48-1.62), 1.17 (95% CI, 1.05-1.29), 0.92 (95% CI, 0.74-1.10), 0.61 (95% CI, 0.22-1.00), and 0.37 (95% CI, 0.35-0.39) ng/mL of 24,25(OH)2D3 per 10 ng/mL of 25(OH)D3 for eGFRs≥90, 60-89, 45-59, 30-44, 15-29, and <15 mL/min/1.73 m2 and end-stage renal disease treated with hemodialysis, respectively. As a result, at a 25(OH)D3 concentration of 20 ng/mL, mean 24,25(OH)2D3 concentrations were 2.92 (95% CI, 2.87-2.96), 2.68 (95% CI, 2.64-2.72), 2.35 (95% CI, 2.26-2.45), 1.92 (95% CI, 1.74-2.10), 1.69 (95% CI, 1.43-1.95), 1.14 (95% CI, 0.62-1.66), and 1.04 (95% CI,1.02-1.07) ng/mL for each category, respectively. This interaction was independent of other relevant clinical characteristics. Race, diabetes, urine albumin excretion, and circulating parathyroid hormone and fibroblast growth factor 23 concentrations more modestly modified the association of 24,25(OH)2D3 with 25(OH)D3.
Limitations:
Lack of direct pharmacokinetic measurements of vitamin D catabolism.
Conclusions:
Lower eGFR is associated strongly with reduced vitamin D catabolism, as measured by circulating 24,25(OH)2D3 concentration.

Related Concept Videos
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:24
Serum Studies: Renal Function Tests
 01:15
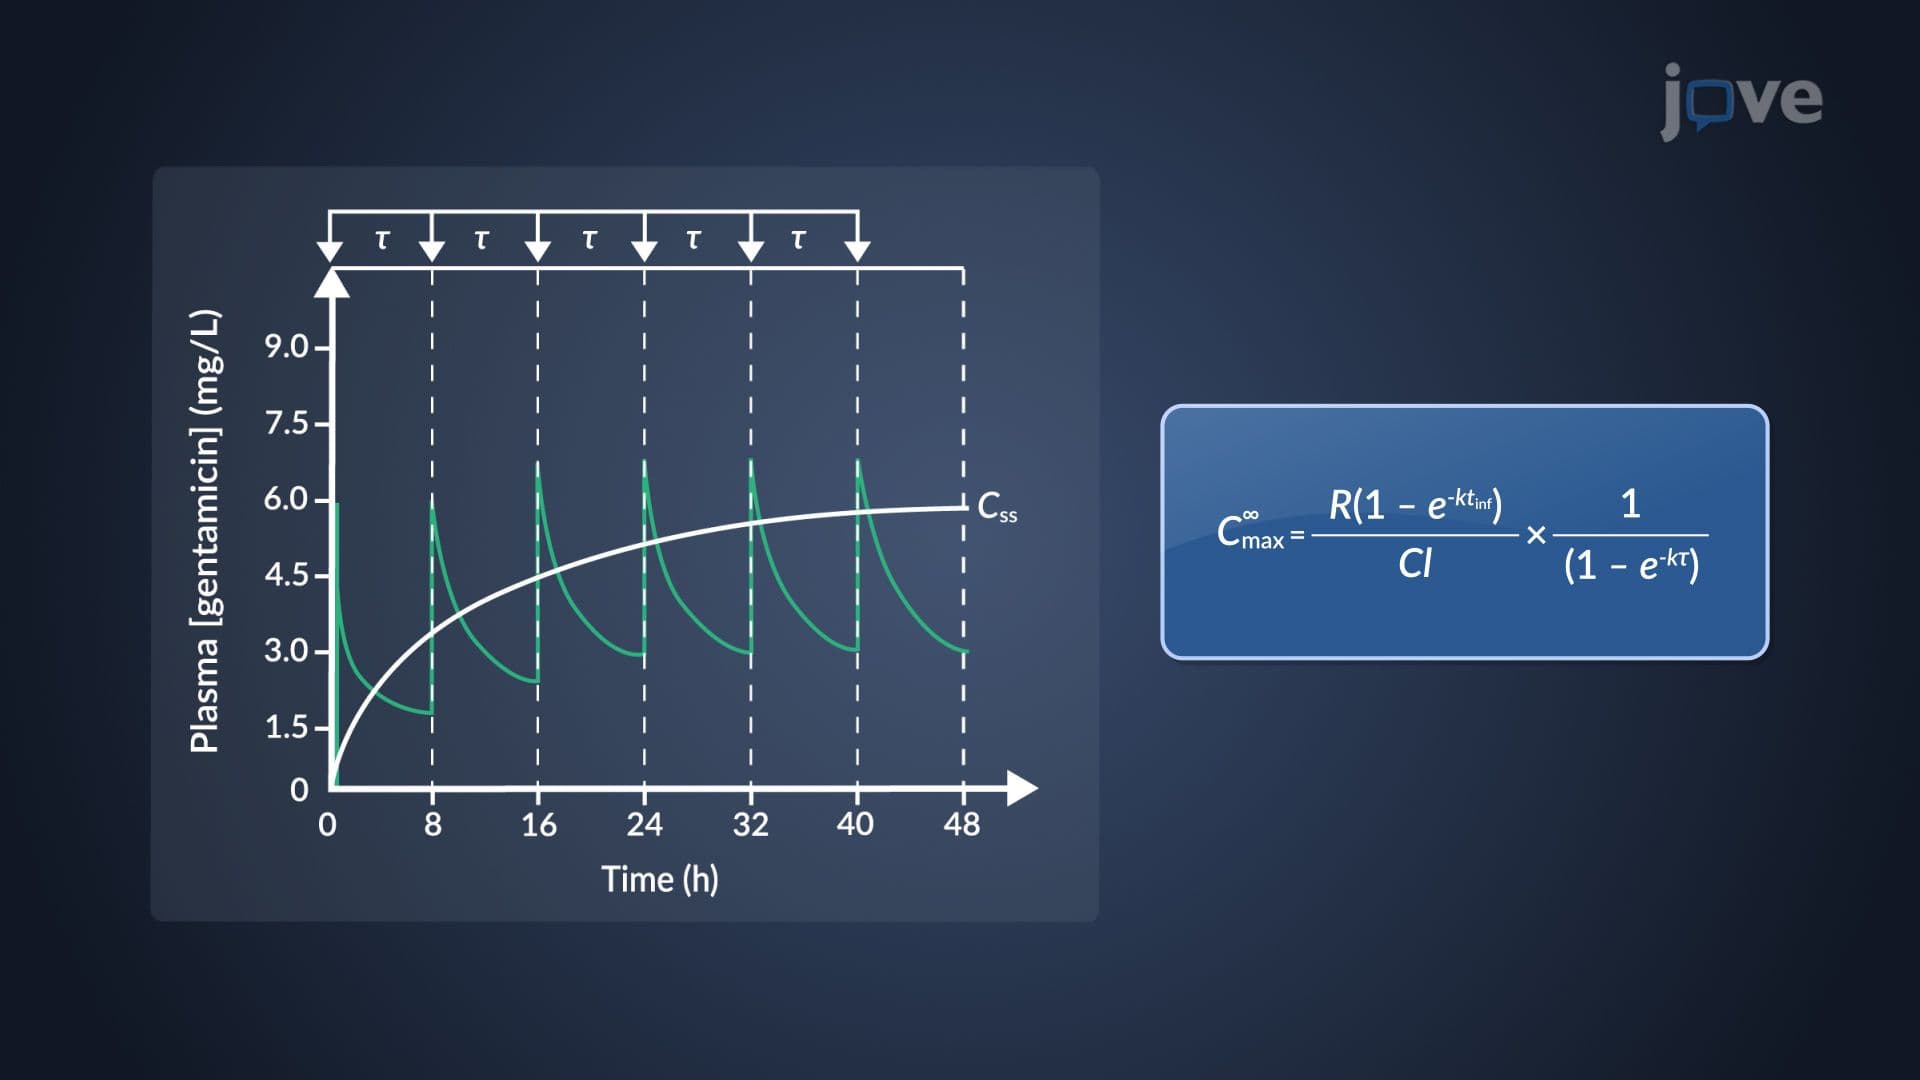
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:23
Role of Skin in Vitamin D Synthesis
The solar UV B rays (290-315 nm) are absorbed by the skin, and 7-dehydrocholesterol (provitamin D3) photolyzes it to previtamin D3, which undergoes a rapid transformation to vitamin...